Related Experiment Video
Updated: Nov 4, 2025
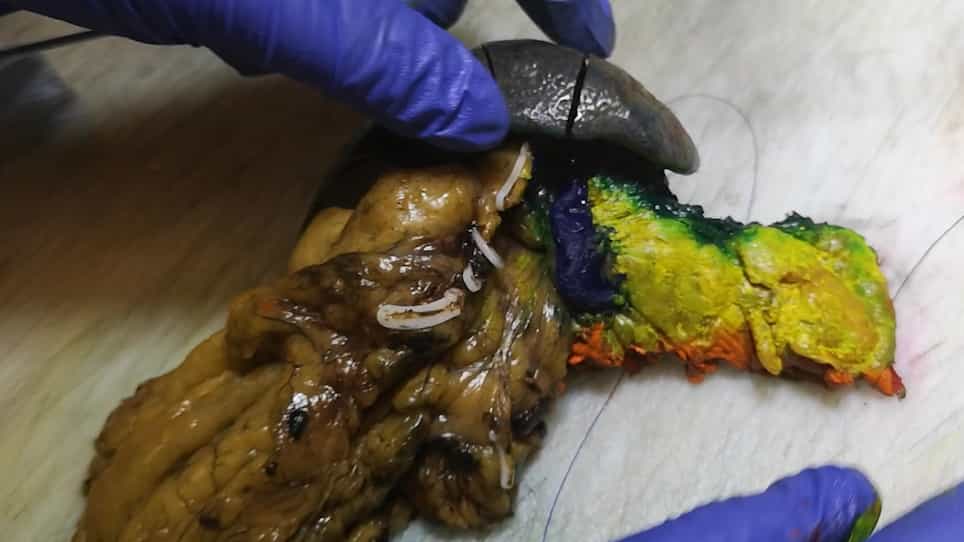

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Proclivity to Explore Locally Advanced Pancreas Cancer Is Not Associated with Surgeon Volume
Alex B Blair1, Robert W Krell2, Aslam Ejaz3
1Department of Surgery, Johns Hopkins Hospital, Baltimore, MD, USA.

Background And Purpose:
There is limited high-level evidence to guide locally advanced pancreas cancer (LAPC) management. Recent work shows that surgeons' preferences in LAPC management vary broadly. We sought to examine whether surgeon volume was associated with attitudes regarding LAPC management.
Methods:
An electronic survey was distributed by email to an international cohort of pancreas surgeons to evaluate practice patterns regarding LAPC management. Clinical vignette-based questions evaluated surgeons' attitudes regarding patient eligibility and the proclivity to offer exploration. Surgeons were classified into "low-" or "high-volume" categories according to thresholds of self-reported annual pancreatectomy volume. Surgeon's attitudes regarding LAPC management and inclination to consider exploration were compared across annual volume categories.
Results:
A total of 153 eligible responses were received from 4 continents, for an estimated response rate of 10.6%. Median duration of practice was 12 years (IQR 6-20). Most respondents reported >25 cases/year (89, 58.2%), of which 34 (22.2%) reported >50. Compared to surgeons with <25 cases/year, surgeons with >25 cases/year practiced longer (median 15 vs. 7.5 years, P<0.001) and were more likely to "always" recommend neoadjuvant chemotherapy (83.2% vs. 56.3%, P=0.001). Surgeons performing >50 cases/year were more likely to offer arterial resection (70.6% vs. 43.7%, P=0.006). The willingness to offer (or defer) exploration did not differ across any categories of surgeons' annual case volume.
Conclusions:
In an international survey of pancreas surgeons, the proclivity to consider exploration for LAPC was not associated with multiple categories of surgeon volume. Better evidence is needed to define the optimal management approach to LAPC.
More Related Videos
 03:55
Laparoscopic Posterior Radical Antegrade Modular Pancreatosplenectomy for Distal Pancreatic Carcinoma
Published on: December 29, 2023
 12:07
Laparoscopic Radical Antegrade Modular Pancreatosplenectomy via Dorsal-Caudal Artery Approach for Pancreatic Neck-Body Cancer
Published on: November 18, 2022