COVID-19 ARDS Is Characterized by Increased Dead Space Ventilation Compared With Non-COVID ARDS
Related Experiment Video
Updated: Nov 4, 2025
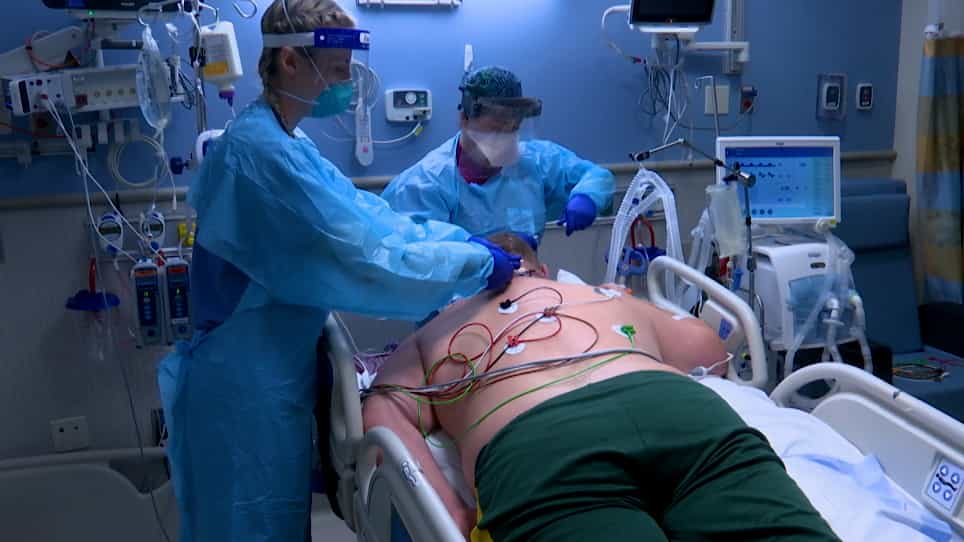
An Educational Video Demonstration of How to Prone a Critically Ill Intubated Patient
Published on: November 30, 2022
Michele Bertelli1, Federica Fusina2, Chiara Prezioso1,3
1Department of Anesthesia and Intensive Care, Fondazione Poliambulanza Hospital, Brescia, Italy.

Background:
ARDS in patients with coronavirus disease 2019 (COVID-19) is characterized by microcirculatory alterations in the pulmonary vascular bed, which could increase dead-space ventilation more than in non-COVID-19 ARDS. We aimed to establish if dead-space ventilation is different in patients with COVID-19 ARDS when compared with patients with non-COVID-19 ARDS.
Methods:
A total of 187 subjects with COVID-19 ARDS and 178 subjects with non-COVID-19 ARDS who were undergoing invasive mechanical ventilation were included in the study. The association between the ARDS types and dead-space ventilation, compliance of the respiratory system, subjects' characteristics, organ failures, and mechanical ventilation was evaluated by using data collected in the first 24 h of mechanical ventilation.
Results:
Corrected minute ventilation (V˙E), a dead-space ventilation surrogate, was higher in the subjects with COVID-19 ARDS versus in those with non-COVID-19 ARDS (median [interquartile range] 12.6 [10.2-15.8] L/min vs 9.4 [7.5-11.6] L/min; P < .001). Increased corrected V˙E was independently associated with COVID-19 ARDS (odds ratio 1.24, 95% CI 1.07-1.47; P = .007). The best compliance of the respiratory system, obtained after testing different PEEPs, was similar between the subjects with COVID-19 ARDS and the subjects with non-COVID-19 ARDS (mean ± SD 38 ± 11 mL/cm H2O vs 37 ± 11 mL/cm H2O, respectively; P = .61). The subjects with COVID-19 ARDS received higher median (interquartile range) PEEP (12 [10-14] cm H2O vs 8 [5-9] cm H2O; P < .001) and lower median (interquartile range) tidal volume (5.8 [5.5-6.3] mL/kg vs 6.6 [6.1-7.3] mL/kg; P < .001) than the subjects with non-COVID-19 ARDS, being these differences maintained at multivariable analysis. In the multivariable analysis, the subjects with COVID-19 ARDS showed a lower risk of anamnestic arterial hypertension (odds ratio 0.18, 95% CI 0.07-0.45; P < .001) and lower neurologic sequential organ failure assessment score (odds ratio 0.16, 95% CI 0.09-0.27; P < .001) than the subjects with non-COVID-19 ARDS.
Conclusions:
Indirect measurements of dead space were higher in subjects with COVID-19 ARDS compared with subjects with non-COVID-19 ARDS. The best compliance of the respiratory system was similar in both ARDS forms provided that different PEEPs were applied. A wide range of compliance is present in every ARDS type; therefore, the setting of mechanical ventilation should be individualized patient by patient and not based on the etiology of ARDS.
Related Concept Videos
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:29
Pneumonia II: Pathophysiology