Related Experiment Video
Updated: Nov 4, 2025
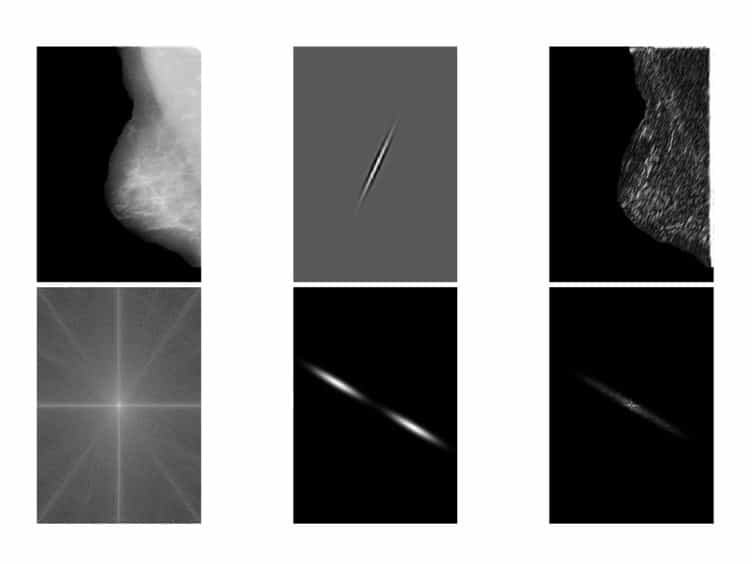

Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
O-RADS MRI score: analysis of misclassified cases in a prospective multicentric European cohort
I Thomassin-Naggara1,2, M Belghitti3,4, A Milon3,4
1APHP, Sorbonne Université, Hôpital Tenon, Service de radiologie, 58 avenue Gambetta, 75020, Paris, France. isabelle.thomassin@aphp.fr.

Objective:
To retrospectively review the causes of categorization errors using O-RADS-MRI score and to determine the presumptive causes of these misclassifications.
Methods:
EURAD database was retrospectively queried to identify misclassified lesions. In this cohort, 1194 evaluable patients with 1502 pelvic masses (277 malignant / 1225 benign lesions) underwent standardized MRI to characterize adnexal masses with histology or 2 years' follow-up as a reference standard. An expert radiologist reviewed cases with two junior radiologists and lesions termed misclassified if malignant lesion was scored ≤ 3, a benign lesion was scored ≥ 4, the site of origin was incorrect, or a non-adnexal mass was incorrectly categorized as benign or malignant.
Results:
There were 139 / 1502 (9.2%) misclassified masses in 116 women including 109 adnexal and 30 non-adnexal masses. False-negative cases corresponded to 16 borderline or invasive malignant adnexal masses rated score ≤ 3 (16 / 139, 11.5%). False-positive cases corresponded to 88 benign masses were rated score 4 (67 / 139, 48.2%) or 5 (18 / 139,12.9%) or considered suspicious non-adnexal lesions (3 / 139, 2.2%). Misclassifications were only due to origin error in 12 adnexal masses (8 benign, 4 malignant) (8.6%, 12 / 139) and 23 non-adnexal masses (18 benign, 5 malignant,16.5%, 23 / 139) perceived respectively as non-adnexal and adnexal masses. Interpretive error (n = 104), failure to recognize technical insufficient exams (n = 9), and perceptual errors (n = 4) were found. Most interpretive was due to misinterpretation of solid tissue or incorrect assignment of mass origin. Eighty-four out of 139 cases were correctly reclassified by the readers with strict adherence to the score rules.
Conclusion:
Most errors were due to misinterpretation of solid tissue or incorrect assignment of mass origin.
Key Points:
• Prospective assignment of O-RADS-MRI score resulted in misclassification of 9.25% of sonographically indeterminate pelvic masses. • Most errors were interpretive (74.8%) due to misinterpretation of solid tissue as defined by the lexicon or incorrect assignment of mass origin. • Pelvic inflammatory disease is a common source of misclassification (8.9%) (12 / 139).
Insights
O-RADS-MRI score misclassified 9.25% of pelvic masses, primarily due to interpretive errors like misinterpreting solid tissue or mass origin. Pelvic inflammatory disease was a common misclassification source.
Area of Science:
- Radiology
- Oncologic Imaging
- Pelvic MRI
Background:
- The O-RADS-MRI (Ovarian-Adnexal Reporting and Data System Magnetic Resonance Imaging) score aids in characterizing adnexal masses.
- Accurate classification is crucial for appropriate patient management and avoiding unnecessary interventions.
Purpose of the Study:
- To retrospectively analyze the causes of categorization errors using the O-RADS-MRI score.
- To identify the presumptive reasons behind misclassifications of pelvic masses.
Main Methods:
- Retrospective review of the EURAD database for misclassified pelvic masses (n=1502).
- Cases were evaluated by multiple radiologists, with misclassification defined by specific scoring, origin, or categorization criteria.
- Histology or 2-year follow-up served as the reference standard.
Main Results:
- 9.25% (139/1502) of masses were misclassified.
- Interpretive errors (74.8%) were the most common cause, stemming from misinterpreting solid tissue or incorrect mass origin assignment.
- Pelvic inflammatory disease accounted for 8.9% of misclassifications.
Conclusions:
- The O-RADS-MRI score, while valuable, is subject to misclassification, particularly due to interpretive challenges.
- Improving the understanding of solid tissue characteristics and mass origin is key to reducing errors.
- Standardized training and adherence to lexicon definitions are essential for accurate O-RADS-MRI application.
More Related Videos
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025
 14:27
Identification of Disease-related Spatial Covariance Patterns using Neuroimaging Data
Published on: June 26, 2013
Related Concept Videos
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:24
Magnetic Resonance Imaging