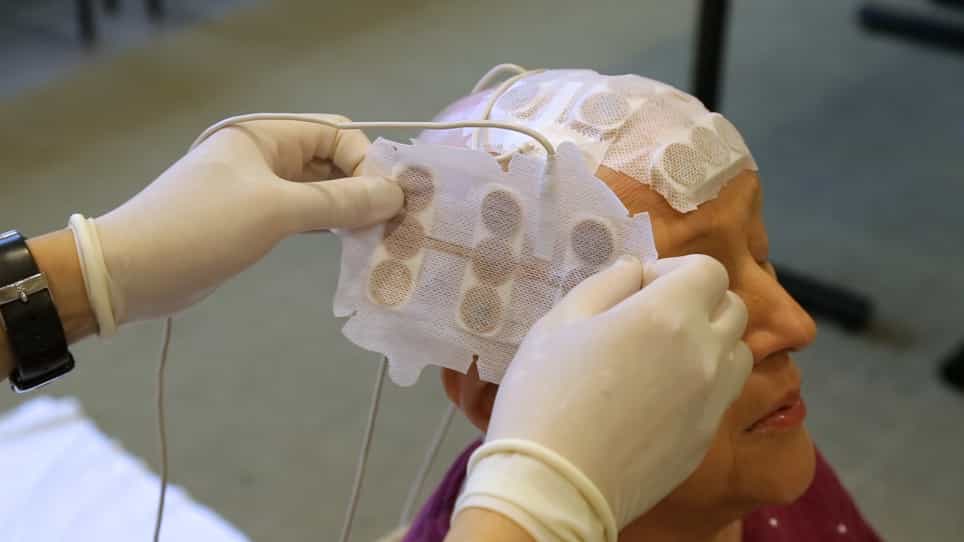
Related Experiment Video
Updated: Nov 4, 2025

Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Lessons learned from contemporary glioblastoma randomized clinical trials through systematic review and network
Shervin Taslimi1, Vincent C Ye1, Gelareh Zadeh1
1Division of Neurosurgery, Department of Surgery, University of Toronto, Toronto, Ontario, Canada.

Background:
Glioblastoma (GB) is the most common malignant brain tumor with a dismal prognosis despite standard of care (SOC). Here we used a network meta-analysis on treatments from randomized control trials (RCTs) to assess the effect on overall survival (OS) and progression-free survival (PFS) beyond the SOC.
Methods:
We included RCTs that investigated the addition of a new treatment to the SOC in patients with newly diagnosed GB. Our primary outcome was OS, with secondary outcomes including PFS and adverse reactions. Hazard ratio (HR) and its 95% confidence interval (CI) regarding OS and PFS were extracted from each paper. We utilized a frequentist network meta-analysis. We planned a subgroup analysis based on O6-methylguanine-DNA methyl-transferase (MGMT) status. We followed the Preferred Reporting Items for Systematic Reviews and Meta-analyses.
Results:
Twenty-one studies were included representing a total of 7403 patients with GB. There was significant heterogeneity among studies impacting important factors such as timing of randomization and sample size. A confidence analysis on the network meta-analysis results revealed a score of low or very low for all treatment comparisons, across subgroups. Allowing for the heterogeneity within the study population, alkylating nitrosoureas (Lomustine and ACNU) and tumor-treating field improved both OS (HR = 0.53, 95% CI 0.33-0.84 and HR = 0.63 95% CI 0.42-0.94, respectively) and PFS (HR = 0.88, 95% CI 0.77-1.00 and HR = 0.63 95% CI 0.52-0.76, respectively).
Conclusions:
Our analysis highlights the numerous studies performed on newly diagnosed GB, with no proven consensus treatment that is superior to the current SOC. Intertrial heterogeneity raises the need for better standardization in neuro-oncology studies.
Insights
Glioblastoma treatments beyond standard care show potential benefits in overall survival and progression-free survival. However, significant study heterogeneity necessitates better standardization in neuro-oncology research.
Area of Science:
- Neuro-oncology
- Clinical trial analysis
- Malignant brain tumors
Background:
- Glioblastoma (GB) is the most common and aggressive primary brain tumor.
- Current standard of care (SOC) offers limited efficacy, leading to a poor prognosis.
- Novel therapeutic strategies are crucial for improving patient outcomes.
Purpose of the Study:
- To conduct a network meta-analysis of randomized control trials (RCTs).
- To evaluate treatments added to SOC for newly diagnosed Glioblastoma.
- To assess the impact on overall survival (OS) and progression-free survival (PFS).
Main Methods:
- Included 21 RCTs with 7403 Glioblastoma patients.
- Utilized a frequentist network meta-analysis to compare treatments.
- Extracted Hazard Ratios (HR) and 95% Confidence Intervals (CI) for OS and PFS.
Main Results:
- Significant heterogeneity was observed across studies.
- Alkylating nitrosoureas (Lomustine, ACNU) and tumor-treating fields improved OS and PFS.
- Confidence analysis indicated low to very low certainty for treatment comparisons.
Conclusions:
- No single treatment beyond SOC demonstrated a definitive superiority for newly diagnosed Glioblastoma.
- Alkylating nitrosoureas and tumor-treating fields showed potential survival benefits.
- High intertrial heterogeneity underscores the need for improved standardization in neuro-oncology trials.