Related Experiment Video
Updated: Nov 4, 2025
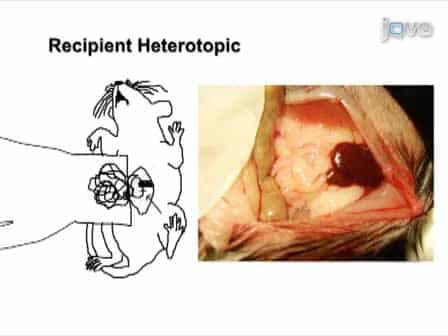

Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Analysis of 40 patients who underwent tracheal resection due to benign complex tracheal stenosis
Mehmet Furkan Sahin1, Muhammet Ali Beyoglu1, Alkin Yazicioglu1
1Department of General Thoracic Surgery and Lung Transplantation, Ankara City Hospital, University of Health Sciences, Ankara, Turkey.

Background:
Benign tracheal stenosis is a common complication in patients followed up in intensive care units. We aimed to analyze the etiology, diagnostic approaches, treatment methods for benign tracheal stenosis, and the predicting factors for complications after tracheal resection for benign stenosis.
Material-Method:
Forty patients who underwent tracheal resection reconstruction due to benign tracheal stenosis were analyzed retrospectively. Predictive factors for complications were determined by statistical analysis.
Results:
There were 23 patients (57.5%) in the intubation group, 11 patients (27.5%) in the tracheostomy group, and 6 patients (15%) in the subsequent tracheostomy group. Preoperatively, rigid dilatation was applied to all patients between 2 and 6 sessions (median = 3). Tracheal resections were performed in all patients after rigid dilatations. The mean of the resected segment lengths is 32.1 ± 8.8 mm. There was a statistically significant difference between preoperative bronchoscopic measurements, preoperative tomography measurements, and intraoperative measurements of the stenosis segment (ꭓ2 (2) = 71,500; p < 0.001). The patients' mean follow-up period was 27.4 ± 21.7 months (3-84). Mortality due to tracheal surgery and major anastomotic complications were not observed. The minor anastomotic complication rate was 12.5%, the non-anastomotic complication rate was 17.5%. The effect of resection length and surgical experience were found to be statistically significant risk factors for anastomotic complications.
Conclusions:
Rigid dilatation does not provide significant palliation in complex stenosis. Bronchoscopic measurements give closer results than CT measurements in the preoperative estimation of resection length. The risk of anastomotic complications increases when the length of the resection increases and when the surgical experience is less.


Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:23
Tracheostomy Suctioning II: Procedure