Related Experiment Video
Updated: Nov 4, 2025


Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Impact of Adjuvant Use of Midodrine to Intravenous Vasopressors: A Systematic Review and Meta-Analysis
Ahmad Al-Abdouh1, Sadam Haddadin1, Atul Matta2
1Department of Medicine, Ascension Saint Agnes Hospital, Baltimore, MD, USA.

Purpose:
To evaluate the efficacy and safety of midodrine use in intensive care units (ICU) to facilitate weaning off intravenous vasopressors (IVV).
Methods:
We searched PubMed/MEDLINE, Cochrane library, and Google Scholar (inception through October 18th, 2020) for studies evaluating adjuvant use of midodrine to IVV in the ICU. The outcomes of interest were ICU length of stay (LOS), hospital LOS, mortality, IVV reinstitution, ICU readmission, and bradycardia. Estimates were pooled using the random-effects model. We reported effect sizes as standardized mean difference (SMD) for continuous outcomes and risk ratios (RRs) for other outcomes with a 95% confidence interval (CI).
Results:
A total of 6 studies were found that met inclusion criteria and had sufficient data for our quantitative analysis (1 randomized controlled trial and 5 retrospective studies). A total of 2,857 patients were included: 600 in the midodrine group and 2,257 patients in the control group. Midodrine use was not associated with a significant difference in ICU LOS (SMD 0.16 days; 95% CI -0.23 to 0.55), hospital LOS (SMD 0.03 days; 95% CI -0.33 to 0.0.39), mortality (RR 0.87; 95% CI 0.52 to 1.46), IVV reinstitution (RR 0.47; 95% CI 0.17 to 1.3), or ICU readmission (RR 1.03; 95% CI 0.71 to 1.49) when compared to using only IVV. However, there were higher trends of bradycardia with midodrine use that did not reach significance (RR 7.64; 95% CI 0.23 to 256.42).
Conclusion:
This meta-analysis suggests that midodrine was not associated with a significant decrease in ICU LOS, hospital LOS, mortality, or ICU readmissions.
Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:18
Adrenergic Agonists: Therapeutic Classification
Vasopressor or pressor agents: They increase blood pressure and function as cardiac stimulants. Examples include endogenous catecholamines (norepinephrine and dopamine) and synthetic agents (phenylephrine).
Bronchodilators: β2-agonists can relax bronchial muscles and widen airways. They are commonly used for treating obstructive pulmonary...
 01:23
Antihypertensive Drugs: Vasodilators
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
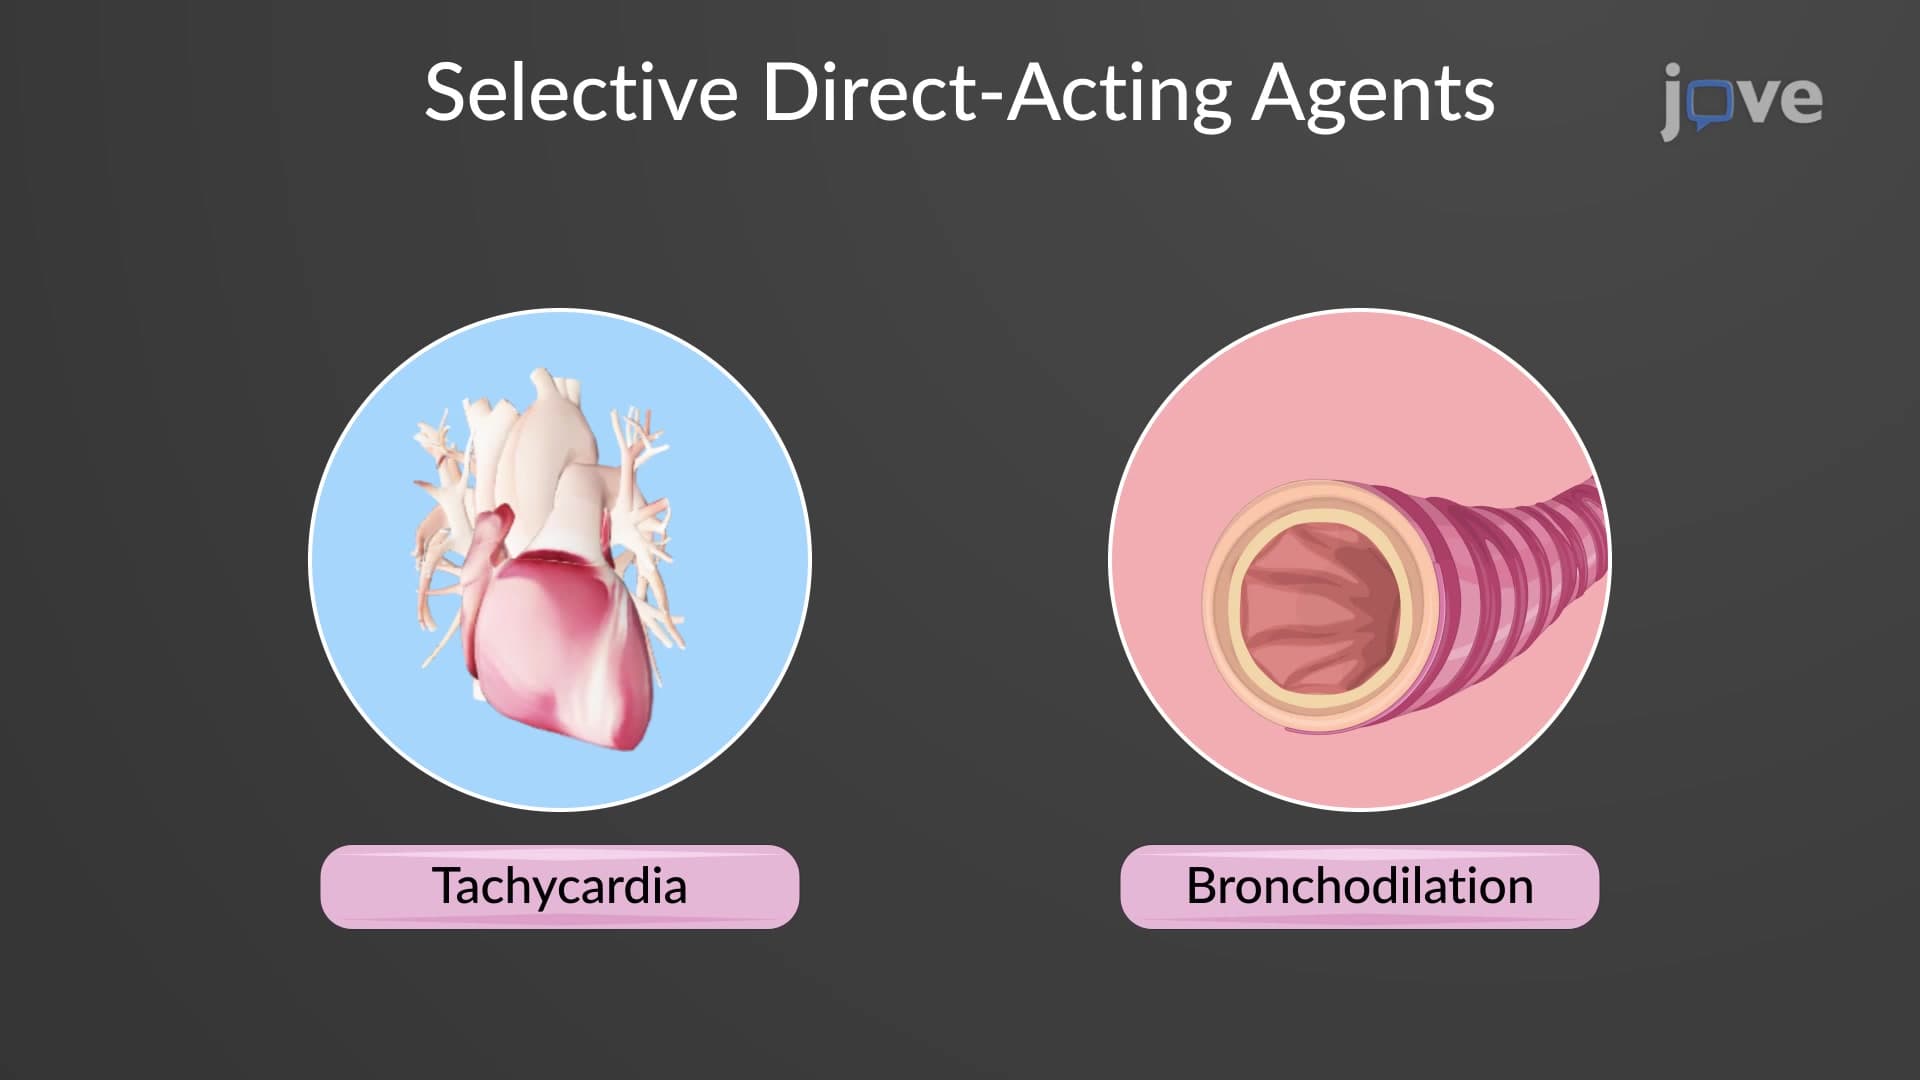
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:25
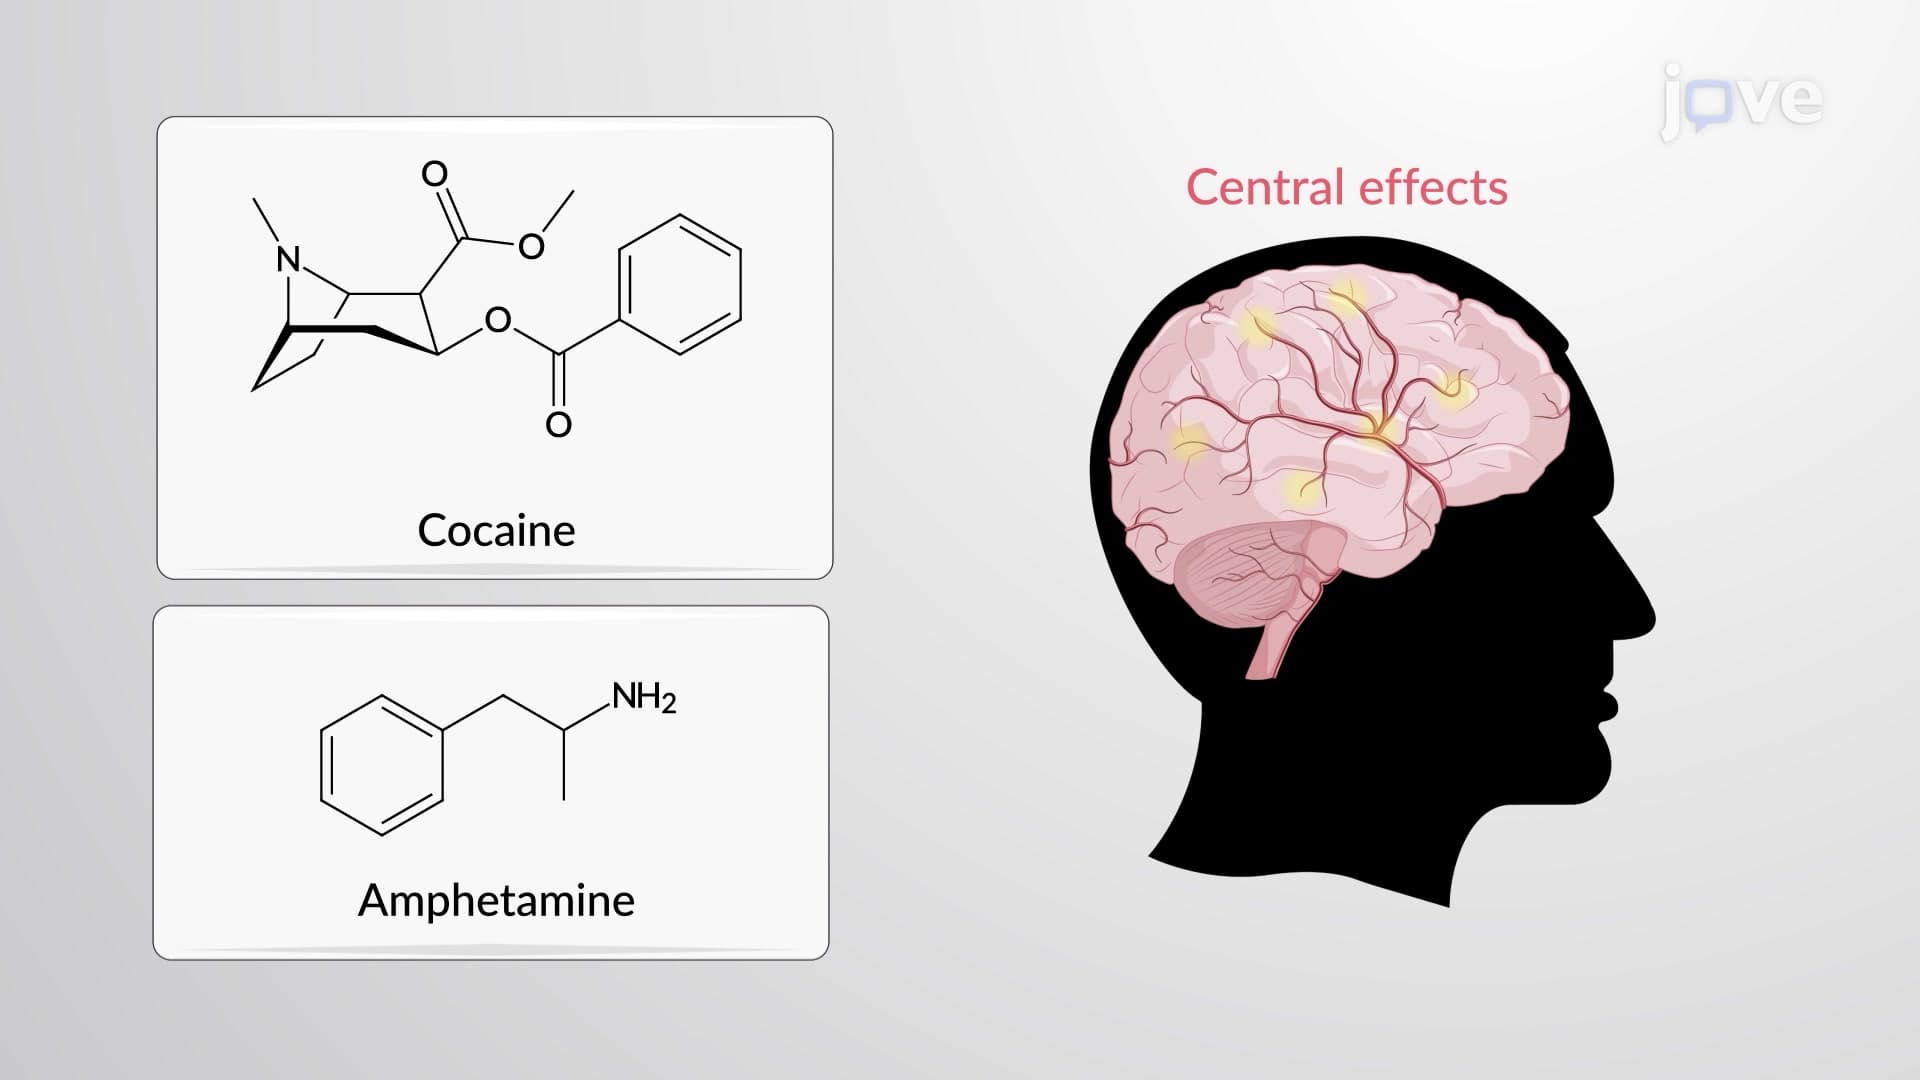
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral...