
Open Reduction and Suture Fixation of Acute Sternoclavicular Fracture-Dislocations in Children
Ishaan Swarup1, Michael S Hughes2, Alejandro Cazzulino3
1UCSF Benioff Children's Hospital, San Francisco, California.

Insights
This study details a novel surgical technique for acute sternoclavicular fracture-dislocation in children. Open reduction and suture fixation offer a stable solution when closed reduction fails, aiming for full recovery.
Area of Science:
- Pediatric Orthopedics
- Pediatric Trauma Surgery
Background:
- Acute sternoclavicular fracture-dislocation is an increasingly recognized injury in children, often resulting from high-energy trauma.
- These injuries can compress mediastinal structures and pose life-threatening risks.
- Current management, including closed reduction, has limited success, with few detailed descriptions of surgical interventions for pediatric cases.
Purpose of the Study:
- To describe the technique of open reduction and suture fixation for acute sternoclavicular fracture-dislocation in children.
- To highlight the rationale for surgical intervention over less successful closed reduction methods.
- To outline the expected outcomes of achieving full range of motion and strength without instability.
Main Methods:
- Surgical timing is determined by patient stability; emergency or urgent intervention is indicated for hemodynamic compromise or respiratory distress.
- The procedure involves a 6-8 cm incision, careful dissection to preserve the sternoclavicular ligament complex, and reduction using axial traction and specialized clamps.
- Reduction is augmented with suture fixation, followed by layered closure and postoperative immobilization in a sling.
Main Results:
- Open reduction allows direct visualization and accurate fracture reduction.
- Suture fixation provides stability without the need for hardware.
- The described technique aims for successful outcomes, including full range of motion and strength, as reported in pediatric literature.
Conclusions:
- Open reduction and suture fixation represent a viable and effective treatment for acute sternoclavicular fracture-dislocation in children.
- This method addresses the limitations of closed reduction and avoids the complexities of plate fixation or ligament reconstruction in acute settings.
- Careful perioperative planning mitigates risks such as vascular injury, ensuring favorable patient outcomes.
Background:
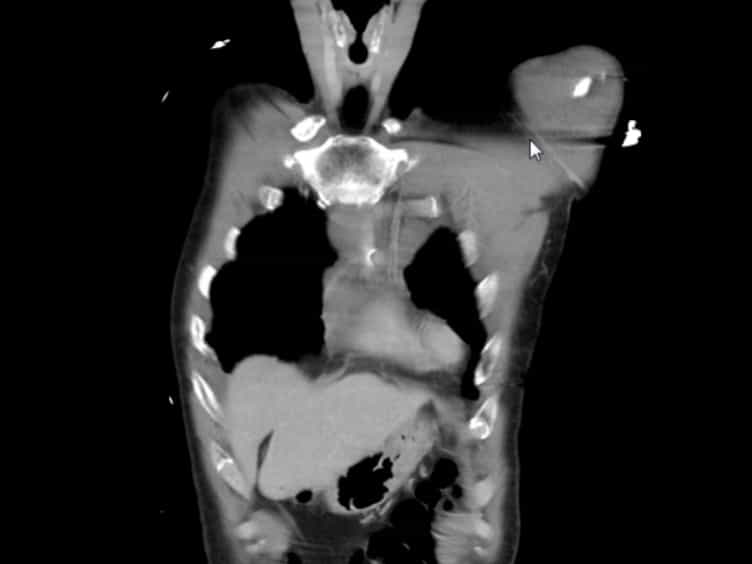
Acute sternoclavicular fracture-dislocation is associated with high-energy trauma and is being increasingly recognized in children1. These injuries are associated with compression of mediastinal structures and can be life-threatening1. The management of acute sternoclavicular fracture-dislocation includes closed reduction or open surgical stabilization; however, limited success is reported with closed reduction2,3. To our knowledge, there are no detailed descriptions of open reduction and suture fixation of acute sternoclavicular fracture-dislocation in children.
Description:
Following diagnosis of acute sternoclavicular fracture-dislocation, the timing of surgical treatment is determined according to several patient and surgical factors. Among patients with hemodynamic instability, respiratory compromise, or evidence of asymmetric perfusion, surgical treatment is needed on an emergency basis. In the absence of these factors, surgical treatment can be performed on an urgent basis. It is important to communicate with vascular or thoracic surgeons prior to proceeding to the operating room because of the rare case in which advanced surgical access or vascular repair is required. In the operating room, general anesthesia and large-bore intravenous access are required. Patients are positioned supine on a radiolucent table, and a small bump is placed between the scapulae to elevate the medial aspect of the clavicle. The contralateral sternoclavicular joint and medial aspect of the clavicle should be prepared into the sterile field, as well as both sides of the groin in case vascular access is needed. A 6 to 8-cm incision is centered on the medial aspect of the clavicle, extending to the manubrium. Standard dissection to the clavicle is performed, and care is taken to maintain the integrity of the sternoclavicular ligament complex. Circumferential dissection of the medial clavicular metaphysis is usually required in order to mobilize the dislocated fragment. Reduction of the physeal fracture usually requires axial traction and extension of the ipsilateral shoulder with the aid of a reduction clamp on the medial clavicular metaphysis. In some cases, a Freer elevator can be placed between the metaphysis and epiphysis to shoehorn the clavicle from posterior to anterior. Once reduced, the fracture-dislocation is usually stable; however, the reduction is augmented with suture fixation. The sternoclavicular joint capsule should be repaired if disrupted, and the incision should be closed in layers. Postoperatively, the arm is placed in a sling, and range of motion is commenced at 4 weeks.
Alternatives:
Alternative management of acute sternoclavicular fracture-dislocation includes closed reduction, plate fixation4, and ligament reconstruction5.
Rationale:
In our experience, closed reduction is often unsuccessful, which is consistent with the experiences reported by other authors2,3. In addition, suture fixation is sufficient and plate fixation is not required because this injury is relatively stable following reduction. Lastly, ligament reconstruction with use of autograft or allograft may be indicated but is more relevant in chronic cases with injury or attenuation of the sternoclavicular ligament complex. Open reduction allows for direct visualization of the fracture reduction, and suture fixation allows for increased stability without the need for hardware or secondary surgical procedures.
Expected Outcomes:
We expect patients to achieve full range of motion and strength without any joint instability as reported by Waters et al.3.
Important Tips:
There is an inherent risk of vascular injury with open reduction and suture fixation. This risk is mitigated with perioperative planning and consultation with vascular or thoracic surgeons. General surgeons should always be available when these procedures are performed in case of vascular issues or emergencies.It is sometimes difficult to reduce the dislocation, but additional maneuvers allow for controlled reduction of the displaced clavicle, such as using a Freer elevator and serrated clamp.Assessing fracture reduction can be difficult intraoperatively. Including the contralateral sternoclavicular joint in the sterile surgical field can be helpful in assessing fracture reduction and osseous contour.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...