Related Experiment Video
Updated: Nov 3, 2025


Supramaximal Intensity Hypoxic Exercise and Vascular Function Assessment in Mice
Published on: March 15, 2019
Muscle Metaboreflex Control of Sympathetic Activity Is Preserved after Acute Intermittent Hypercapnic Hypoxia
Brooke M Shafer1, Anthony V Incognito2, Tyler D Vermeulen1
1Centre for Heart, Lung, and Vascular Health, School of Health and Exercise Sciences, University of British Columbia, Kelowna, British Columbia, CANADA.

Purpose:
In normotensive patients with obstructive sleep apnea (OSA), the muscle sympathetic nerve activity (MSNA) response to exercise is increased while metaboreflex control of MSNA is decreased. We tested the hypotheses that acute intermittent hypercapnic hypoxia (IHH) in males free from OSA and associated comorbidities would augment the MSNA response to exercise but attenuate the change in MSNA during metaboreflex activation.
Methods:
Thirteen healthy males (age = 24 ± 4 yr) were exposed to 40 min of IHH. Before and after IHH, the pressor response to exercise was studied during 2 min of isometric handgrip exercise (at 30% maximal voluntary contraction), whereas the metaboreflex was studied during 4 min of postexercise circulatory occlusion (PECO). Mean arterial pressure (MAP), heart rate (HR), and fibular MSNA were recorded continuously. MSNA was quantified as burst frequency (BF) and total activity (TA). Mixed effects linear models were used to compare the exercise pressor and metaboreflex before and after IHH.
Results:
As expected, IHH led to significant increases in MSNA BF, TA, and MAP at baseline and throughout exercise and PECO. However, during handgrip exercise, the change from baseline in MAP, HR, MSNA BF, and TA was similar before and after IHH (All P > 0.31). During PECO, the change from baseline in MSNA BF and TA was similar after IHH, whereas the change from baseline in MAP (Δ14 mm Hg, 95% CI = 7-19, vs Δ16 mm Hg, 95% CI = 10-21; P < 0.01) was modestly increased.
Conclusion:
After acute IHH, MSNA response to handgrip exercise and metaboreflex activation were preserved in healthy young males despite overall increases in resting MSNA and MAP. Chronic IHH and comorbidities often associated with OSA may be required to modulate the exercise pressor reflex and metaboreflex.
More Related Videos
 05:45
Delivery of In Vivo Acute Intermittent Hypoxia in Neonatal Rodents to Prime Subventricular Zone-derived Neural Progenitor Cell Cultures
Published on: November 2, 2015
 05:45
Experimental Approach to Examine Leptin Signaling in the Carotid Bodies and its Effects on Control of Breathing
Published on: October 25, 2019
Related Concept Videos
 01:23
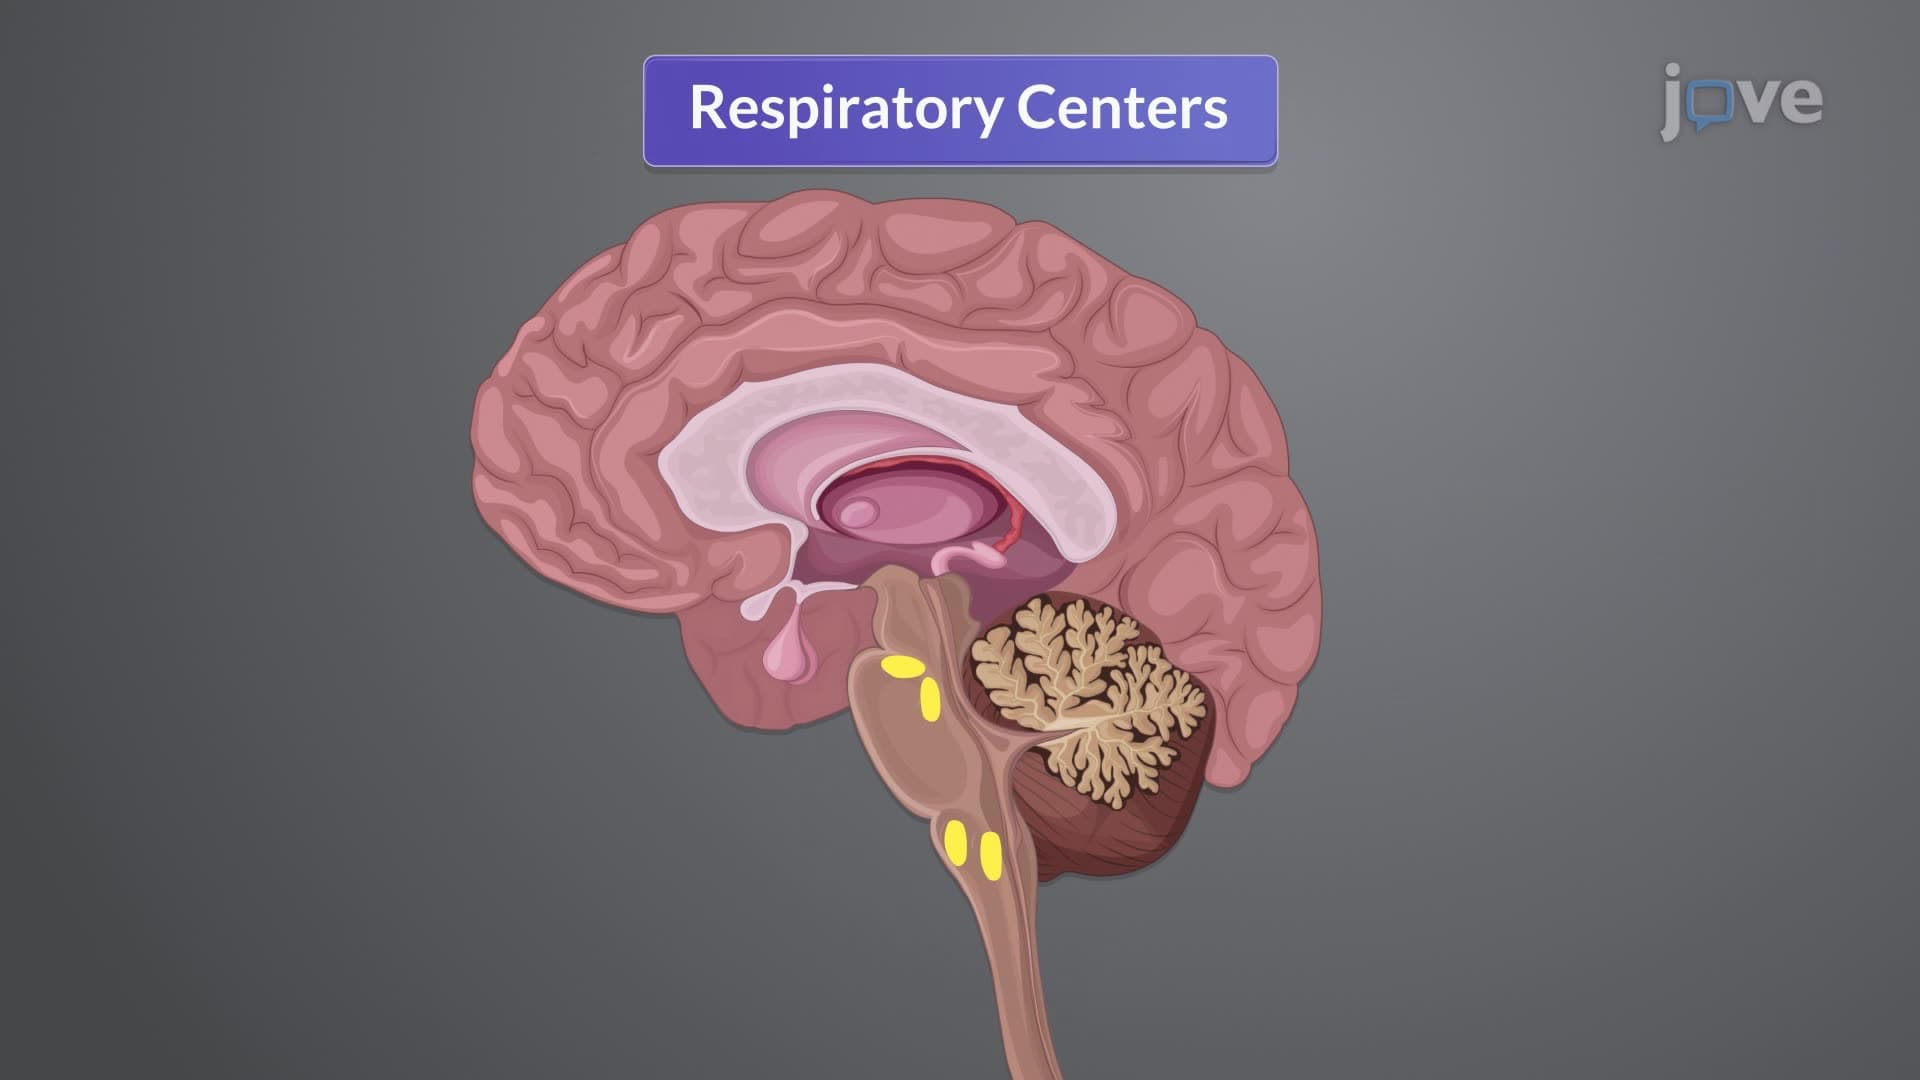
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:25
Hyperpnea and Hyperventilation
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical...
 01:31
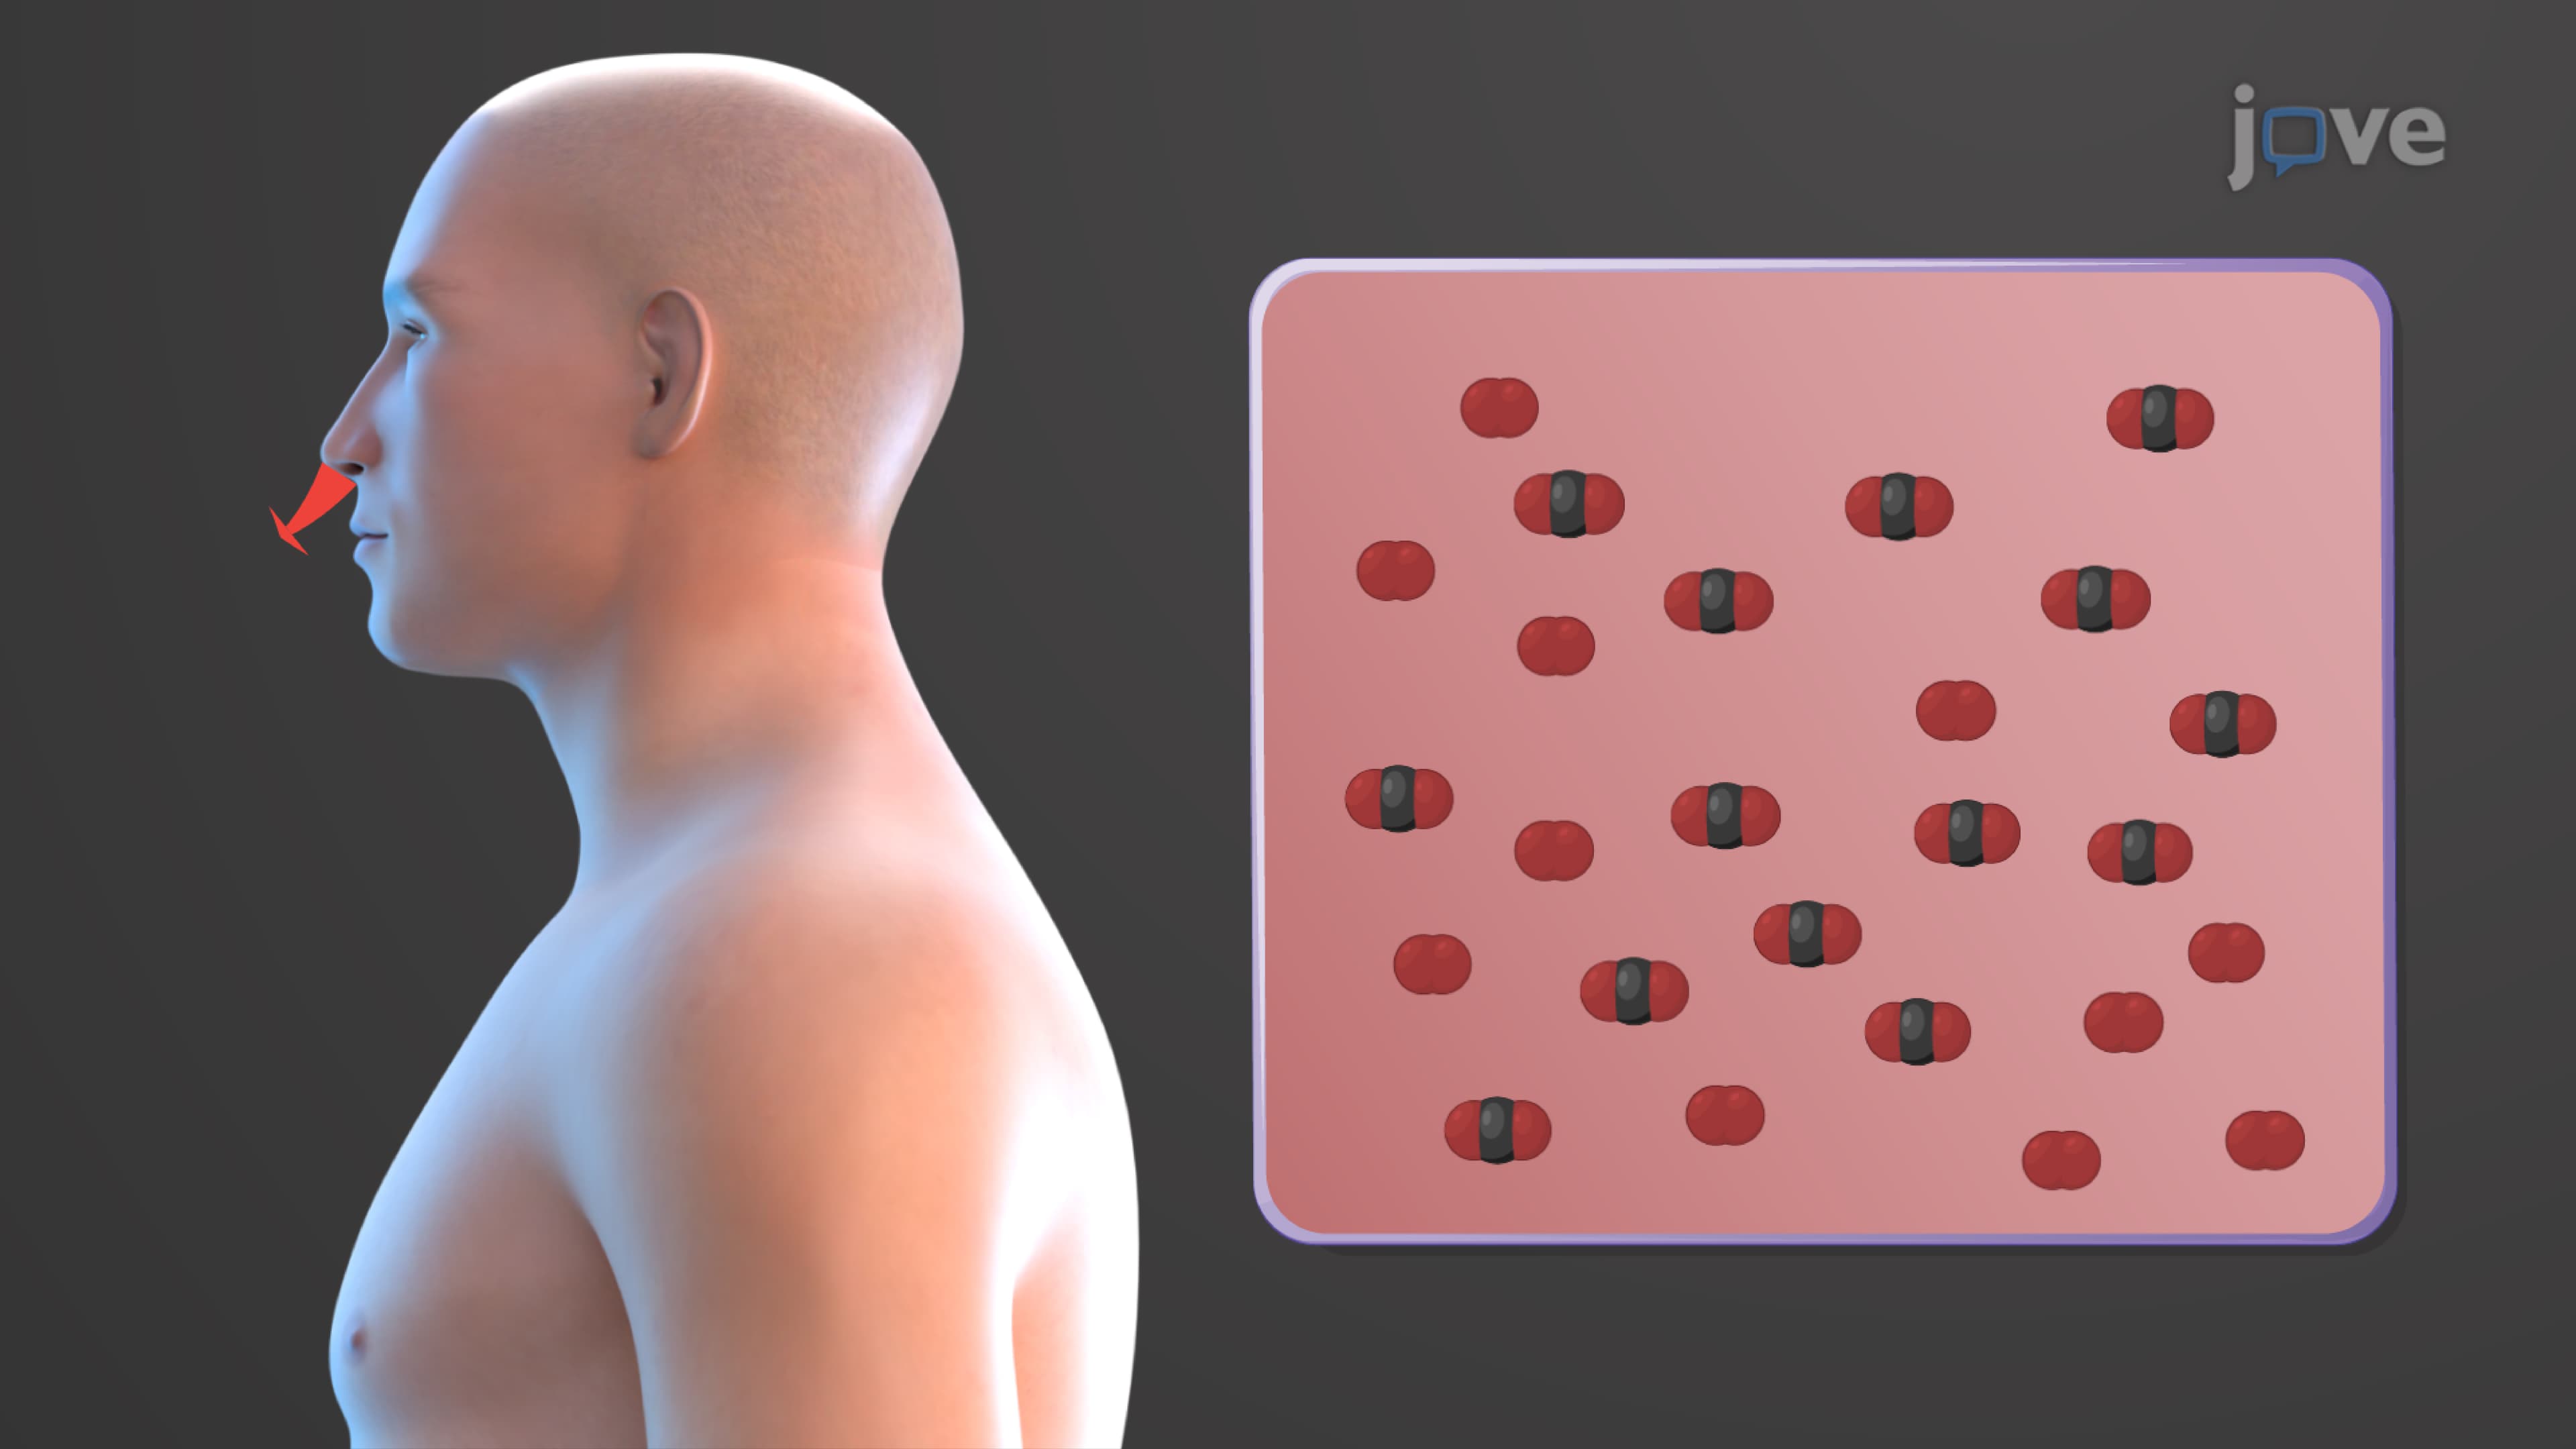
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:18
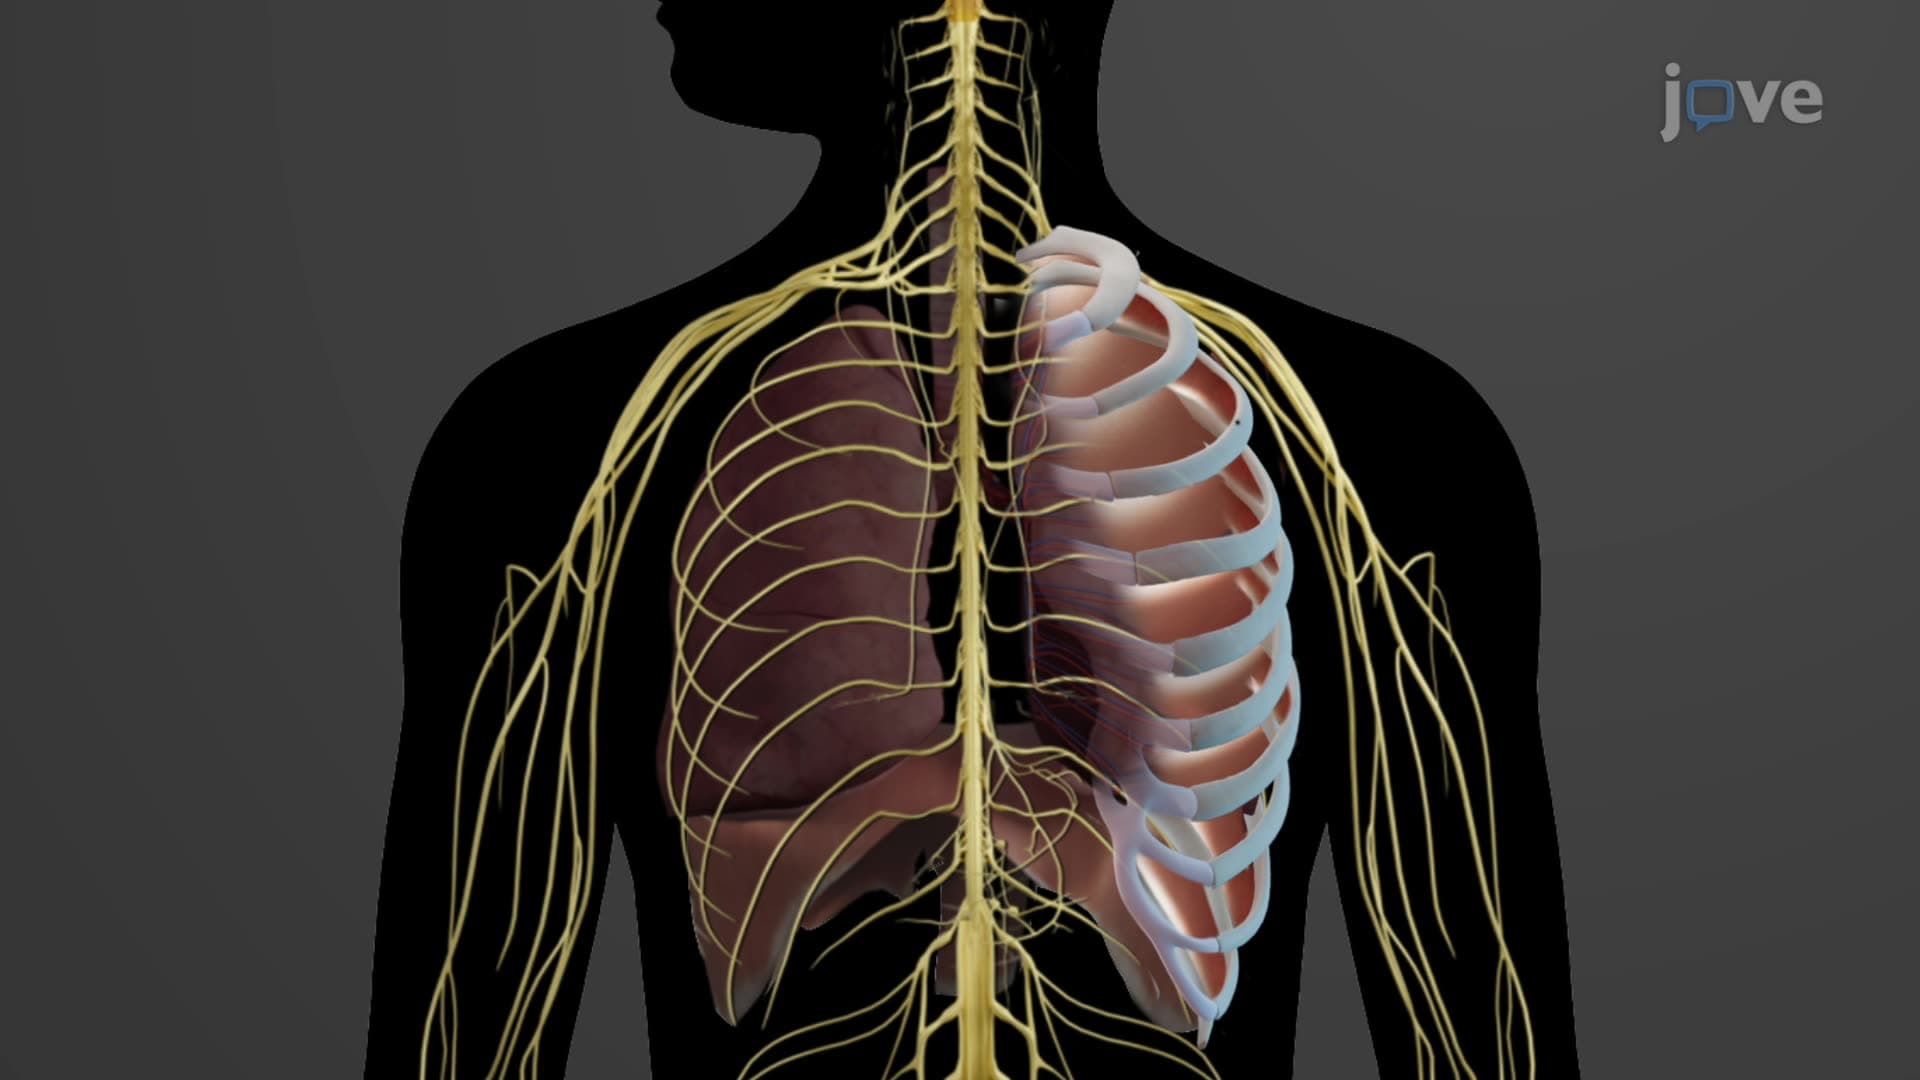
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...