Related Experiment Video
Updated: Nov 3, 2025
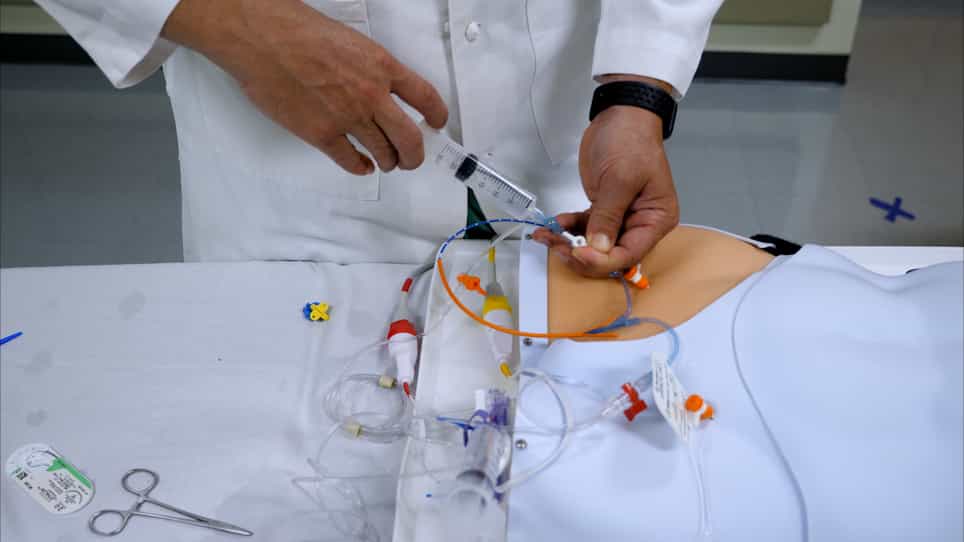
Complete and Partial Resuscitative Endovascular Balloon Occlusion of the Aorta for Hemorrhagic Shock
Published on: May 19, 2022
Predicting success of resuscitative endovascular occlusion of the aorta: Timing supersedes variable techniques in
Alexis L Cralley1, Ernest E Moore, Thomas M Scalea
1From the Department of Surgery (A.L.C., E.E.M.), Denver Health Medical Center, Denver, Colorado; Department of Surgery (T.M.S., C.J.F.), University of Maryland School of Medicine, Baltimore, Maryland; Department of Surgery (K.I.), University of Southern California, Los Angeles, California; Department of Surgery (E.M.B.), University of Washington School of Medicine, Seattle, Washington; Department of Surgery at UT Health (D.E.M.), Texas Health Science Center's McGovern Medical School, Houston, Texas; Colorado School of Public Health (A.S.), Aurora, Colorado.

Background:
Resuscitative endovascular occlusion of the aorta (REBOA) is used for temporary aortic occlusion of trauma patients in the management of noncompressible hemorrhage. Previous studies have focused on how to properly perform REBOA in the trauma environment to improve survival rates, but high-grade evidence defining the ideal patient population does not yet exist. This post hoc analysis of the Emergent Truncal Hemorrhage Control Study seeks to identify the most important clinical factors for physicians to consider when selecting for REBOA candidates and their potential survival following REBOA.
Methods:
Post hoc analysis of a large, multicenter, prospective observational study conducted at six level 1 trauma centers, 2017 to 2018, was performed. An onsite data collector documented all time points for REBOA patients since admission. Candidate predictors were demographics; injury severity; physiology preprocedure, during procedure, and postprocedure; cardiopulmonary resuscitation; and REBOA-specific variables (time to procedure, procedure-related time intervals, access site, technique, sheath size, catheter length, balloon volume, deployment zone). Predictive models for survival at three different time points along the trauma triage and REBOA process timeline ("Admission," "REBOA Initiation," and "Postaortic Occlusion") were devised by logistic regression.
Results:
Eighty-eight patients had REBOA placement. The Admission model selected age, Glasgow Coma Scale, and admission systolic blood pressure as significant predictors of survival (area under the receiver operating characteristic curve [AUROC], 0.86; 95% CI, 0.77-0.94). The REBOA Initiation and Postaortic Occlusion models selected age, Glasgow Coma Scale, and the systolic blood pressure measured just before balloon inflation as predictors for survival (AUROC, 0.87 [95% CI, 0.78-0.97] and AUROC, 0.90 [95% CI, 0.81-0.99], respectively). No REBOA procedural variables were identified as predictors of patient survival.
Conclusion:
Only patient-specific criteria of age, neurologic status, and severity of shock predicted survival. The hemodynamic stability of the patient at the time REBOA is initiated is more important than how REBOA is initiated. These findings suggest that earlier preparation for REBOA placement may be a key to improved survival.
Level Of Evidence:
Therapeutic, level IV.


Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Aneurysm IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care