Related Experiment Video
Updated: Nov 2, 2025

Surgical Techniques for Catheter Placement and 5/6 Nephrectomy in Murine Models of Peritoneal Dialysis
Published on: July 19, 2018
Elimination of fosfomycin during dialysis with the Genius system in septic patients
T Dimski1, T Brandenburger2, M Janczyk3
1Department of Anesthesiology, University Hospital Düsseldorf, Heinrich Heine University Düsseldorf, Moorenstr. 5, 40225, Düsseldorf, Germany. Thomas.Dimski@med.uni-duesseldorf.de.

Abstract:
To assess fosfomycin (FOS) elimination in patients with sepsis and acute kidney injury (AKI) undergoing slow-extended daily dialysis (SLEDD) with the Genius system in a prospective observational study. After ethics committee approval ten patients with sepsis and AKI stage 3 underwent daily SLEDD sessions of eight hours. FOS was applied i.v. at doses of 3 × 5 g per day. FOS serum levels were measured pre- and post hemofilter before, during, and after SLEDD sessions, and instantaneous clearance was calculated. In five of the patients, we analyzed FOS levels after the first dose, in the other five patients serum levels were measured during ongoing therapy. FOS was eliminated rapidly via the hemofilter. FOS clearance decreased from 152 ± 10 mL/min (start of SLEED session) to 43 ± 38 mL/min (end of SLEDD session). In 3/5 first-dose patients after 4-6 h of SLEDD the FOS serum level fell below the EUCAST breakpoint of 32 mg/L for Enterobacterales and Staphylococcus species. In all patients with ongoing fosfomycin therapy serum levels were high and above the breakpoint at all times. FOS toxicity or adverse effects were not observed. FOS serum concentrations exhibit wide variability in critically ill patients with sepsis and AKI. FOS is eliminated rapidly during SLEDD. A loading dose of 5 g is not sufficient to achieve serum levels above the EUCAST breakpoint for common bacteria in all patients, considering that T > MIC > 70% of the dosing interval indicates sufficient plasma levels. We thus recommend a loading dose of 8 g followed by a maintenance dose of 5 g after a SLEDD session in anuric patients. We strongly recommend therapeutic drug monitoring of FOS levels in critically ill patients with AKI and dialysis therapy.
More Related Videos

Related Concept Videos
 01:15
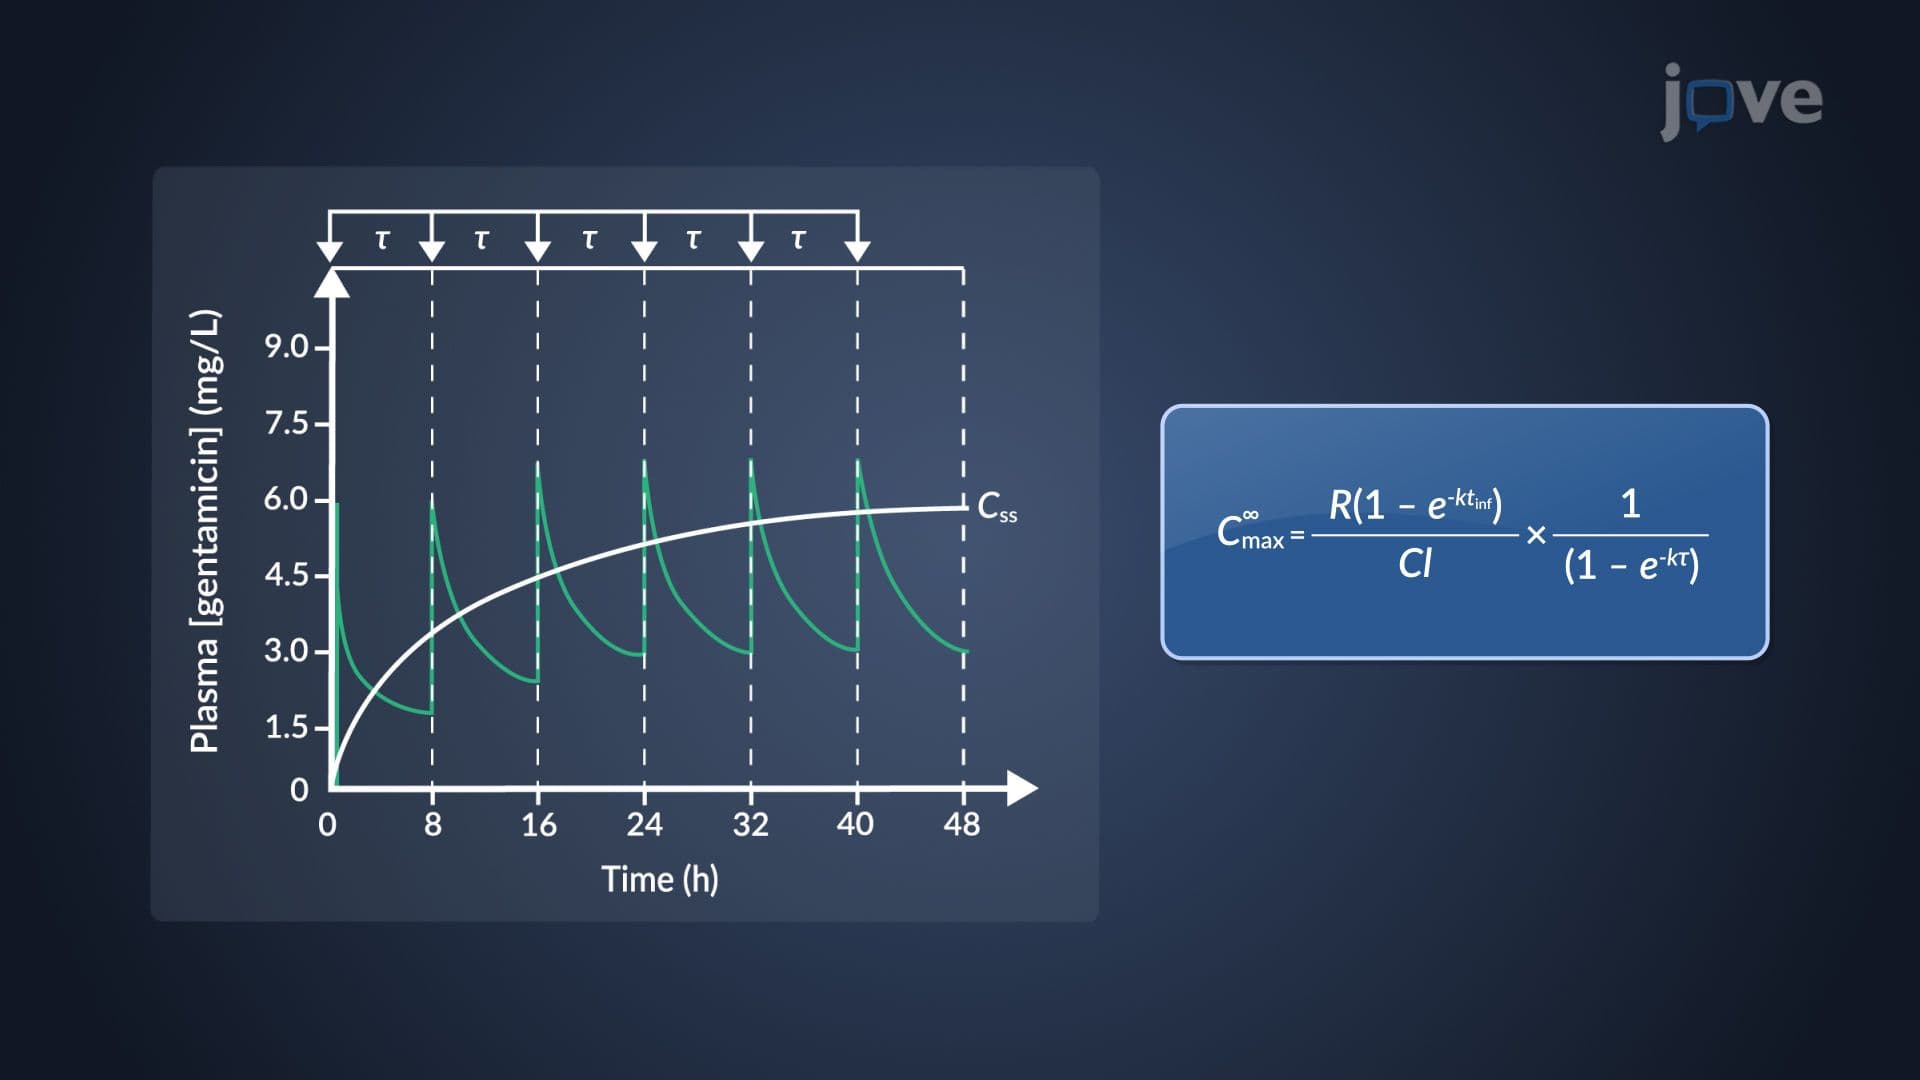
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:30
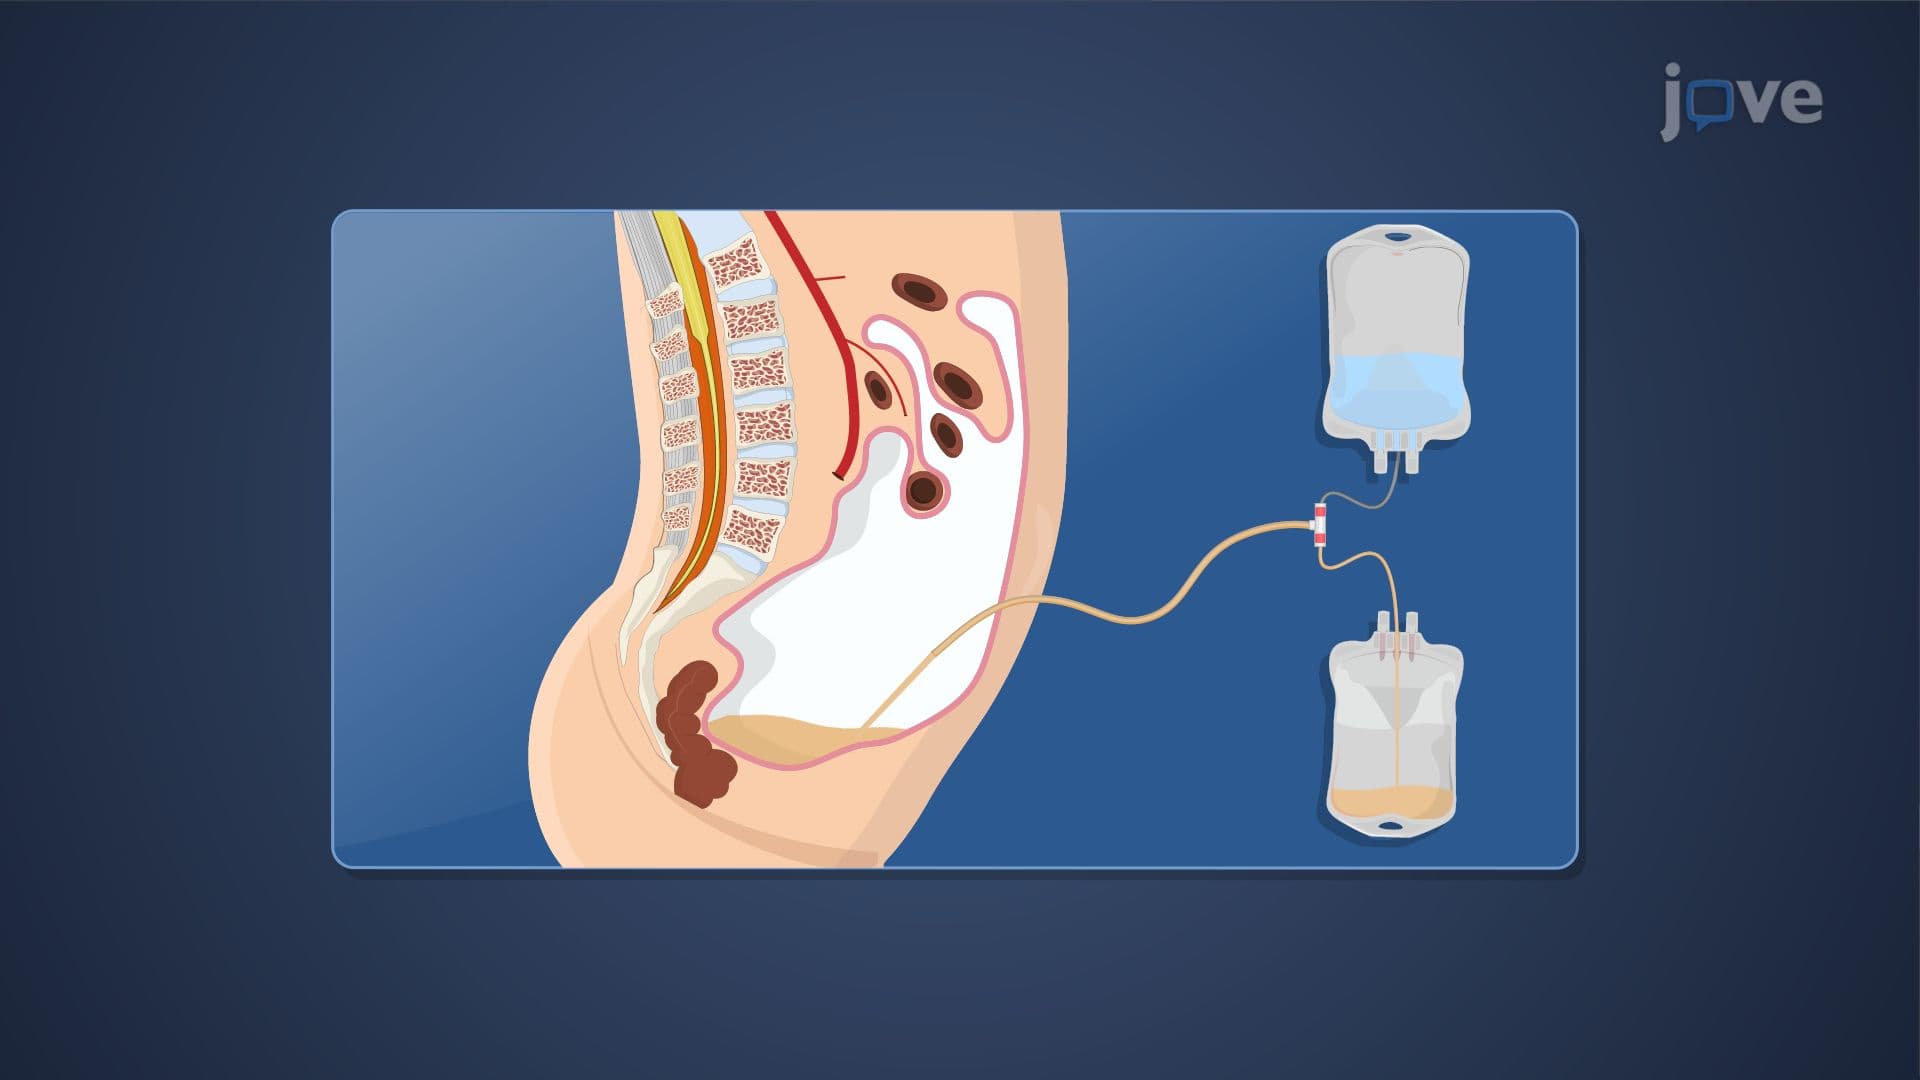
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Dialysis
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration