Related Experiment Video
Updated: Nov 2, 2025


Posterior Approach for Debridement of the Psoas Abscess
Published on: March 2, 2020
[Avulsion injuries of the adductors and iliopsoas]
Heinz Lohrer1,2
1Zentrum für Sportorthopädie, ESN - European Sportscare Network, Borsigstr. 2, 65205, Wiesbaden-Nordenstadt, Deutschland. lohrer@esn-ortho.de.

Abstract:
Avulsion injuries of the tendon-bone junction of the adductor longus are rare. Avulsions of the iliopsoas tendon insertion on the lesser trochanter are even rarer. Avulsion injuries of the adductor insertion occur predominantly in active athletes. Iliopsoas tendon avulsions are described mainly in nonathletes, in old age and frequently with no triggering event. In these cases possible underlying pathologies (e.g. tumor or metastases in the lesser trochanter) must be ruled out. In the literature no generally accepted recommendations for treatment of these injuries can be found because only a few retrospective anecdotal case reports and case studies have been published. For this reason, it is mostly unclear if and when a conservative or operative approach is indicated.A PubMed/Medline literature search resulted in 86 articles for iliopsoas avulsions and 155 hits for adductor tendon avulsions. Accordingly, both injuries can basically be treated conservatively. A surgical treatment is recommended only occasionally when conservative treatment fails and when the adductor insertion or the apophysis of the lesser trochanter is dislocated more than 2 cm after avulsion. Reinsertion for adductor longus tendon avulsion injuries is usually performed by open repair using various anchor systems, while extensive avulsion injuries or non-unions of the apophysis of the lesser trochanter are treated by refixation by cannulated screw systems or resection and anchor refixation of the tendon. The postoperative outcome in most cases is described as good or very good (excellent). No major complications were reported in both groups.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025
Related Concept Videos
 01:20
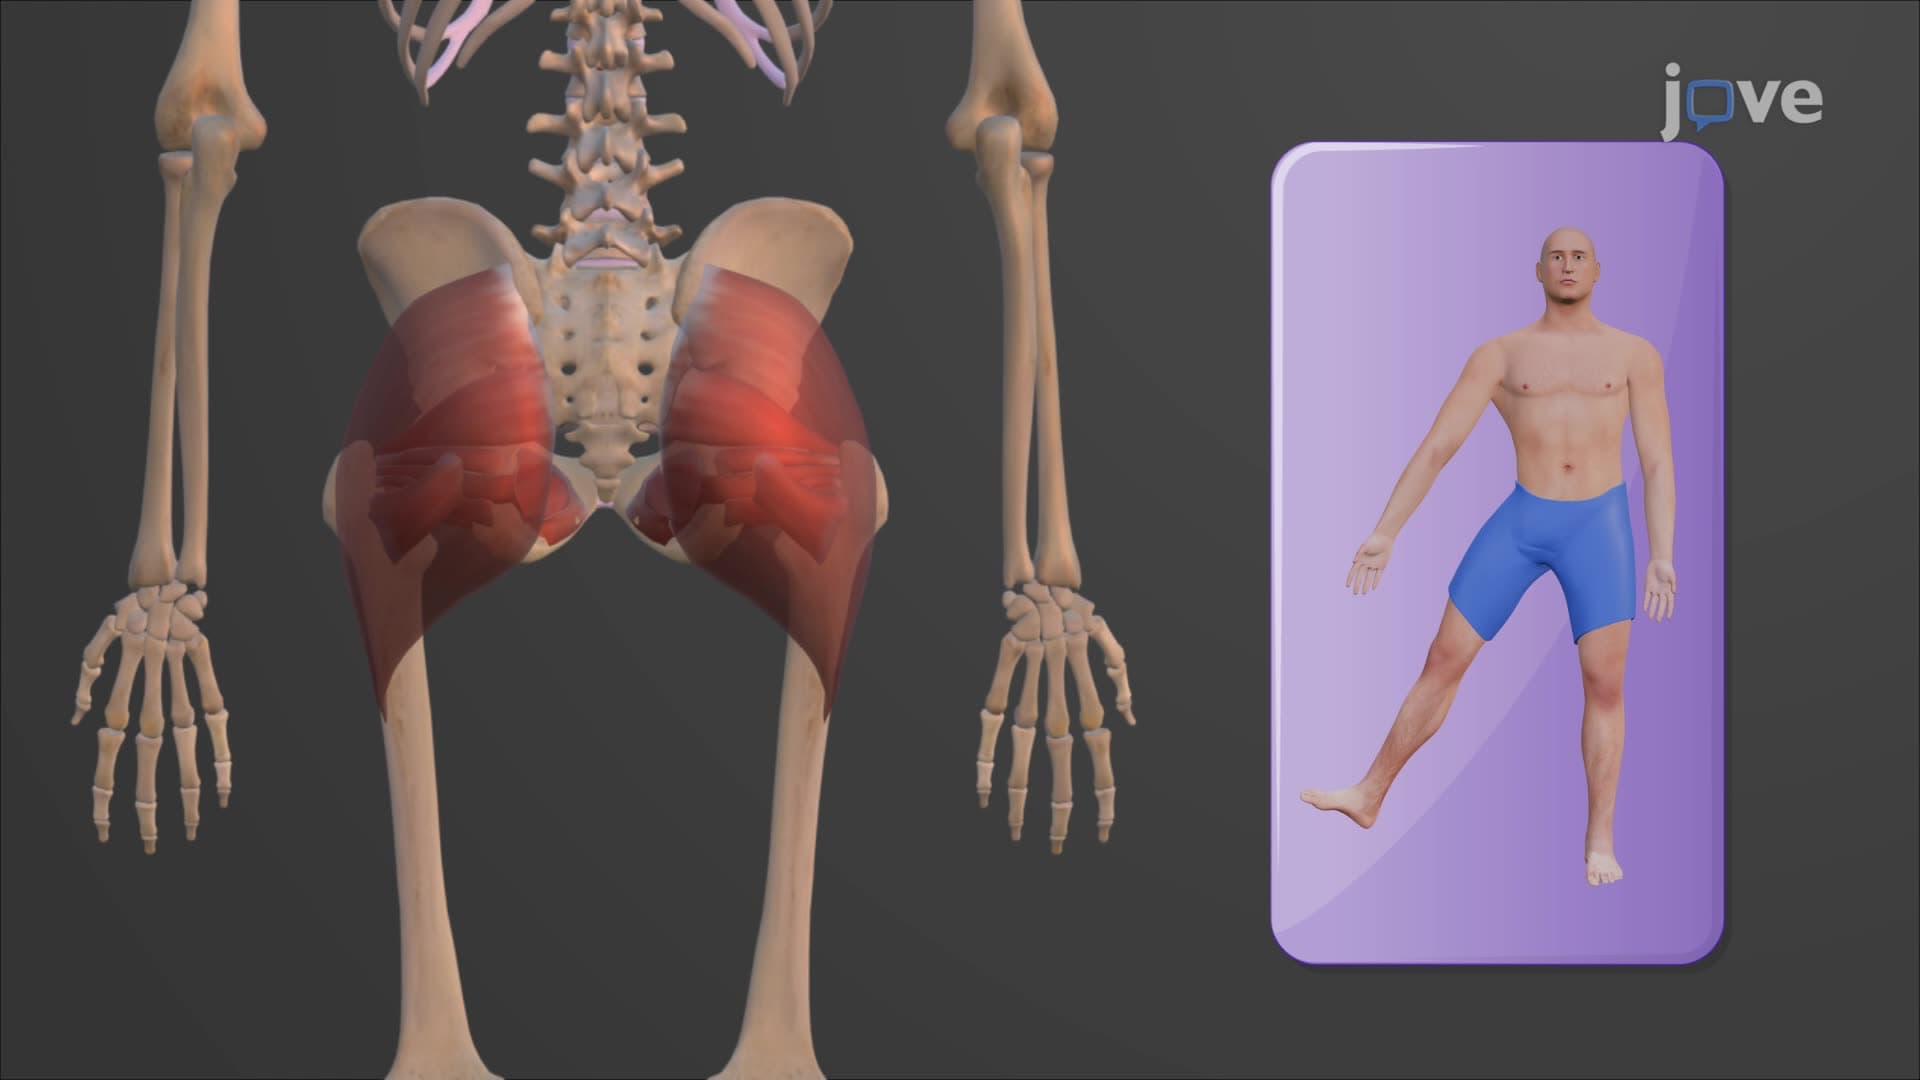
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar...
 01:23
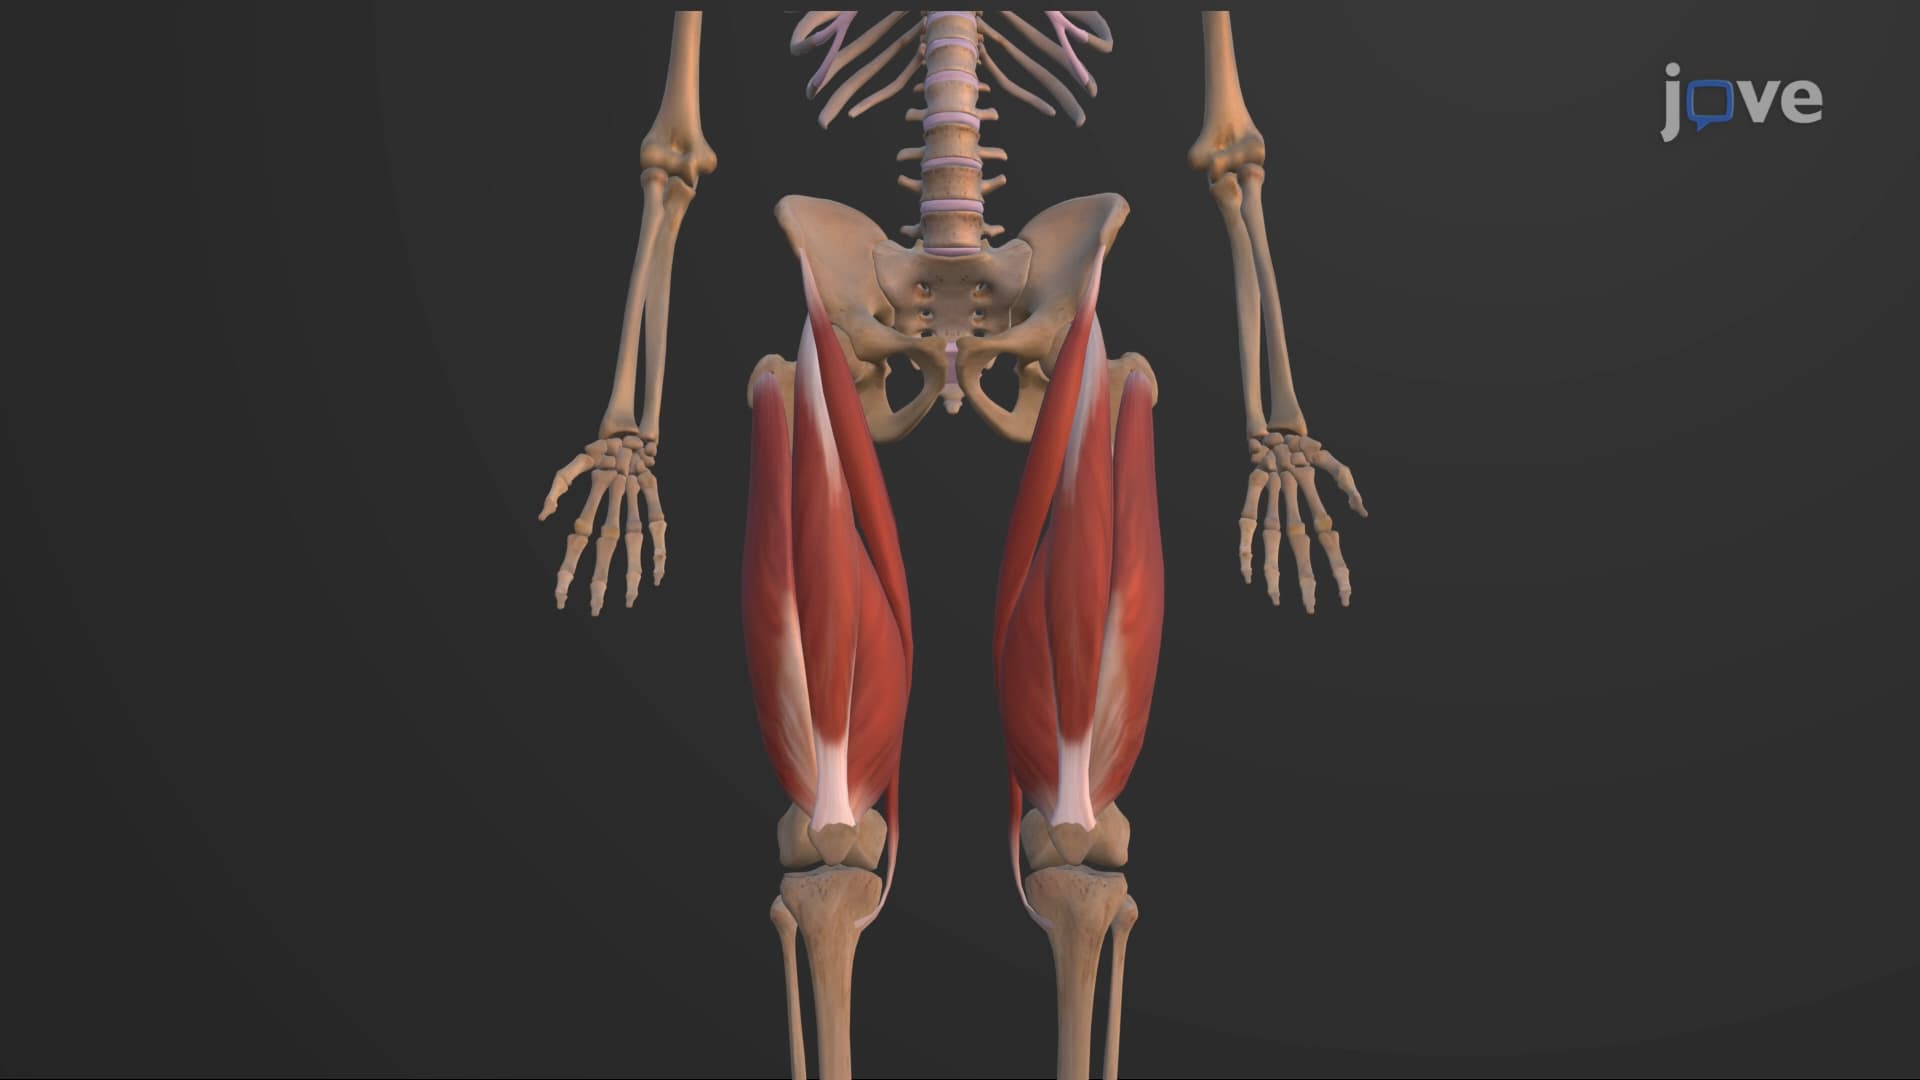
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:20
Arteries of Lower Limbs