Related Experiment Video
Updated: Nov 2, 2025

3D Ultrasound Imaging: Fast and Cost-effective Morphometry of Musculoskeletal Tissue
Published on: November 27, 2017
Reliability of Processing 3-D Freehand Ultrasound Data to Define Muscle Volume and Echo-intensity in Pediatric Lower
Britta Hanssen1, Nathalie De Beukelaer2, Simon-Henri Schless3
1Department of Rehabilitation Sciences, KU Leuven, Leuven, Belgium; Clinical Motion Analysis Laboratory, University Hospitals Leuven, Pellenberg, Belgium; Department of Rehabilitation Sciences, Ghent University, Ghent, Belgium.

Insights
Muscle volume and echo-intensity in children
Area of Science:
- Biomedical Engineering
- Musculoskeletal Imaging
Background:
- Reliable assessment of muscle characteristics is crucial for understanding development and conditions like cerebral palsy.
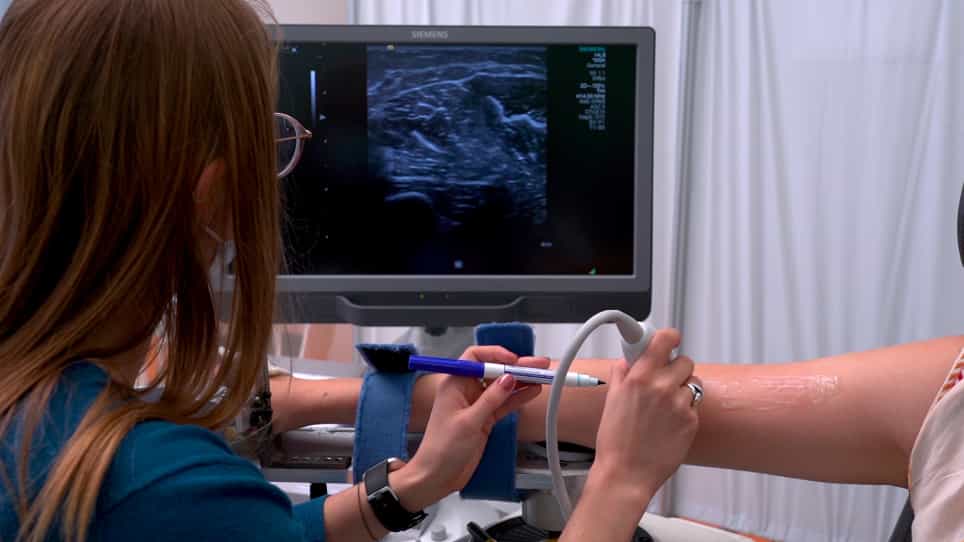
- 3-D freehand ultrasonography offers a non-invasive method for muscle evaluation.
Purpose of the Study:
- To assess the processor reliability of estimating muscle volume and echo-intensity.
- To evaluate these measures in typically developing children and those with spastic cerebral palsy.
Main Methods:
- Utilized 3-D freehand ultrasonography to scan rectus femoris, tibialis anterior, and semitendinosus muscles.
- Conducted intra- and inter-processor analyses using intra-class correlation coefficients (ICCs) and relative standard errors of measurement (SEM%).
Main Results:
- High intra-processor reliability for muscle volume (ICCs 0.943-0.997) and echo-intensity (ICCs >0.947).
- Good inter-processor reliability for muscle volume (ICCs 0.853-0.988) and echo-intensity (ICCs >0.947).
- Low relative SEMs (<8.97% for volume, <4% for echo-intensity) indicate precision.
Conclusions:
- Muscle volume and echo-intensity can be reliably measured using 3-D ultrasonography in both typically developing children and those with cerebral palsy.
- The necessity of a single processor depends on the magnitude of expected changes or differences in measurements.
Abstract:
This investigation assessed the processer reliability of estimating muscle volume and echo-intensity of the rectus femoris, tibialis anterior and semitendinosus. The muscles of 10 typically developing children (8.15 [1.40] y) and 15 children with spastic cerebral palsy (7.67 [3.80] y; Gross Motor Function Classification System I = 5, II = 5, III = 5) were scanned with 3-D freehand ultrasonography. For the intra-processer analysis, the intra-class correlations coefficients (ICCs) for muscle volume ranged from 0.943-0.997, with relative standard errors of measurement (SEM%) ranging from 1.24%-8.97%. For the inter-processer analysis, these values were 0.853 to 0.988 and 3.47% to 14.02%, respectively. Echo-intensity had ICCs >0.947 and relative SEMs <4% for both analyses. Muscle volume and echo-intensity can be reliably extracted for the rectus femoris, semitendinosus and tibialis anterior in typically developing children and children with cerebral palsy. The need for a single processer to analyze all data is dependent on the size of the expected changes or differences.