Related Experiment Video
Updated: Nov 2, 2025

Tissue Collection and RNA Extraction from the Human Osteoarthritic Knee Joint
Published on: July 22, 2021
Knee Joint Line Obliquity Causes Tibiofemoral Subluxation That Alters Contact Areas and Meniscal Loading
Dong Wang1,2, Lukas Willinger1, Kiron K Athwal1
1The Biomechanics Group, Department of Mechanical Engineering, Imperial College London, London, UK.

Background:
Little scientific evidence is available regarding the effect of knee joint line obliquity (JLO) before and after coronal realignment osteotomy.
Hypotheses:
Higher JLO would lead to abnormal relative position of the femur on the tibia, a shift of the joint contact areas, and elevated joint contact pressures.
Study Design:
Descriptive laboratory study.
Methods:
10 fresh-frozen human cadaveric knees (age, 59 ± 5 years) were axially loaded to 1500 N in a materials testing machine with the joint line tilted 0°, 4°, 8°, and 12° varus ("downhill" medially) and valgus, at 0° and 20° of knee flexion. The mechanical compression axis was aligned to the center of the tibial plateau. Contact pressure and contact area were recorded by pressure sensors inserted between the tibia and femur below the menisci. Changes in relative femoral and tibial position in the coronal plane were obtained by an optical tracking system.
Results:
Both medial and lateral JLO caused significant tibiofemoral subluxation and pressure distribution changes. Medial (varus) JLO caused the femur to subluxate medially down the coronal slope of the tibial plateau, and vice versa for lateral (valgus) downslopes (P < .01), giving a 6-mm range of subluxation. The areas of peak pressure moved 12 mm and 8 mm across the medial and lateral condyles, onto the downhill meniscus and the "uphill" tibial spine. Changes in JLO had only small effects on maximum contact pressures.
Conclusion:
A 4° change of JLO during load bearing caused significant mediolateral tibiofemoral subluxation. The femur slid down the slope of the tibial plateau to abut the tibial eminence and also to rest on the downhill meniscus. This caused large movements of the tibiofemoral contact pressures across each compartment.
Clinical Relevance:
These results provide important information for understanding the consequences of creating coronal JLO and for clinical practice in terms of osteotomy planning regarding the effect on JLO. This information provides guidance regarding the choice of single- or double-level osteotomy. Excessive JLO alteration may cause abnormal tibiofemoral joint articulation and chondral or meniscal loading.
More Related Videos
 08:40
Author Spotlight: Investigating the Mechanism of Action of Acupotomy in Treating Knee Osteoarthritis
Published on: October 20, 2023
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025
Related Concept Videos
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:23
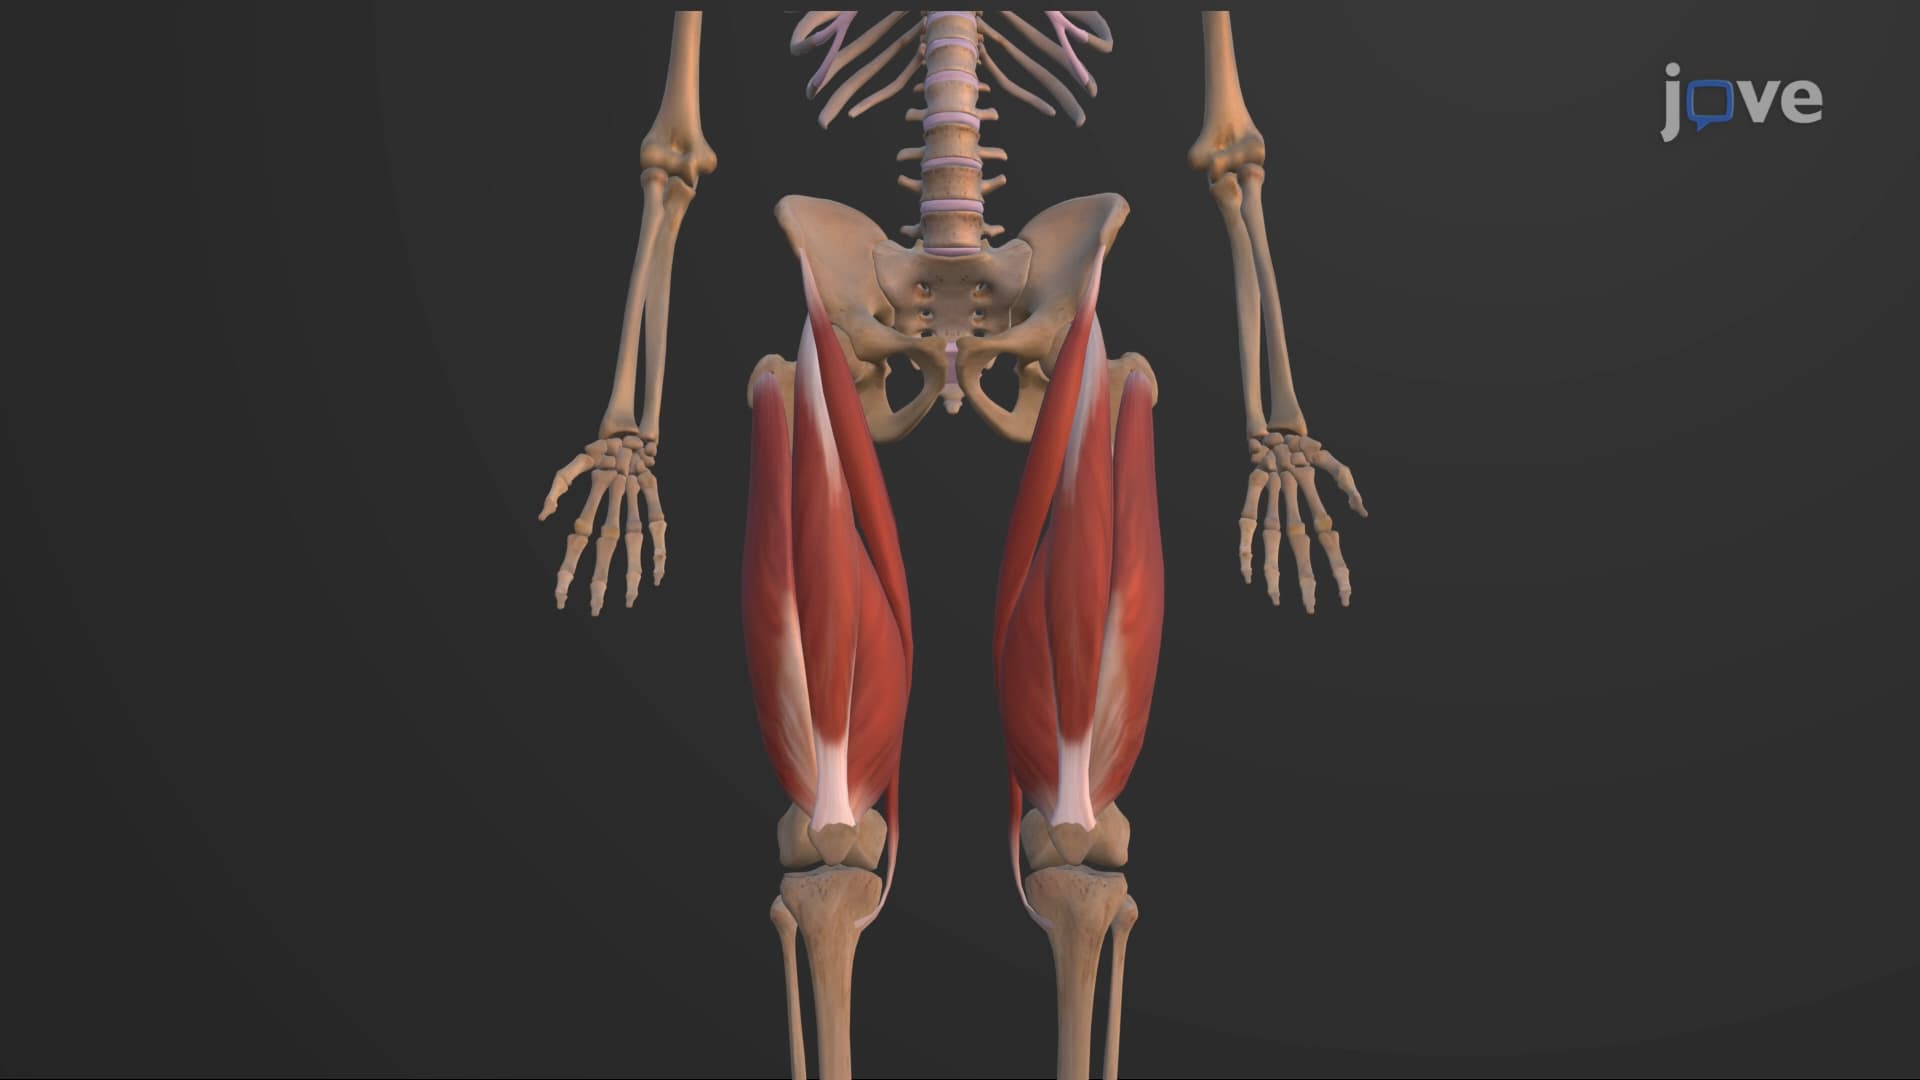
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed...
 01:10
Bones of the Lower Limb: Tibia and Fibula
 01:10
Ankle Joint
 01:20
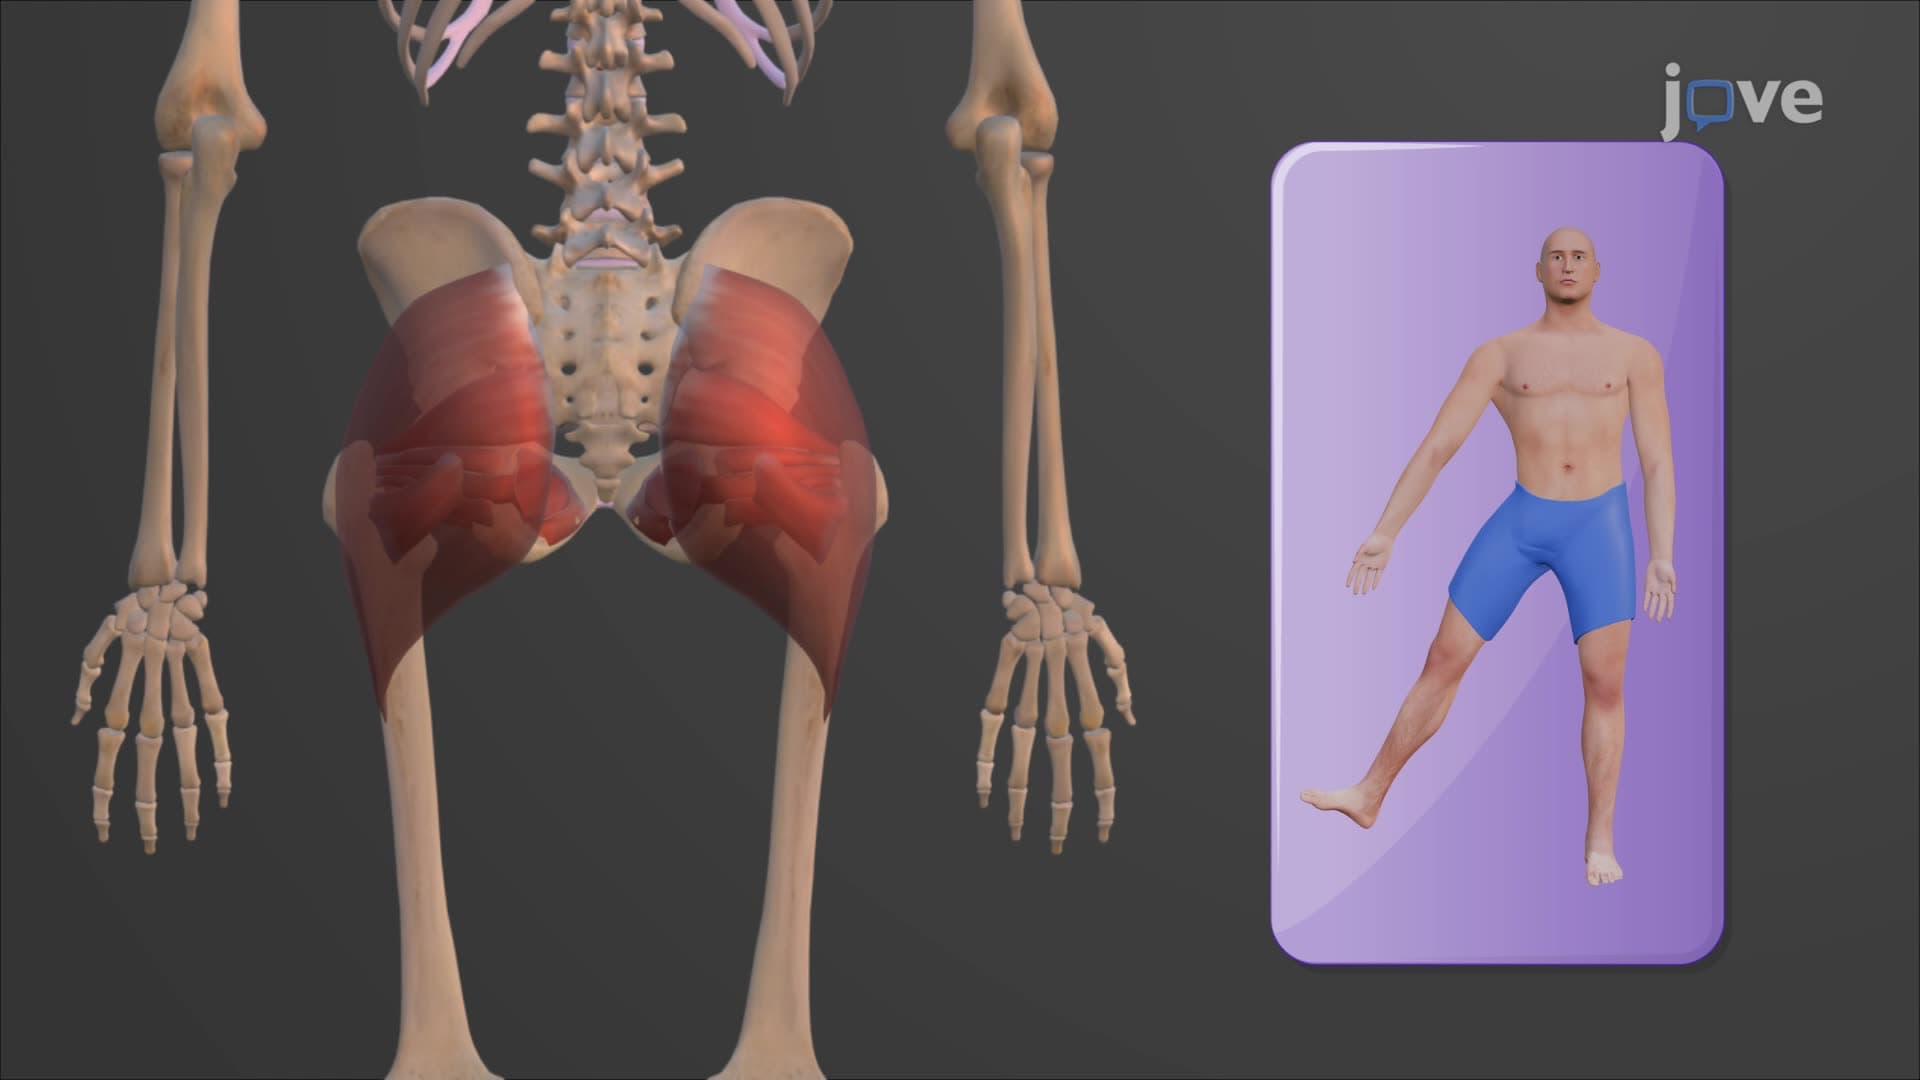
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar...