Related Experiment Video
Updated: Nov 2, 2025
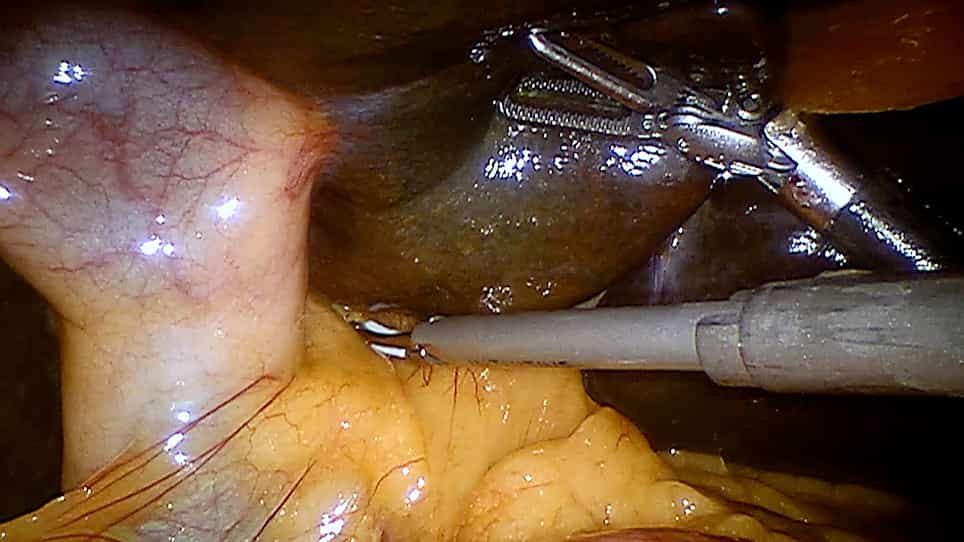

Robotic Taj Mahal Hepatectomy for Hilar Cholangiocarcinoma
Published on: July 14, 2022
Surgical Strategies for Bismuth Type I and II Hilar Cholangiocarcinoma: Impact on Long-Term Outcomes
Xu-Feng Zhang1,2, Nan Zhang1, Diamantis I Tsilimigras2
1Department of Hepatobiliary Surgery and Institute of Advanced Surgical Technology and Engineering, The First Affiliated Hospital of Xi'an Jiaotong University, Xi'an, China.

Background:
The surgical approach to treat Bismuth type I and II hilar cholangiocarcinoma (HCCA) has been a topic of debate. We sought to characterize whether bile duct resection (BDR) with or without concomitant hepatic resection (HR) was associated with R0 margin status, as well as define the impact of HR+BDR versus BDR alone on long-term survival.
Methods:
Patients who underwent curative-intent HR+BDR for HCCA between 2000 and 2014 were identified from a multi-institutional database. Perioperative and long-term outcomes were compared among patients who underwent BDR only, BDR+left hepatic resection (LHR), and BDR+right hepatic resection (RHR) for Bismuth type I and II HCCA.
Results:
Among 257 patients with HCCA, 61 (23.7%) patients had a Bismuth type I (n=25, 41.0%) or II (n=36, 59.0%) lesion. The incidence of R0 resection after BDR only was the same as among patients after LHR and RHR (BDR 70.0% vs. BDR+LHR 71.4% vs. BDR+RHR 76.5%, p=0.891). In contrast, severe complications were more likely after LHR and RHR than BDR only (BDR 21.4% vs. BDR+LHR 60.0% and BDR+RHR 50.0%, p=0.041). Overall (median: BDR 20.9 vs. BDR+LHR 23.2 and BDR+RHR 25.0 months, p=0.213) and recurrence-free (median: BDR 13.4 vs. BDR+LHR 15.3 and BDR+RHR 25.0, p= 0.109) survival were comparable. On multivariable analysis, while CA19-9>37.0U/ml (Ref. CA19-9≤37.0U/ml, HR 3.2, 95% CI 1.1-9.4, p=0.035) and AJCC T3-T4 disease (Ref. T1-T2, HR 4.6, 95% CI 1.5-13.7, p=0.007) were associated with long-term survival, surgical approach was not (BDR+LHR: HR 1.0, 95% CI 0.5-2.2, p=0.937; BDR+RHR: HR 0.6, 95% CI 0.3-1.3, p=0.197).
Conclusion:
R0 resection, overall survival, and recurrence-free survival were comparable among well-selected patients who had BDR versus BDR+HR for Bismuth type I and II HCCA.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease