Related Experiment Video
Updated: Nov 1, 2025


Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Low noncarbonic buffer power amplifies acute respiratory acid-base disorders in patients with sepsis: an in vitro
Thomas Langer1,2, Serena Brusatori3, Eleonora Carlesso3
1Department of Medicine and Surgery, University of Milan-Bicocca, Monza, Italy.

Abstract:
Patients with sepsis have typically reduced concentrations of hemoglobin and albumin, the major components of noncarbonic buffer power (β). This could expose patients to high pH variations during acid-base disorders. The objective of this study is to compare, in vitro, noncarbonic β of patients with sepsis with that of healthy volunteers, and evaluate its distinct components. Whole blood and isolated plasma of 18 patients with sepsis and 18 controls were equilibrated with different CO2 mixtures. Blood gases, pH, and electrolytes were measured. Noncarbonic β and noncarbonic β due to variations in strong ion difference (βSID) were calculated for whole blood. Noncarbonic β and noncarbonic β normalized for albumin concentrations (βNORM) were calculated for isolated plasma. Representative values at pH = 7.40 were compared. Albumin proteoforms were evaluated via two-dimensional electrophoresis. Hemoglobin and albumin concentrations were significantly lower in patients with sepsis. Patients with sepsis had lower noncarbonic β both of whole blood (22.0 ± 1.9 vs. 31.6 ± 2.1 mmol/L, P < 0.01) and plasma (0.5 ± 1.0 vs. 3.7 ± 0.8 mmol/L, P < 0.01). Noncarbonic βSID was lower in patients (16.8 ± 1.9 vs. 24.4 ± 1.9 mmol/L, P < 0.01) and strongly correlated with hemoglobin concentration (r = 0.94, P < 0.01). Noncarbonic βNORM was lower in patients [0.01 (-0.01 to 0.04) vs. 0.08 (0.06-0.09) mmol/g, P < 0.01]. Patients with sepsis and controls showed different amounts of albumin proteoforms. Patients with sepsis are exposed to higher pH variations for any given change in CO2 due to lower concentrations of noncarbonic buffers and, possibly, an altered buffering function of albumin. In both patients with sepsis and healthy controls, electrolyte shifts are the major buffering mechanism during respiratory acid-base disorders.NEW & NOTEWORTHY Patients with sepsis are poorly protected against acute respiratory acid-base derangements due to a lower noncarbonic buffer power, which is caused both by a reduction in the major noncarbonic buffers, i.e. hemoglobin and albumin, and by a reduced buffering capacity of albumin. Electrolyte shifts from and to the red blood cells determining acute variations in strong ion difference are the major buffering mechanism during acute respiratory acid-base disorders.
More Related Videos

Related Concept Videos
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 02:58
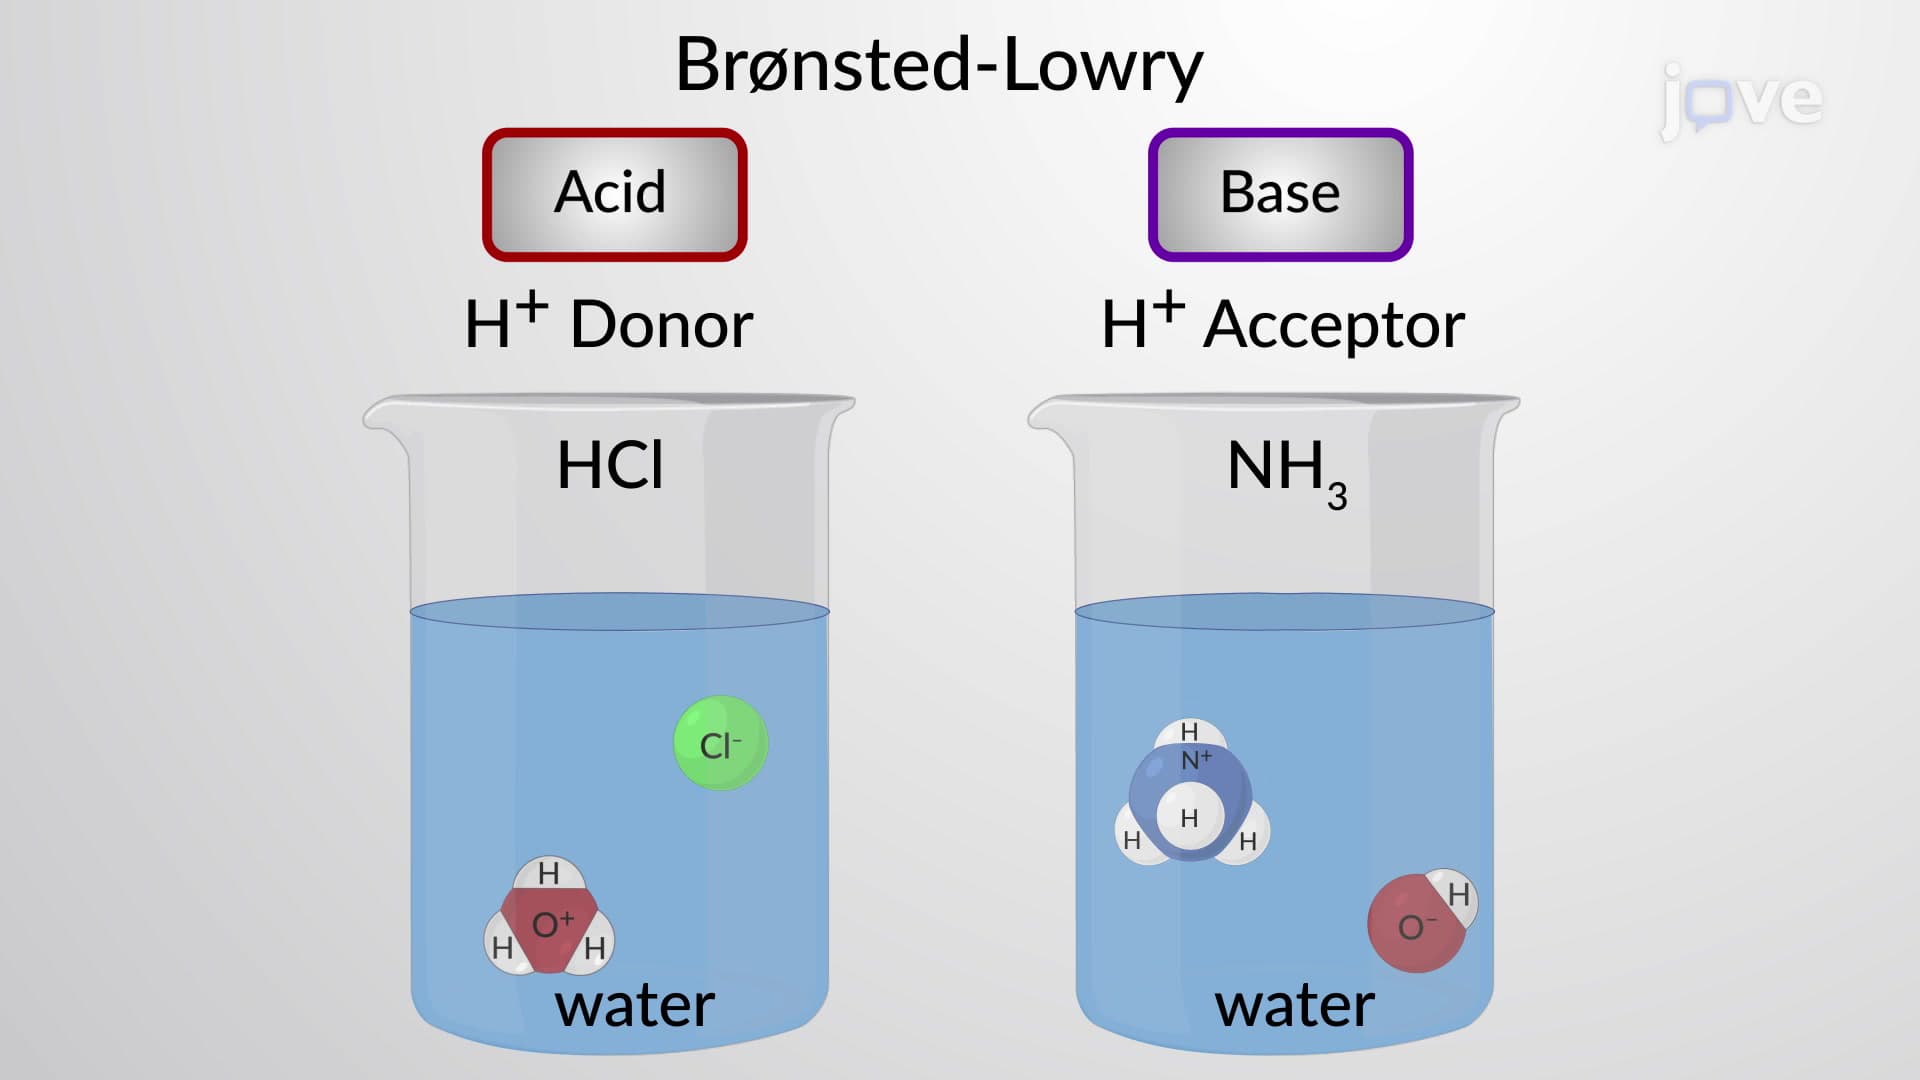
Bronsted-Lowry Acids and Bases