Related Experiment Video
Updated: Nov 1, 2025

Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Assessment of the Effects of a High Amikacin Dose on Plasma Peak Concentration in Critically Ill Children
Rym Medjebeur Hanna1, Michael Levy2, Emmanuelle Bille3
1Service de Réanimation et Surveillance Continue Médico-chirugicale Pédiatriques, Hôpital Necker Enfants Malades, Assistance Publique-Hôpitaux de Paris, Université Paris Descartes, Paris, France.

Insights
Most critically ill children (70%) did not reach target amikacin plasma peak concentrations (Cmax) with the standard 30 mg/kg/day dose. Higher kidney function and lower blood urea were linked to sub-therapeutic amikacin levels.
Area of Science:
- Pediatric Intensive Care
- Pharmacokinetics
- Infectious Diseases
Background:
- Amikacin is a critical antibiotic for severe pediatric infections.
- Optimizing amikacin dosing in critically ill children is essential for efficacy and safety.
- Current dosing guidelines may not achieve therapeutic amikacin plasma peak concentrations (Cmax) in this population.
Purpose of the Study:
- To determine the incidence of sub-therapeutic amikacin Cmax (< 60 mg·L⁻¹) in critically ill children.
- To identify factors associated with low amikacin Cmax.
- To assess the occurrence of acute kidney injury (AKI) in this patient group.
Main Methods:
- Retrospective observational study in two French pediatric intensive care units.
- Inclusion of critically ill children receiving amikacin 30 mg·kg⁻¹·day⁻¹ with Cmax measurement.
- Collection of clinical, biological, and amikacin concentration data.
Main Results:
- 70% (21/30) of children had amikacin Cmax < 60 mg·L⁻¹.
- High estimated glomerular filtration rate and low blood urea concentration were associated with low Cmax.
- Acute kidney injury (AKI) occurred in 21% of patients.
Conclusions:
- The standard amikacin dose of 30 mg·kg⁻¹·day⁻¹ frequently fails to achieve target Cmax in critically ill children.
- Further research is needed to develop population pharmacokinetic models for optimized amikacin dosing.
- Individualized dosing strategies may be required to improve amikacin target attainment and patient outcomes.
Objectives:
This study aimed to assess the incidence of amikacin plasma peak concentration (Cmax) below 60 mg·L-1 in critically ill children receiving an amikacin dosing regimen of 30 mg kg-1·day-1. Secondary objectives were to identify factors associated with low Cmax and to assess the incidence of acute kidney injury (AKI).
Methods:
A retrospective observational study was performed in two French pediatric intensive care units. All admitted children who received 30 mg·kg-1 amikacin and had a Cmax measurement were eligible. Clinical and biological data, amikacin dose, and concentrations were collected.
Results:
In total, 30 patients were included, aged from 3 weeks to 7 years. They received a median amikacin dosage of 30 mg kg-1·day-1 (range 29-33) based on admission body weight (BW), corresponding to 27 mg kg-1·day-1 (range 24-30) based on actual BW. Cmax was < 60 mg·L-1 in 21 (70%) children and none had a Cmax ≥ 80 mg·L-1. Among the 15 patients with a measured minimum inhibitory concentration (MIC), 13 (87%) had a Cmax/MIC ratio > 8. Univariate analysis showed that factors associated with Cmax < 60 mg·L-1 were high estimated glomerular filtration rate (p = 0.015) and low blood urea concentration (p = 0.001). AKI progression or occurrence was observed after amikacin administration in two (7%) and six (21%) patients, respectively.
Conclusions:
Despite the administration of the maximal recommended amikacin dose, Cmax was below the pharmacokinetic target in 70% of our pediatric population. Further studies are needed to develop a pharmacokinetic model in a population of critically ill children to optimize target attainment.


Related Concept Videos
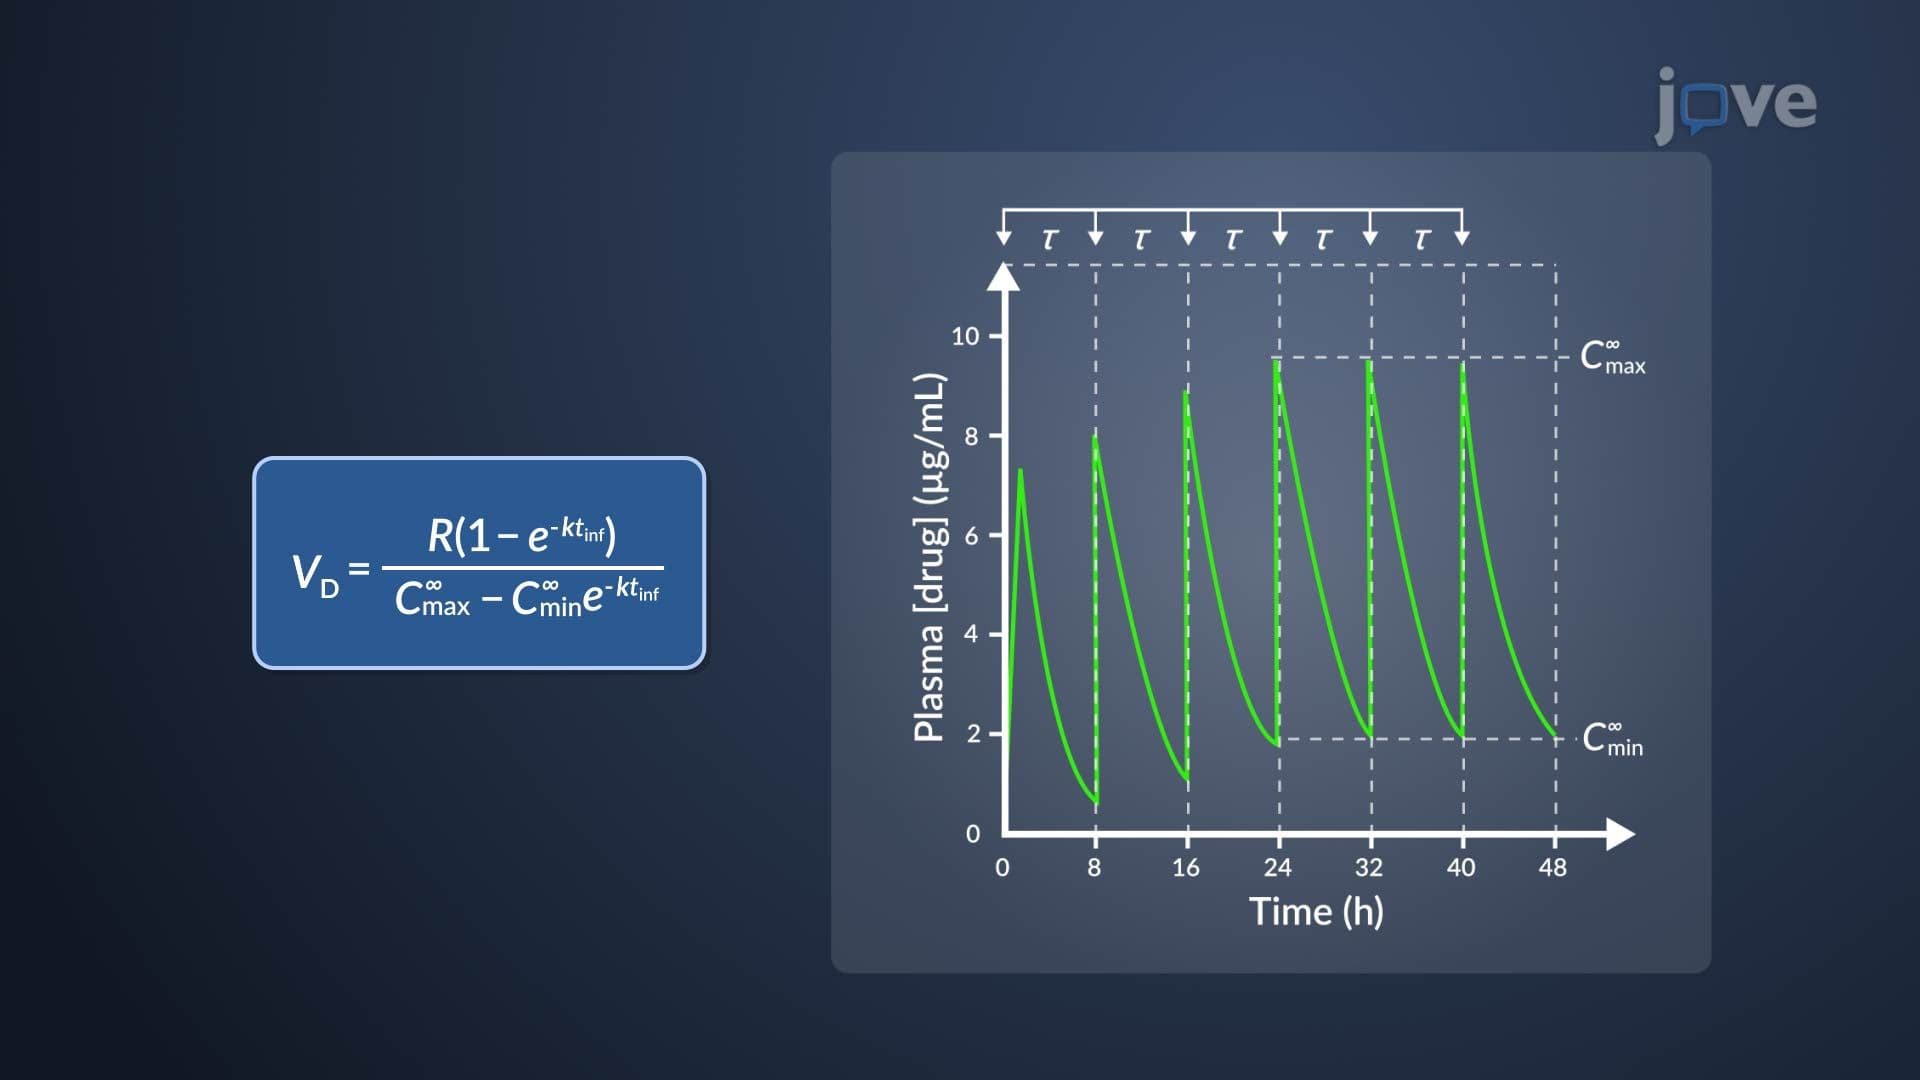 01:20
Estimation of k and VD of Aminoglycosides
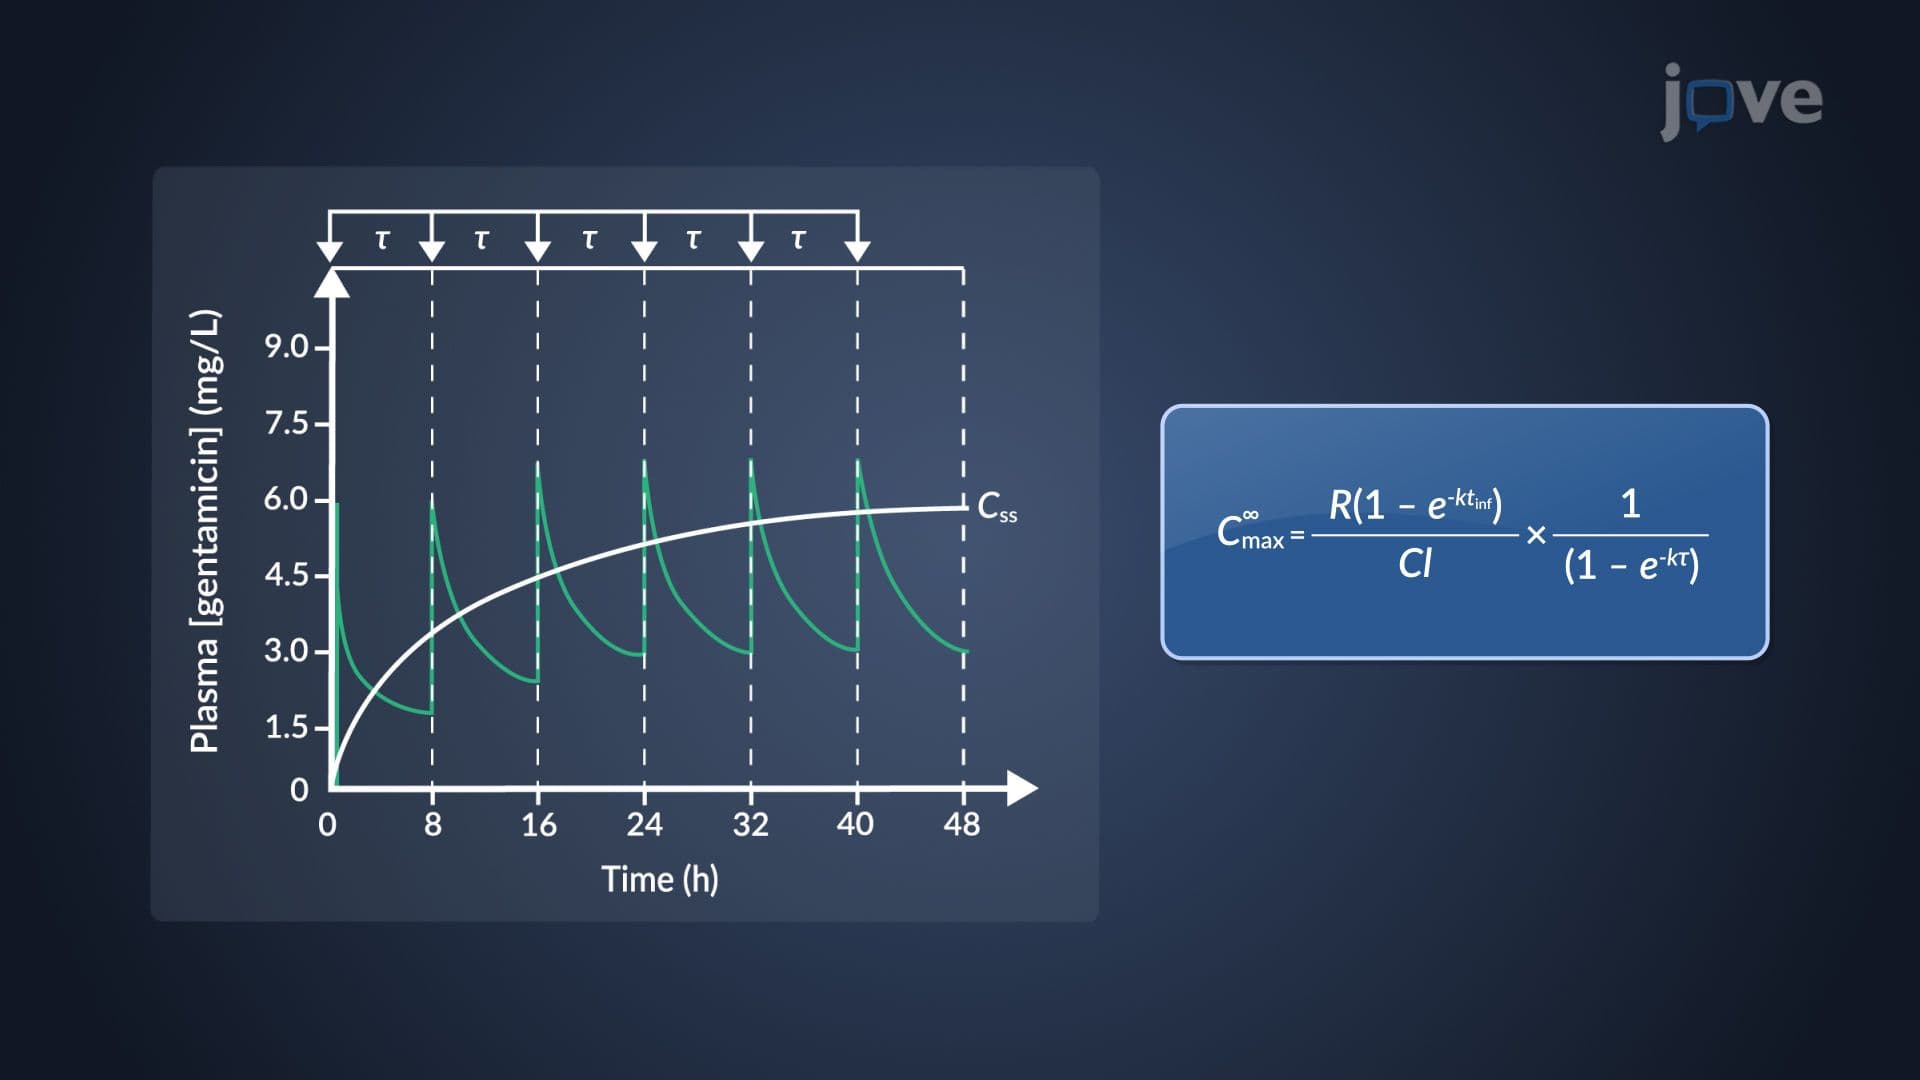 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
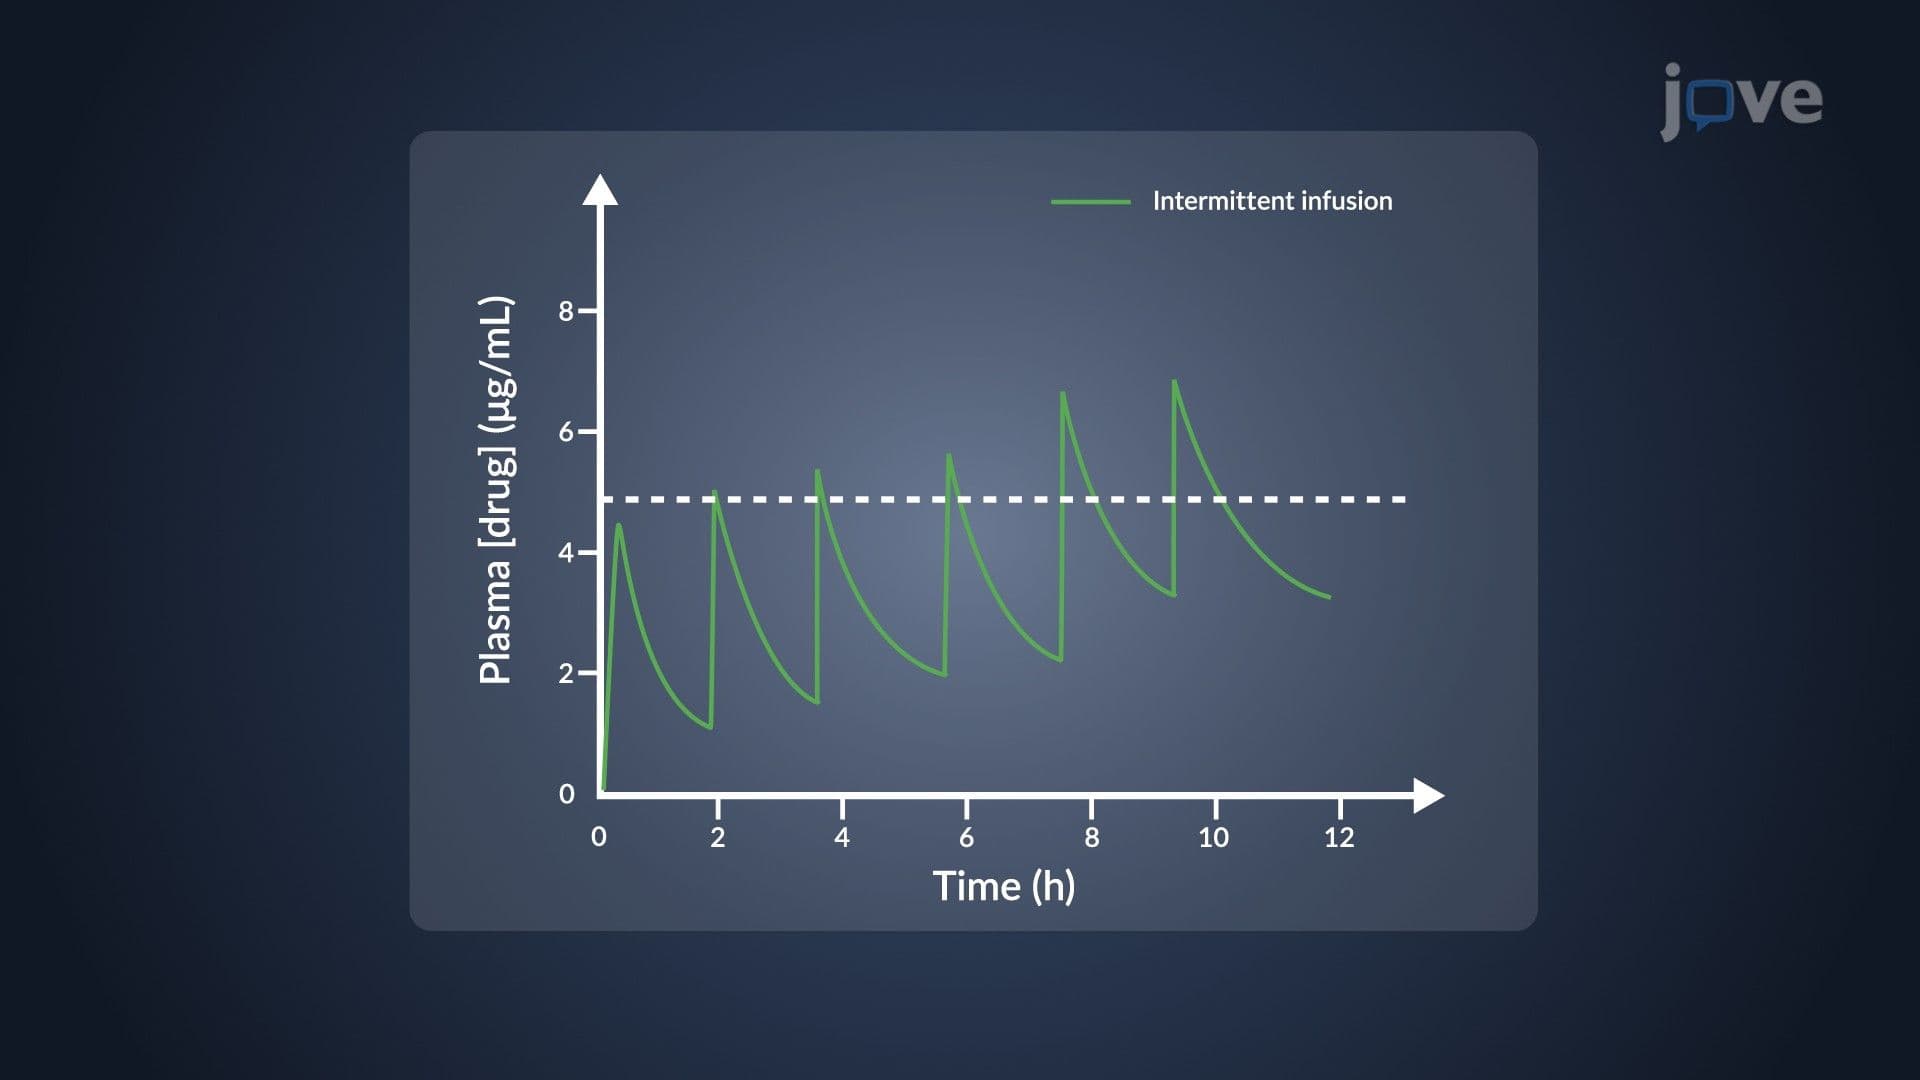 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism