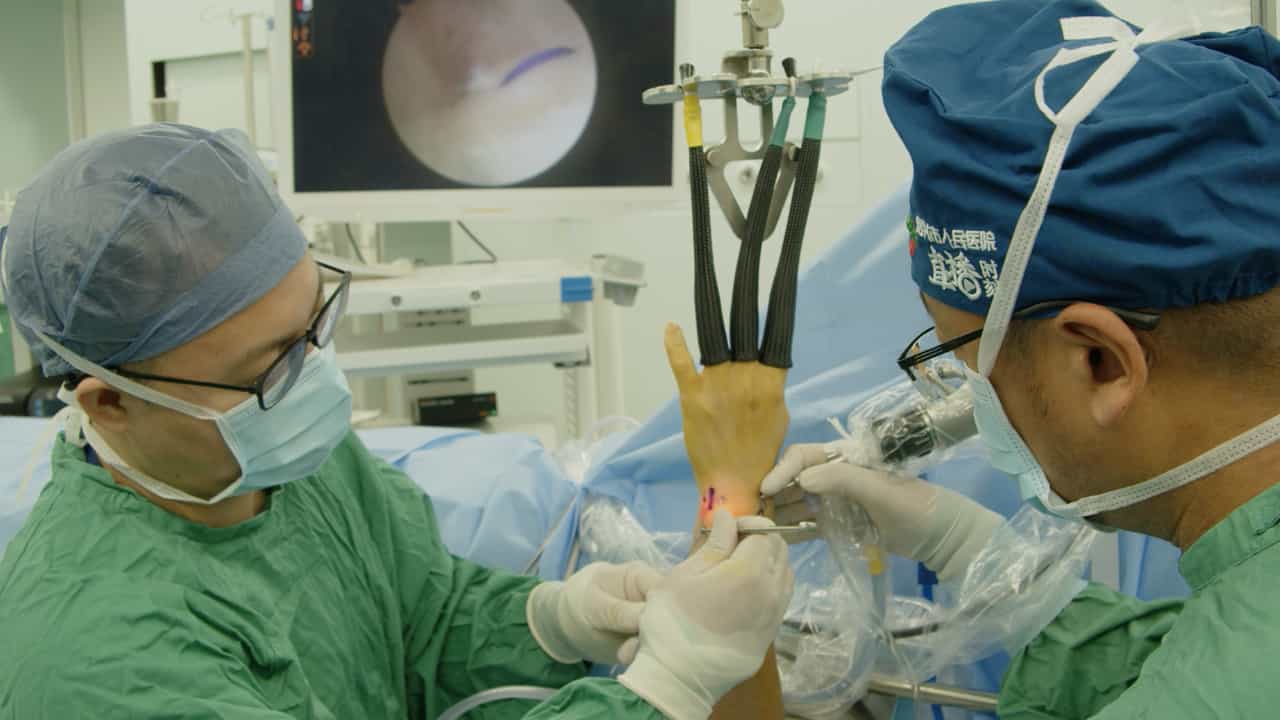
A dorsal approach for the distal-to-proximal internal fixation of oblique scaphoid fractures
Related Experiment Video
Updated: Nov 1, 2025
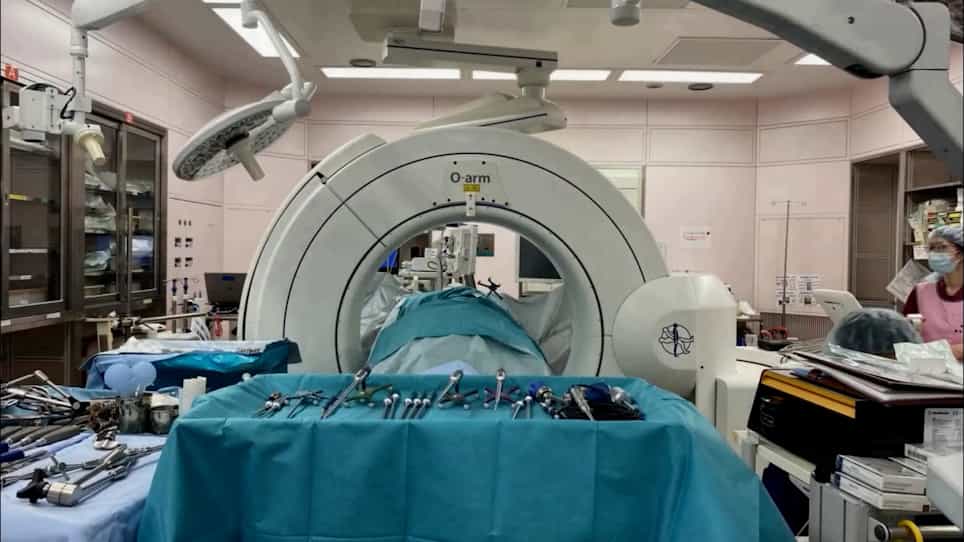
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Takuya Tada1, Kenji Onuma1, Koji Sukegawa1
1Department of Orthopaedic Surgery, Kitasato University School of Medicine, Japan.

Introduction:
Two methods using cannulated headless screws can be used for scaphoid fractures: Inserting the screw through the distal fragment and then into the proximal fragment through a palmar approach under direct vision or fluoroscopic guidance and inserting the screw in the proximal-to-distal direction through a dorsal approach with fluoroscopic guidance. These methods are sometimes difficult to use in oblique fractures when trying to achieve screw fixation perpendicular to the fracture plane.The most common mechanism of injury in the scaphoid fracture is forceful wrist hyperextension and punching something. Less commonly, a direct blow to the wrist also can cause a fracture. The mechanism of fracture by a direct blow to the wrist is not completely clear.
Case Presentation:
We experienced two rare cases of scaphoid fracture in goalkeepers sustained when they saved a goal by contacting the soccer ball with the palm of their hand. Both fractures were proximal oblique fractures. We performed through a dorsal approach to insert the screws in the distal-to-proximal direction under direct vision assisted with fluoroscopy. Bone union was noted after surgery in both cases. They returned to their occupations without wrist pain.We investigated the relationship between the fracture line and wrist position using a fresh cadaver. The experiment revealed that the fracture line of the scaphoid matched the dorsal edge of the articular surface of the radius with the wrist in 30° of dorsiflexion and 20° of ulnar deviation.
Conclusion:
In this report, we reported rare cases of scaphoid fracture due to contact with the soccer ball on the palm. We propose a surgical approach for an oblique fracture of the proximal scaphoid that used guide wires and screws, but was performed through a dorsal, and not palmar, approach to insert the screws in the distal-to-proximal direction.We presume that coronal shear stress to the scaphoid bone occurred when the palm contacted the ball with the wrist positioned at 30° dorsiflexion and 20° ulnar deviation.