Related Experiment Video
Updated: Nov 1, 2025
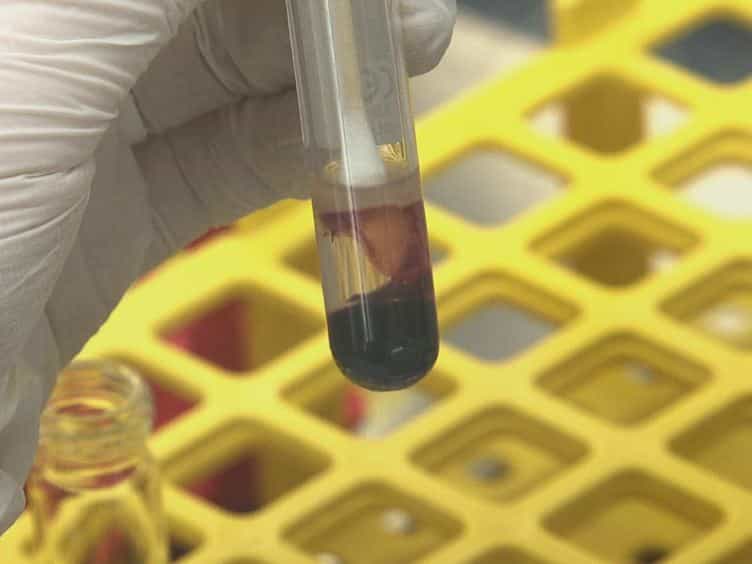

One-day Workflow Scheme for Bacterial Pathogen Detection and Antimicrobial Resistance Testing from Blood Cultures
Published on: July 9, 2012
Validation of neonatal and paediatric antimicrobial stewardship treatment algorithms in rapid diagnostic-detected
Amy Kruger Howard1, Kristine A Parbuoni1, Kimberly Claeys1
1Department of Pharmacy Practice and Science, University of Maryland School of Pharmacy, Baltimore, MD, USA.

Objectives:
Blood culture rapid diagnostic testing (RDT) aids in early organism identification and resistance gene detection. This information allows quicker transition to tailored antimicrobial therapy, improved patient outcomes and prevention of antimicrobial resistance. An antimicrobial treatment algorithm based on RDT results and local antibiograms can serve as a valuable clinical decision-support tool. This study assessed the proportion of appropriate antibiotic therapy recommendations using a novel paediatric RDT-guided treatment algorithm compared with standard care (SC) in paediatric bacteraemia.
Methods:
This was a retrospective, observational study of admitted paediatric patients who received antibiotics for RDT-confirmed bacteraemia. Appropriateness of SC was compared with algorithm-recommended treatment. Antimicrobial appropriateness was defined as in vitro susceptibility to the organism identified through traditional microbiology. Clinical appropriateness took into consideration the ability to tailor therapy within 12 h of RDT results. Appropriateness was evaluated by two blinded, independent reviewers.
Key Findings:
Eighty-six blood cultures were included with 15 unique Gram-positive and Gram-negative species or genus identified. Comparative antimicrobial appropriateness of SC and algorithm-recommended treatment was 94.2% (81/86) and 100% (86/86), respectively (P = 0.06). Clinical assessment determined 39.5% (34/86) of SC patients were on appropriate therapy within 12 h of RDT result. Algorithm-recommended therapy was clinically appropriate in 97.7% (84/86) of patients (P < 0.001). There was a median time savings of 42.7 h (IQR 40.6, 49.4) for the patients able to be de-escalated as compared with waiting on final sensitivities.
Conclusions:
Algorithm-guided treatment may allow most patients to be de-escalated to organism-tailored therapy earlier in their therapeutic course.
More Related Videos
 09:07
Author Spotlight: Accelerating Diagnostic Accuracy with Direct Identification of Gram-Negatives from Blood Culture Bottles
Published on: May 24, 2024
 11:25
Preparation of a Blood Culture Pellet for Rapid Bacterial Identification and Antibiotic Susceptibility Testing
Published on: October 15, 2014
