Related Experiment Video
Updated: Oct 31, 2025


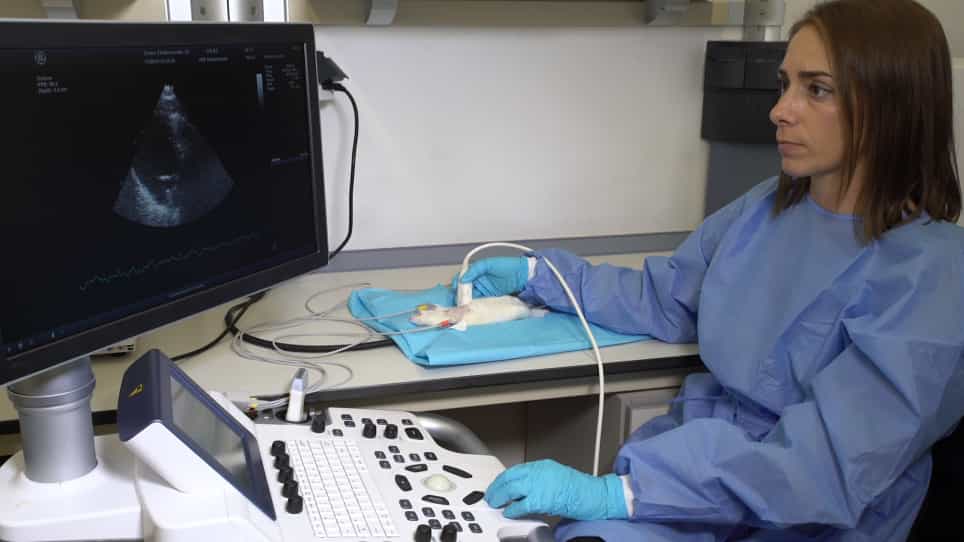
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
Physiological significance of pre- and post-ejection left ventricular tissue velocities and relations to mitral and
Asbjørn Støylen1,2, Annichen Søyland Daae1,2
1Department of Circulation and Medical Imaging, Norwegian University of Science and Technology, Trondheim, Norway.

Background:
Tissue Doppler shows short duration velocity spikes during pre- and post-ejection (protodiastole). They have been assumed to be isovolumic contraction and relaxation movements, but this is not in accordance with newer studies.
Methods:
We examined 22 healthy volunteers. Valve closures and openings were determined from spectral Doppler from LVOT and mitral inflow and transferred to colour tissue Doppler recordings for comparison with tissue velocities, colour M-mode and strain rate (SR).
Results:
Pre-ejection positive velocity spikes were simultaneous in both walls, starting ca. 24.8 ± 10.1 ms after start QRS, duration 51.5 ± 10.8 ms, ending 10.2 ± 11.5 ms after mitral valve closure (MVC) (p < 0.001). There were corresponding colour tracings and negative strain rate. Protodiastolic lengthening was predominant in the septum. Negative velocity spikes had a duration of 35.5 ± 10.7 ms, ending 9.5 ± 14.7 ms after aortic valve closure (AVC, p < 0.001) in septum. During isovolumic relaxation, strain rate showed apical lengthening (Peak SR-0.72 ± 0.50 s-1 ) and basal shortening (Peak SR 0.44 ± 0.63 s-1 ).
Conclusion:
Electromechanical activation of the LV is simultaneous in septum and lateral wall, occurs before MVC, is terminated by MVC itself and is thus not isovolumic. Protodiastole is a short event of lengthening, predominantly in the septum. It may be the mechanism for valve closure and ends by AVC itself. Isovolumic relaxation occurs after this velocity spike, and is characterized by elongation of the apex, shortening of the base, thus showing a volume shift from base towards apex.

Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:20
Mitral Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...