Related Experiment Video
Updated: Oct 31, 2025


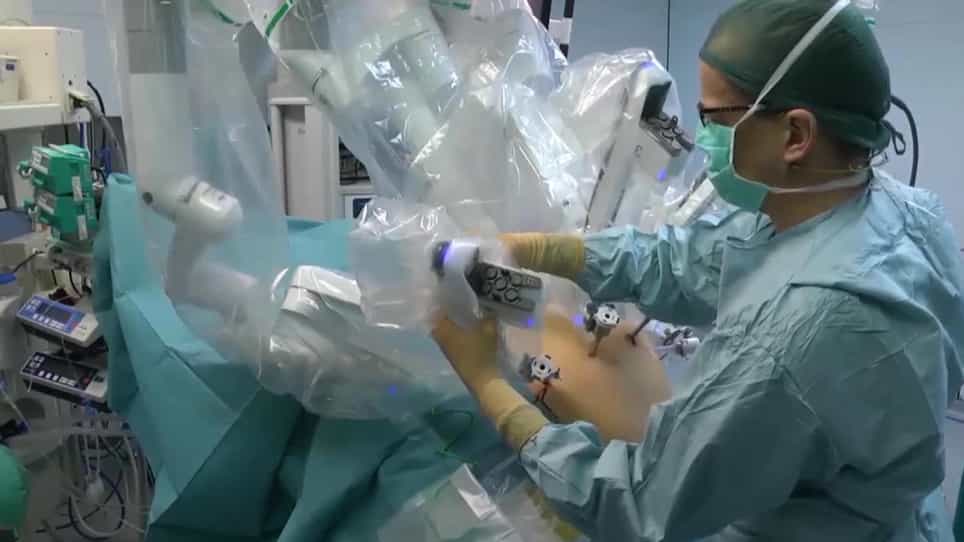
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Use of Total Neoadjuvant Therapy for Locally Advanced Rectal Cancer: Initial Results From the Pembrolizumab Arm of a
Osama E Rahma1,2, Greg Yothers1,3, Theodore S Hong1,4
1NRG Oncology, Philadelphia, Pennsylvania.

Importance:
Total neoadjuvant therapy (TNT) is often used to downstage locally advanced rectal cancer (LARC) and decrease locoregional relapse; however, more than one-third of patients develop recurrent metastatic disease. As such, novel combinations are needed.
Objective:
To assess whether the addition of pembrolizumab during and after neoadjuvant chemoradiotherapy can lead to an improvement in the neoadjuvant rectal (NAR) score compared with treatment with FOLFOX (5-fluorouracil, leucovorin, and oxaliplatin) and chemoradiotherapy alone.
Design, Setting, And Participants:
In this open-label, phase 2, randomized clinical trial (NRG-GI002), patients in academic and private practice settings were enrolled. Patients with stage II/III LARC with distal location (cT3-4 ≤ 5 cm from anal verge, any N), with bulky disease (any cT4 or tumor within 3 mm of mesorectal fascia), at high risk for metastatic disease (cN2), and/or who were not candidates for sphincter-sparing surgery (SSS) were stratified based on clinical tumor and nodal stages. Trial accrual opened on August 1, 2018, and ended on May 31, 2019. This intent-to-treat analysis is based on data as of August 2020.
Interventions:
Patients were randomized (1:1) to neoadjuvant FOLFOX for 4 months and then underwent chemoradiotherapy (capecitabine with 50.4 Gy) with or without intravenous pembrolizumab administered at a dosage of 200 mg every 3 weeks for up to 6 doses before surgery.
Main Outcomes And Measures:
The primary end point was the NAR score. Secondary end points included pathologic complete response (pCR) rate, SSS, disease-free survival, and overall survival. This report focuses on end points available after definitive surgery (NAR score, pCR, SSS, clinical complete response rate, margin involvement, and safety).
Results:
A total of 185 patients (126 [68.1%] male; mean [SD] age, 55.7 [11.1] years) were randomized to the control arm (CA) (n = 95) or the pembrolizumab arm (PA) (n = 90). Of these patients, 137 were evaluable for NAR score (68 CA patients and 69 PA patients). The mean (SD) NAR score was 11.53 (12.43) for the PA patients (95% CI, 8.54-14.51) vs 14.08 (13.82) for the CA patients (95% CI, 10.74-17.43) (P = .26). The pCR rate was 31.9% in the PA vs 29.4% in the CA (P = .75). The clinical complete response rate was 13.9% in the PA vs 13.6% in the CA (P = .95). The percentage of patients who underwent SSS was 59.4% in the PA vs 71.0% in the CA (P = .15). Grade 3 to 4 adverse events were slightly increased in the PA (48.2%) vs the CA (37.3%) during chemoradiotherapy. Two deaths occurred during FOLFOX: sepsis (CA) and pneumonia (PA). No differences in radiotherapy fractions, FOLFOX, or capecitabine doses were found.
Conclusions And Relevance:
Pembrolizumab added to chemoradiotherapy as part of total neoadjuvant therapy was suggested to be safe; however, the NAR score difference does not support further study.
Trial Registration:
ClinicalTrials.gov Identifier: NCT02921256.
More Related Videos
 09:11
Y-90 Radioembolization and PD-1 Inhibitor as Neoadjuvant Treatment in Hepatocellular Carcinoma
Published on: May 24, 2024
 12:34
Robot-Assisted Radical Antegrade Modular Pancreatosplenectomy Including Resection and Reconstruction of the Spleno-Mesenteric Junction
Published on: January 3, 2020
