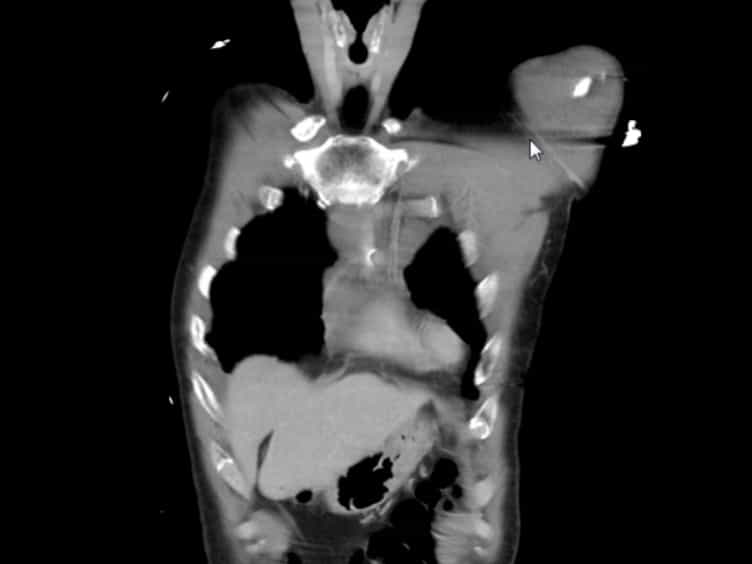

Surgical stabilization of traumatic rib fractures is associated with reduced readmissions and increased survival
Erik A Green1, Chrissy Guidry1, Charles Harris2
1Department of Surgery, Tulane University School of Medicine, New Orleans, LA.

Background:
Surgical stabilization for rib fractures (SSRF) in trauma patients remains controversial, with guidelines currently suggesting the procedure for only select patient groups. How surgical stabilization for rib fractures affect hospital readmission in patients with traumatic rib fractures is unknown. We hypothesized that surgical stabilization for rib fractures would not decrease the risk of readmission.
Methods:
The National Readmission Database was examined for adults with any rib fractures from 2010 to 2017. Readmission up to 90 days was examined. Patients receiving surgical stabilization for rib fractures were compared with those receiving nonoperative treatment.
Results:
In total, 864,485 patients met criteria, with 13,701 (1.6%) receiving SSRF. For patients receiving SSRF, 338 (1.5%) were readmitted. Readmitted patients had higher Charlson Comorbidity Index and were more likely to have flail chest. On multivariate propensity score-matched analysis, SSRF (Hazard Ratio [HR]: 0.55, 95% confidence interval [CI] 0.33-0.92, P = .022) was associated with reduced readmission. Addition of surgical stabilization for rib fractures to video-assisted thoracoscopic surgery (VATS) (Odds Ratio [OR]: 0.95, 95% CI 0.52-1.73, P = .86) or thoracotomy (OR: 1.97, 95% CI 0.83-4.70, P = .13) was not associated with increased readmission. On further propensity matched analysis, VATS + SSRF when compared with SSRF alone (HR: 0.75, 95% CI 0.18-3.20, P = .696), and VATS + SSRF when compared with VATS alone (HR: 0.49, 95% CI 0.11-2.22, P = .355) was also not associated with increased readmission. SSRF on primary admission was associated with increased in-hospital survival (HR: 0.27, 95% CI 0.22-0.32, P < .001). For patients with retained hemothorax who underwent VATS, addition of SSRF did not improve survival (HR = 0.92, 95% CI 0.58-1.46, P = .72). However, for patients requiring thoracotomy for retained hemothorax, concomitant SSRF was associated with improved survival (HR = 0.14, 95% CI 0.06-0.32, P < .001).
Conclusion:
Surgical stabilization for rib fractures is associated with reduced readmission risk while also being associated with improved survival. Patients who had a thoracotomy for retained hemothorax appear to especially benefit from concomitant surgical stabilization for rib fractures.
More Related Videos

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:27
Pneumothorax-II
Clinical Manifestations: