Related Experiment Video
Updated: Oct 30, 2025
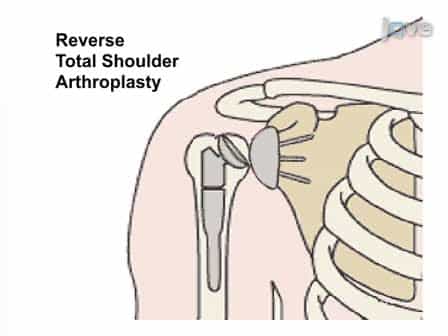
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Long-term results after posterior open glenoid wedge osteotomy for posterior shoulder instability associated with
Manuel Waltenspül1, Thomas Häller1, Lukas Ernstbrunner1
1Department of Orthopedics, Balgrist University Hospital, University of Zürich, Zürich, Switzerland.

Background:
Treatment of posterior shoulder instability (PSI) associated with excessive glenoid retroversion is a rare, challenging problem in shoulder surgery. One proposed technique is posterior open wedge glenoid osteotomy to correct excessive glenoid retroversion as described by Scott. However, this operation is rarely performed, and limited long-term outcomes using this approach are available. The goal of this study was to analyze the long-term outcomes of posterior open wedge glenoid osteotomy for PSI associated with excessive glenoid retroversion.
Methods:
Six consecutive patients (7 shoulders) with a mean age of 24 years (range 19-34) were treated with posterior open wedge glenoid osteotomy for PSI associated with a glenoid retroversion greater than 15° and followed up clinically and radiographically at a mean age of 15 years (range 10-19).
Results:
Recurrent, symptomatic PSI was observed in 6 of 7 shoulders (86%). One necessitated revision with a posterior (iliac crest) bone block procedure and was rated as a failure and excluded from functional analysis. One patient rated his result as excellent, 3 as good, 1 as fair, and 1 as unsatisfactory. Mean relative Constant Score (CS%) was unchanged from preoperation to final follow-up (CS% = 72%) and pain did not significantly decrease (Constant Score = 7-10 points; P = .969). The mean Subjective Shoulder Value (SSV) improved postoperatively, but with 6 patients the improvement did not reach statistical significance (SSV = 42%-67%, P = .053) and the total Western Ontario Shoulder Instability Index averaged 30% at the final follow-up. Mean glenoid retroversion of all 7 shoulders was corrected from 20° (range 16°-26°) to 3° (range -3° to +8°) (P = .018). In the 5 shoulders with preoperative static posterior subluxation of the humeral head, the humeral head was not recentered. All 7 shoulders showed progression of glenoid arthritic changes.
Conclusions:
Posterior open wedge glenoid osteotomy for PSI associated with excessive glenoid retroversion neither reliably restored shoulder stability nor recentered the joint or prevent progression of osteoarthritis. Alternative treatments for PSI associated with excessive glenoid retroversion have to be developed and evaluated.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 07:22
Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025