Related Experiment Video
Updated: Oct 29, 2025
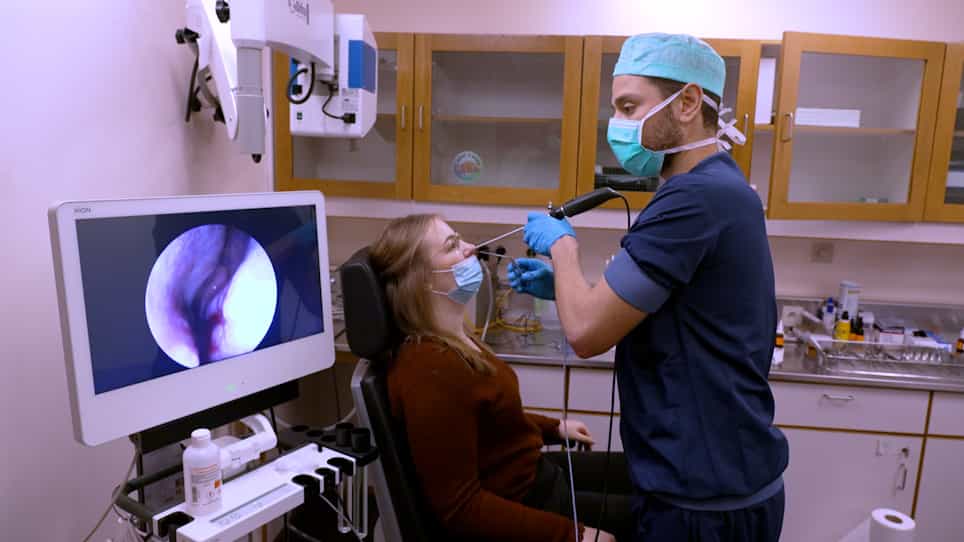

Nasal Brushing Sampling and Processing Using Digital High Speed Ciliary Videomicroscopy – Adaptation for the COVID-19 Pandemic
Published on: November 7, 2020
Safety practices for in-office laryngology procedures during clinical reintroduction amidst COVID-19
Haley Calcagno1, Benjamin P Anthony1, Stacey L Halum1
1The Indiana University School of Medicine and the Department of Otolaryngology-Head and Neck Surgery, Indiana University Indianapolis Indiana USA.

Objective:
Describe safety practices for performing in-office laryngology procedures during clinical re-introduction amidst the coronavirus disease 2019 (COVID-19) pandemic.
Methods:
An anonymous survey in Qualtrics was created to evaluate demographics, preprocedure testing, practice settings, anesthesia, and personal protective equipment (PPE) use for five procedure categories (non-mucosal-traversing injections, mucosal-traversing injections, endoscopy without suction, endoscopy with suction/mucosal intervention via working channel, and laser via working channel). The survey was emailed to the Fall Voice Community on Doc Matter and to members of the American Broncho-Esophagological Association (ABEA) from May to June 2020.
Results:
Eighty-two respondents were analyzed (response rate: 10%). Respondents represented diverse locations, including international. Most reported academic (71%) or private practices (16%), laryngology fellowship training (76%), and a significant practice devotion to laryngology and broncho-esophagology. During the early re-introduction, most continued to perform all procedure categories. The office was preferred to the OR setting for most, though 36% preferred the OR for laser procedures. There was a preference for preprocedural SARS-Cov2 testing for procedures involving a working channel (>67%), and these procedures had the highest proportion of respondents discontinuing the procedure due to COVID-19. Various types of topical anesthesia were reported, including nebulizer treatments. The most common forms of personal protective equipment utilized were gloves (>95%) and N95 masks (>67%). Powered-air purifying respirators and general surgical masks were used infrequently.
Conclusions:
During the early re-introduction, respondents reported generally continuing to perform office laryngology procedures, while greater mucosal manipulation affected decisions to stop procedures due to COVID-19, perform preprocedural SARS-Cov2 testing, and alter topical anesthesia. Gloves and N95 masks were the predominate PPE.
Level Of Evidence:
N/A.


Related Concept Videos
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...
 01:23
Tracheostomy Suctioning II: Procedure
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes: