Rationale of a lower dexamethasone dose in prenatal congenital adrenal hyperplasia therapy based on pharmacokinetic modelling
Related Experiment Video
Updated: Oct 29, 2025

A Hyperandrogenic Mouse Model to Study Polycystic Ovary Syndrome
Published on: October 2, 2018
Viktoria Stachanow1,2, Uta Neumann3, Oliver Blankenstein3
1Department of Clinical Pharmacy and Biochemistry, Institute of Pharmacy, Freie Universitaet Berlin, Berlin, Germany.

Context:
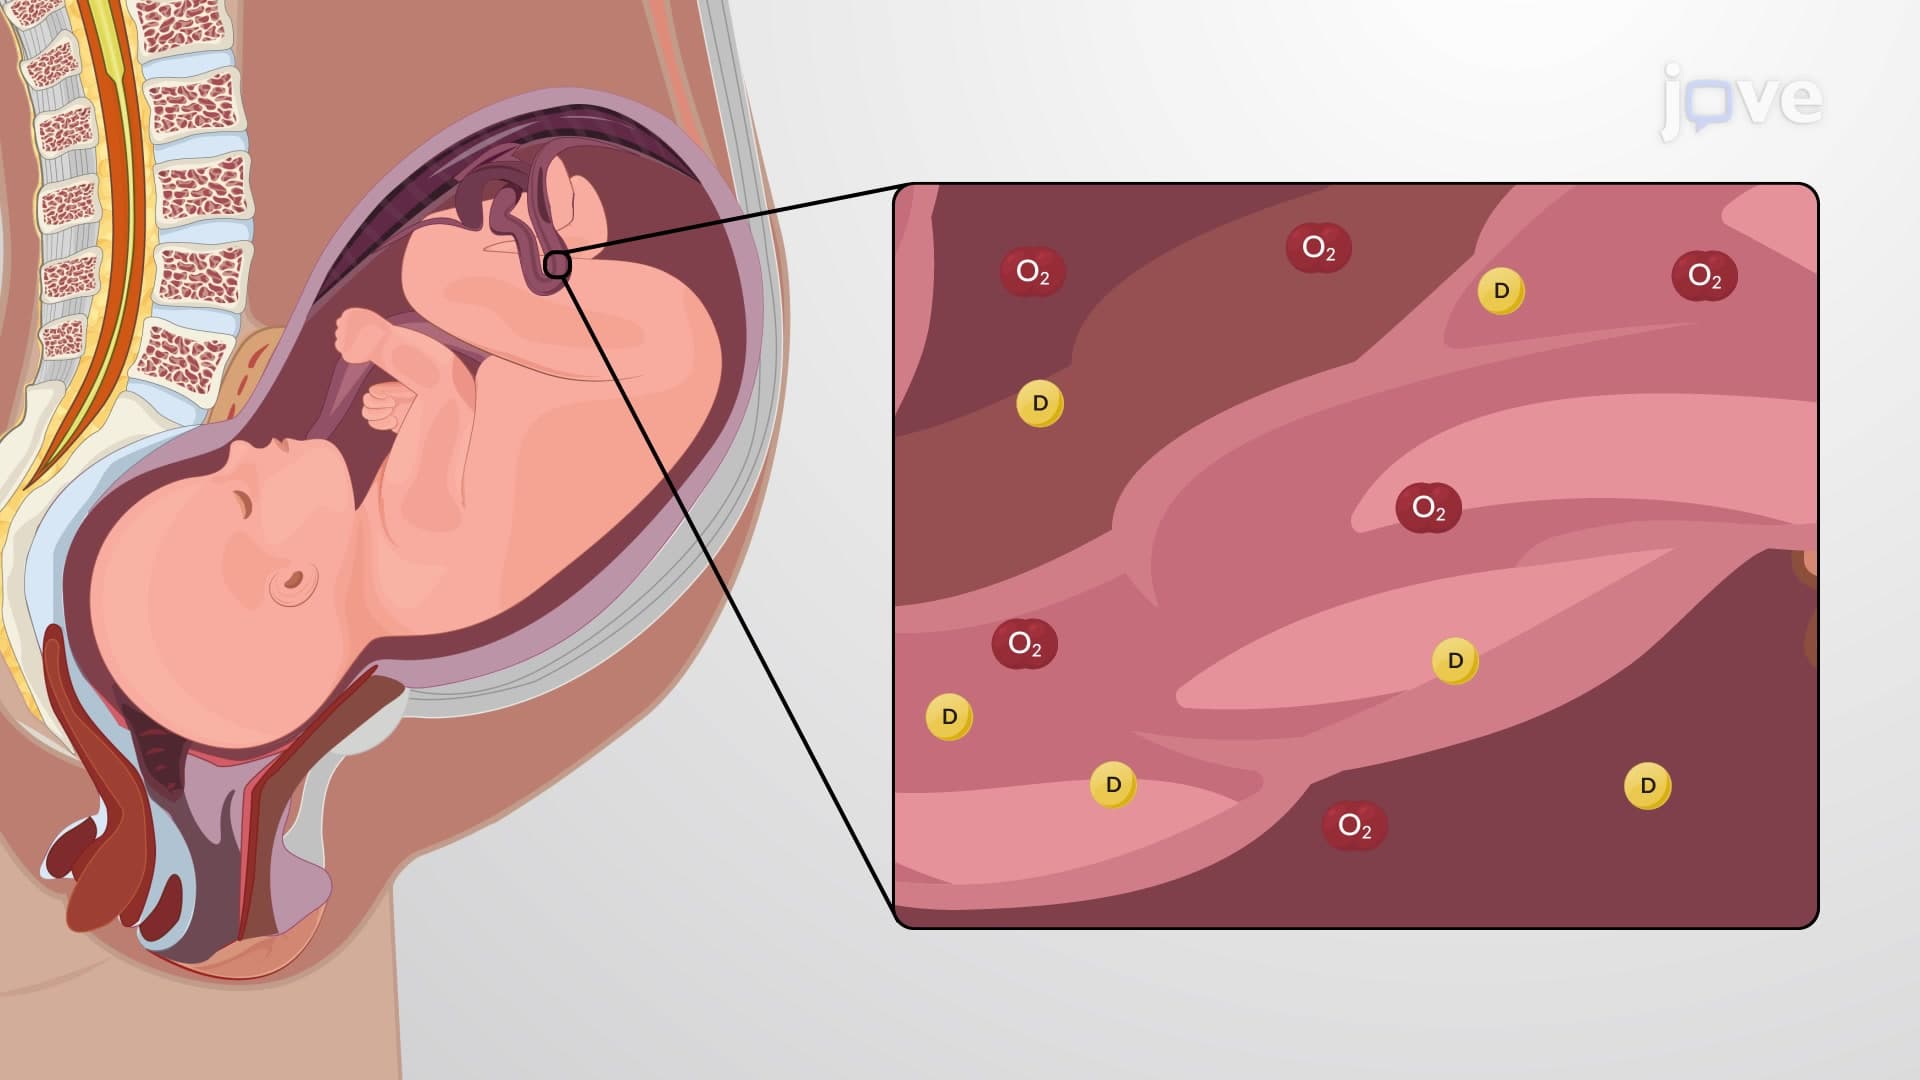
Prenatal dexamethasone therapy is used in female foetuses with congenital adrenal hyperplasia to suppress androgen excess and prevent virilisation of the external genitalia. The traditional dexamethasone dose of 20 µg/kg/day has been used since decades without examination in clinical trials and is thus still considered experimental.
Objective:
As the traditional dexamethasone dose potentially causes adverse effects in treated mothers and foetuses, we aimed to provide a rationale of a reduced dexamethasone dose in prenatal congenital adrenal hyperplasia therapy based on a pharmacokinetics-based modelling and simulation framework.
Methods:
Based on a published dexamethasone dataset, a nonlinear mixed-effects model was developed describing maternal dexamethasone pharmacokinetics. In stochastic simulations (n = 1000), a typical pregnant population (n = 124) was split into two dosing arms receiving either the traditional 20 µg/kg/day dexamethasone dose or reduced doses between 5 and 10 µg/kg/day. Target maternal dexamethasone concentrations, identified from the literature, served as a threshold to be exceeded by 90% of mothers at a steady state to ensure foetal hypothalamic-pituitary-adrenal axis suppression.
Results:
A two-compartment dexamethasone pharmacokinetic model was developed and subsequently evaluated to be fit for purpose. The simulations, including a sensitivity analysis regarding the assumed foetal:maternal dexamethasone concentration ratio, resulted in 7.5 µg/kg/day to be the minimum effective dose and thus our suggested dose.
Conclusions:
We conclude that the traditional dexamethasone dose is three-fold higher than needed, possibly causing harm in treated foetuses and mothers. The clinical relevance and appropriateness of our recommended dose should be tested in a prospective clinical trial.


Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:21
Factors Affecting Drug Response: Overview
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism