

Hypokalemic Periodic Paralysis Precipitated by Thyrotoxicosis and Renal Tubular Acidosis
Ian Jackson1, Yazan Addasi1, Moeed Ahmed1
1Department of Medicine, Creighton University School of Medicine, Omaha, NE, USA.

Background:
Hypokalemic periodic paralysis is a rare neuromuscular disorder characterized by transient episodes of flaccid paralysis due to a defect in muscle ion channels. Most cases are hereditary, but it can be acquired. We present a case of acquired hypokalemic periodic paralysis associated with hyperthyroidism and renal tubular acidosis. Clinical Case. A 38-year-old female with a history of Graves' disease presented to the emergency department with generalized weakness and associated nausea, vomiting, and weight loss. Examination was significant for diffuse weakness in all extremities. Labs showed hypokalemia, hyperthyroidism, and nonanion gap metabolic acidosis with a positive urine anion gap. She was treated for hypokalemic periodic paralysis and renal tubular acidosis. Potassium replacement, propranolol, methimazole, and sodium bicarbonate were initiated. Her potassium gradually corrected with resolution of her symptoms. Further investigation revealed a history of dry eyes, dry mouth, and recurrent dental carries. She had positive ANA, SS-A, and SS-B antibodies. She was diagnosed with Sjögren's syndrome, which may have been associated with her Graves' disease and thus contributed to both her RTA and hyperthyroidism.
Conclusion:
Early recognition and treatment of thyrotoxic periodic paralysis are important to prevent cardiac complications. Management includes potassium replacement with careful monitoring to prevent rebound hyperkalemia. The definitive treatment is to achieve euthyroid status.
More Related Videos


Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:29
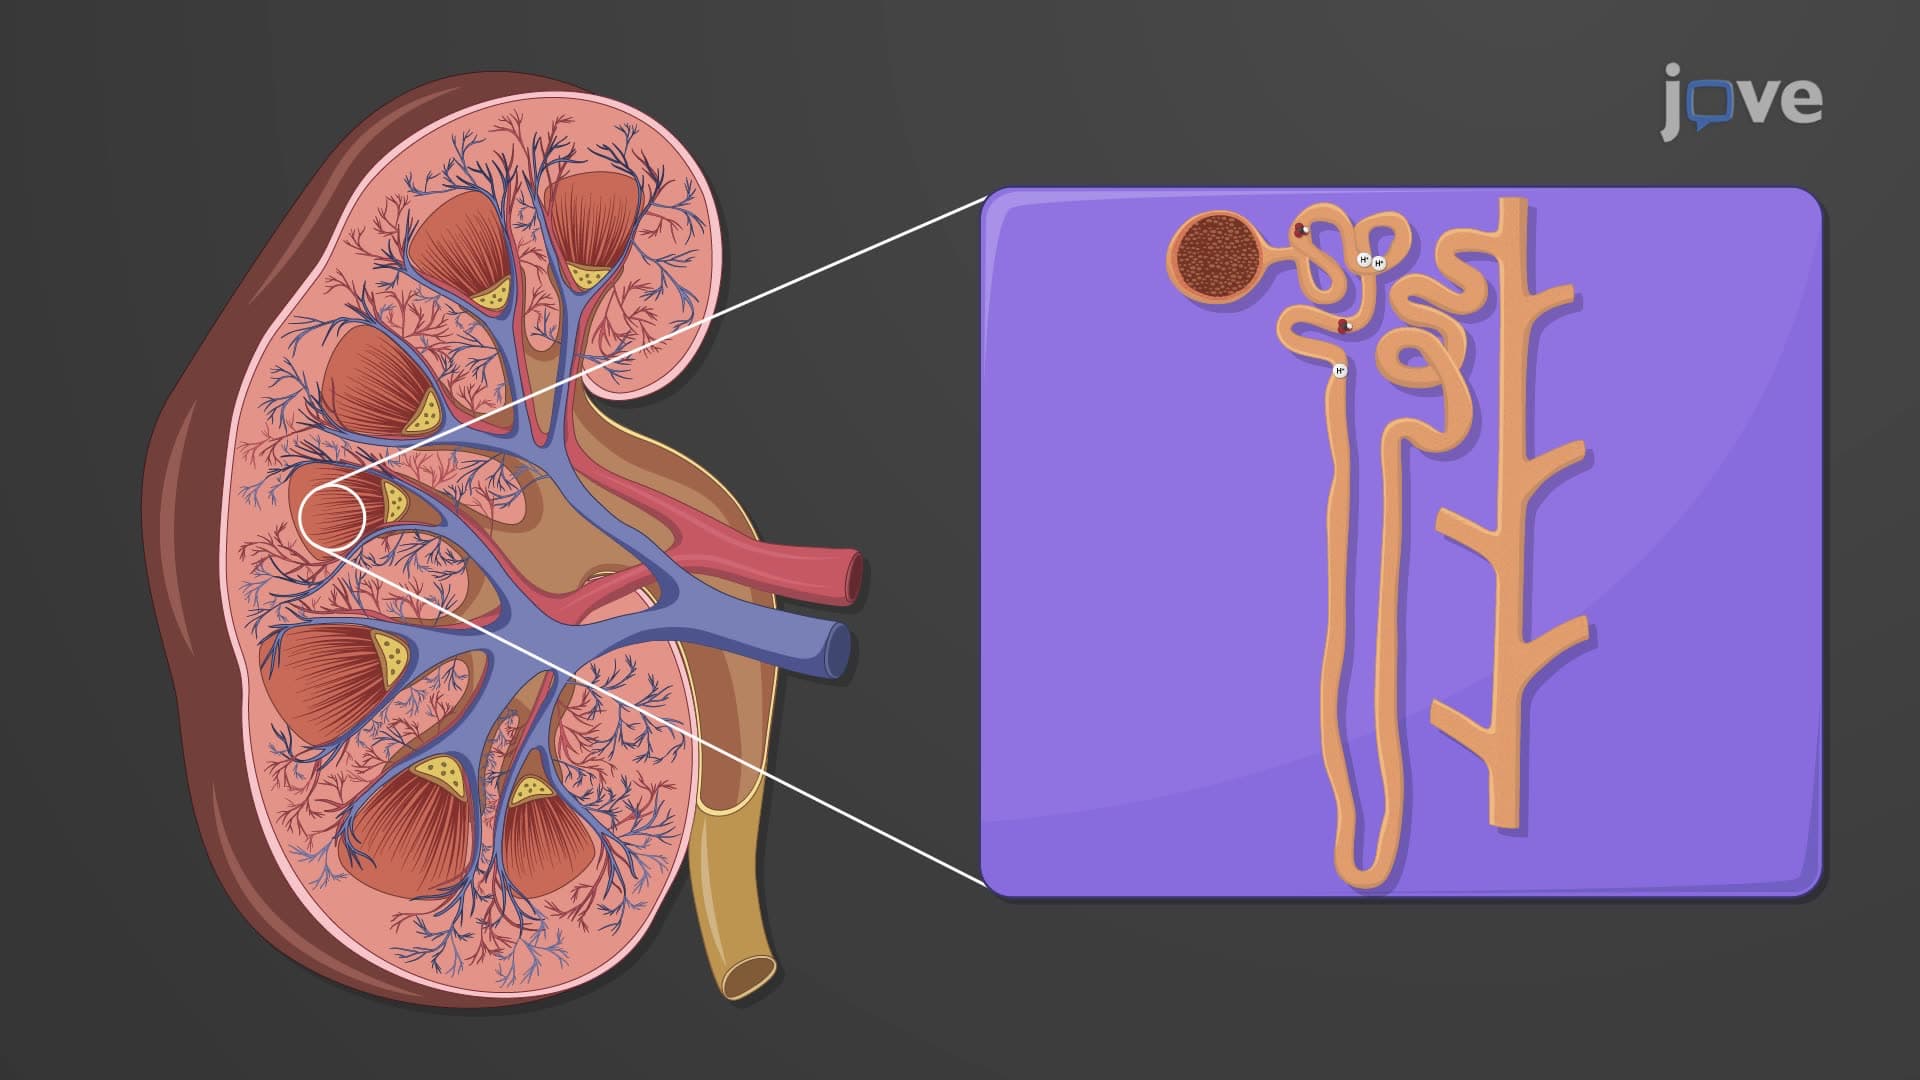
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...