Related Experiment Video
Updated: Oct 29, 2025
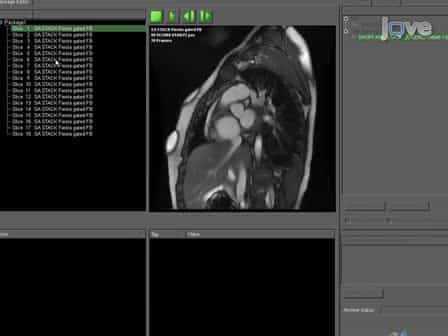
Magnetic Resonance Derived Myocardial Strain Assessment Using Feature Tracking
Published on: February 12, 2011
Multi-parametric assessment of left ventricular hypertrophy using late gadolinium enhancement, T1 mapping and
Sorin Giusca1, Henning Steen2, Moritz Montenbruck2
1Departments of Cardiology, Vascular Medicine and Pneumology, GRN Hospital Weinheim, Roentgenstrasse 1, 69469, Weinheim, Germany.

Insights
Single heartbeat fast-strain encoded (SENC) cardiovascular magnetic resonance (CMR) myocardial strain effectively differentiates athletes from hypertrophic cardiomyopathy (HCM) and hypertensive heart disease (HHD). Combining strain with late gadolinium enhancement (LGE) aids in distinguishing HHD from HCM and HCM from cardiac amyloidosis.
Area of Science:
- Cardiology
- Medical Imaging
- Biophysics
Background:
- Left ventricular hypertrophy (LVH) presents in various forms, including hypertensive heart disease (HHD), hypertrophic cardiomyopathy (HCM), and cardiac amyloidosis, necessitating accurate differentiation.
- Distinguishing between these conditions and healthy states or athletic adaptations is crucial for appropriate patient management and treatment strategies.
Purpose of the Study:
- To assess the efficacy of single heartbeat fast-strain encoded (SENC) cardiovascular magnetic resonance (CMR) derived myocardial strain in differentiating various forms of left ventricular hypertrophy (LVH).
- To evaluate the combined diagnostic utility of SENC strain and late gadolinium enhancement (LGE) for classifying LVH subtypes.
Main Methods:
- Analysis of 314 patients, including those with HHD, HCM, amyloidosis, competitive athletes, and healthy controls.
- Assessment of left ventricular ejection fraction (LVEF), LV mass index, interventricular septal (IVS) thickness, T1 mapping, and atypical LGE.
- Quantification of the percentage of LV myocardial segments with strain ≤ -17% (%normal myocardium).
Main Results:
- Patients with amyloidosis and HCM showed significantly higher IVS thickness compared to other groups.
- Amyloidosis patients exhibited the highest LV mass index and lower LVEF than controls.
- In mild to moderate hypertrophy, %normal myocardium accurately differentiated athletes from HCM (AUC=1.0) and athletes from HHD (AUC=0.85).
- The combination of %normal myocardial strain and atypical LGE demonstrated high accuracy in differentiating HHD vs. HCM (AUC=0.92) and HCM vs. amyloidosis (AUC=0.83).
Conclusions:
- Fast-SENC derived myocardial strain is a valuable tool for differentiating athletes from HCM and HHD.
- Integrating SENC strain with LGE data enhances diagnostic accuracy for distinguishing between HHD, HCM, and cardiac amyloidosis.
Aim:
To evaluate the ability of single heartbeat fast-strain encoded (SENC) cardiovascular magnetic resonance (CMR) derived myocardial strain to discriminate between different forms of left ventricular (LV) hypertrophy (LVH).
Methods:
314 patients (228 with hypertensive heart disease (HHD), 45 with hypertrophic cardiomyopathy (HCM), 41 with amyloidosis, 22 competitive athletes, and 33 healthy controls) were systematically analysed. LV ejection fraction (LVEF), LV mass index and interventricular septal (IVS) thickness, T1 mapping and atypical late gadolinium enhancement (LGE) were assessed. In addition, the percentage of LV myocardial segments with strain ≤ - 17% (%normal myocardium) was determined.
Results:
Patients with amyloidosis and HCM exhibited the highest IVS thickness (17.4 ± 3.3 mm and 17.4 ± 6 mm, respectively, p < 0.05 vs. all other groups), whereas patients with amyloidosis showed the highest LV mass index (95.1 ± 20.1 g/m2, p < 0.05 vs all others) and lower LVEF compared to controls (50.5 ± 9.8% vs 59.2 ± 5.5%, p < 0.05). Analysing subjects with mild to moderate hypertrophy (IVS 11-15 mm), %normal myocardium exhibited excellent and high precision, respectively for the differentiation between athletes vs. HCM (sensitivity and specificity = 100%, Area under the curve; AUC%normalmyocardium = 1.0, 95%CI = 0.85-1.0) and athletes vs. HHD (sensitivity = 83%, specificity = 75%, AUC%normalmyocardium = 0.85, 95%CI = 0.78-0.90). Combining %normal myocardial strain with atypical LGE provided high accuracy also for the differentiation of HHD vs. HCM (sensitivity = 82%, specificity = 100%, AUCcombination = 0.92, 95%CI = 0.88-0.95) and HCM vs. amyloidosis (sensitivity = 83%, specificity = 100%, AUCcombination = 0.83, 95%CI = 0.60-0.96).
Conclusion:
Fast-SENC derived myocardial strain is a valuable tool for differentiating between athletes vs. HCM and athletes vs. HHD. Combining strain and LGE data is useful for differentiating between HHD vs. HCM and HCM vs. cardiac amyloidosis.
More Related Videos
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:21
Imaging Studies for Cardiovascular System IV: CMRI