Related Experiment Video
Updated: Oct 29, 2025


Author Spotlight: Advancements in Retroperitoneal Approach for Necrotizing Pancreatitis
Published on: March 15, 2024
Radiological and surgical management of bleeding pancreatic pseudocyst in a pediatric patient

Insights
Pediatric pancreatic trauma can lead to giant pseudocysts. This case highlights the successful radiological and surgical management of a large traumatic pancreatic pseudocyst with intracystic bleeding.
Area of Science:
- Pediatric surgery
- Trauma surgery
- Gastroenterology
Background:
- The pancreas is the fourth most frequently injured solid organ in pediatric abdominal trauma.
- Traumatic pancreatic injuries require careful management due to potential complications.
Observation:
- A 13-year-old male developed a giant pancreatic pseudocyst (170x86x180 mm) following grade IV pancreatic injury.
- The patient experienced intracystic bleeding, abdominal compartment syndrome, biliary leak, and chemical peritonitis.
Findings:
- Radiological embolization of the gastroduodenal artery successfully managed intracystic bleeding.
- Laparotomy and drainage were necessary for abdominal compartment syndrome, biliary leak, and peritonitis.
- Pancreatitis and duct fistula showed slow but favorable recovery.
Implications:
- Giant pancreatic pseudocysts (>200 mm) may necessitate surgical intervention.
- Intracystic bleeding is a rare but life-threatening complication of pancreatic trauma.
- Selective angiography is a valuable tool for improving prognosis in such cases.
Introduction:
The pancreas is the fourth most frequently involved solid organ in pediatric abdominal trauma. We present the case of a giant pancreatic pseudocyst secondary to trauma and how it was radiologically and surgically managed.
Clinical Case:
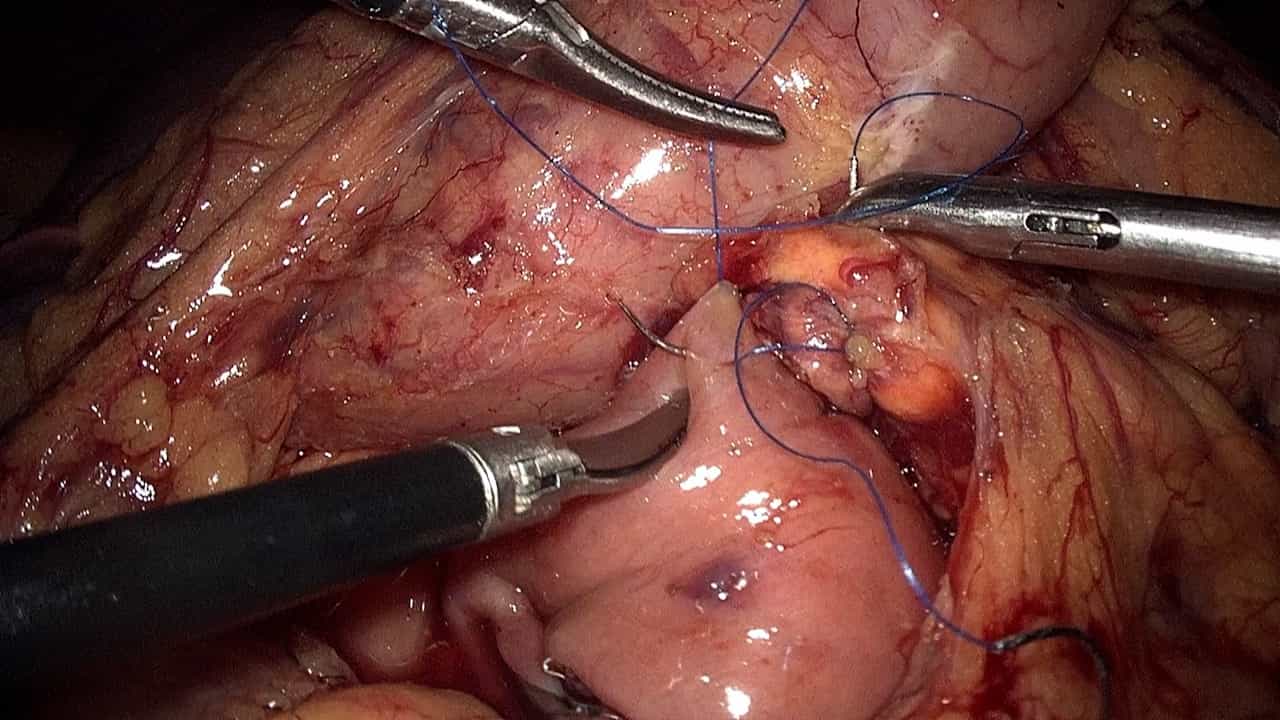
This is the case of a 13-year-old male patient admitted as a result of a grade IV pancreatic lesion, which turned into a 170x86x180 mm pancreatic pseudocyst. Intracystic bleeding required radiological embolization of the proximal gastroduodenal artery. Subsequent abdominal compartment syndrome, biliary leak, and chemical peritonitis required laparotomy and collection drainage. Pancreatitis and duct fistula had a slow but favorable progression.
Discussion:
The presence of duct damage is a failure predictor in the conservative treatment of pancreatic trauma. Surgical management could be indicated in recurrent, multiple, or giant (> 200 mm) pseudocysts. Intracystic bleeding is rare but potentially fatal. Selective angiogram could be a useful tool for improved prognosis.

Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management