Intraoperative diastolic function assessed by TEE does not agree with preoperative diastolic function grade in CABG patients
Related Experiment Video
Updated: Oct 29, 2025
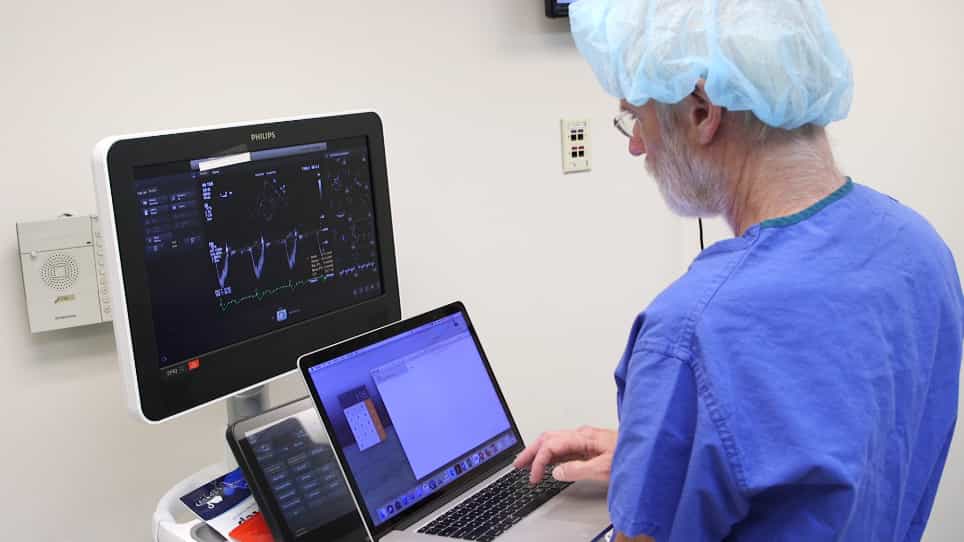
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Reed Harvey1, Vivek Chellappa1, Sean Mofidi1
1Department of Anesthesiology and Perioperative Medicine, David Geffen School of Medicine at UCLA, Los Angeles, California, USA.

Objective:
To compare the agreement of the 2016 ASE/EACVI guidelines for grading diastolic dysfunction (DD) with the most commonly used intraoperative transesophageal echocardiography (TEE)-based diastolic function grading algorithm in cardiac surgical patients, and to describe the contribution of the echocardiographic variables used in the algorithms to any observed differences.
Design:
Retrospective data analysis.
Setting:
University tertiary medical center.
Participants:
Hundred and one patients undergoing coronary artery bypass grafting (CABG) at a single institution from June 2017 to February 2019.
Interventions:
Preoperative transthoracic echocardiography (TTE) diastolic function grade determined by the 2016 American Society of Echocardiography (ASE)/European Association of Cardiovascular Imaging (EACVI) guidelines was compared to intraoperative diastolic function grade obtained by TEE.
Measurements And Main Results:
Incidence of DD on preoperative TTE was only 19.8%, while 62.3% of patients were graded as having DD on the intraoperative TEE exam. There was grade agreement between TTE and TEE in only 47/101 patients (46.5%). The McNemar test showed poor agreement between the two algorithms (OR for disagreement = 15.33, CI = 4.77-49.30; p < 0.0001). Despite the low incidence of DD on preoperative TTE, mean lateral e' values were significantly lower on TTE compared to TEE (7.7 cm/s vs 9.5 cm/s; p = < 0.0001).
Conclusions:
There is strong disagreement between TTE and TEE-based DD grading algorithms. Due to the different echocardiographic variables used in each and the unique clinical settings in which they are applied, they produce fundamentally different results.