Related Experiment Video
Updated: Oct 12, 2026

Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Pentoxifylline in end-stage renal disease
1Department of Medicine, University of Pittsburgh, PA 15261.

Abstract:
Little information is available about the clearance of pentoxifylline and its metabolites in renal failure. Consequently, when a dialysis patient required this drug, we started at a low dose and gradually increased the dosage while monitoring the patient for signs or symptoms of toxicity and following plasma concentrations of parent drug and its metabolites. Our patient appeared to develop evidence of drug toxicity after about six days on two-thirds of the usual recommended adult dose of the drug. The pentoxifylline half-life and apparent half-life of metabolite I were both substantially prolonged as compared with data from healthy volunteers. Both accumulated rapidly in plasma. Concentrations of metabolites IV and V were also very high.
Related Concept Videos
 01:15
Renal Drug Excretion: Overview
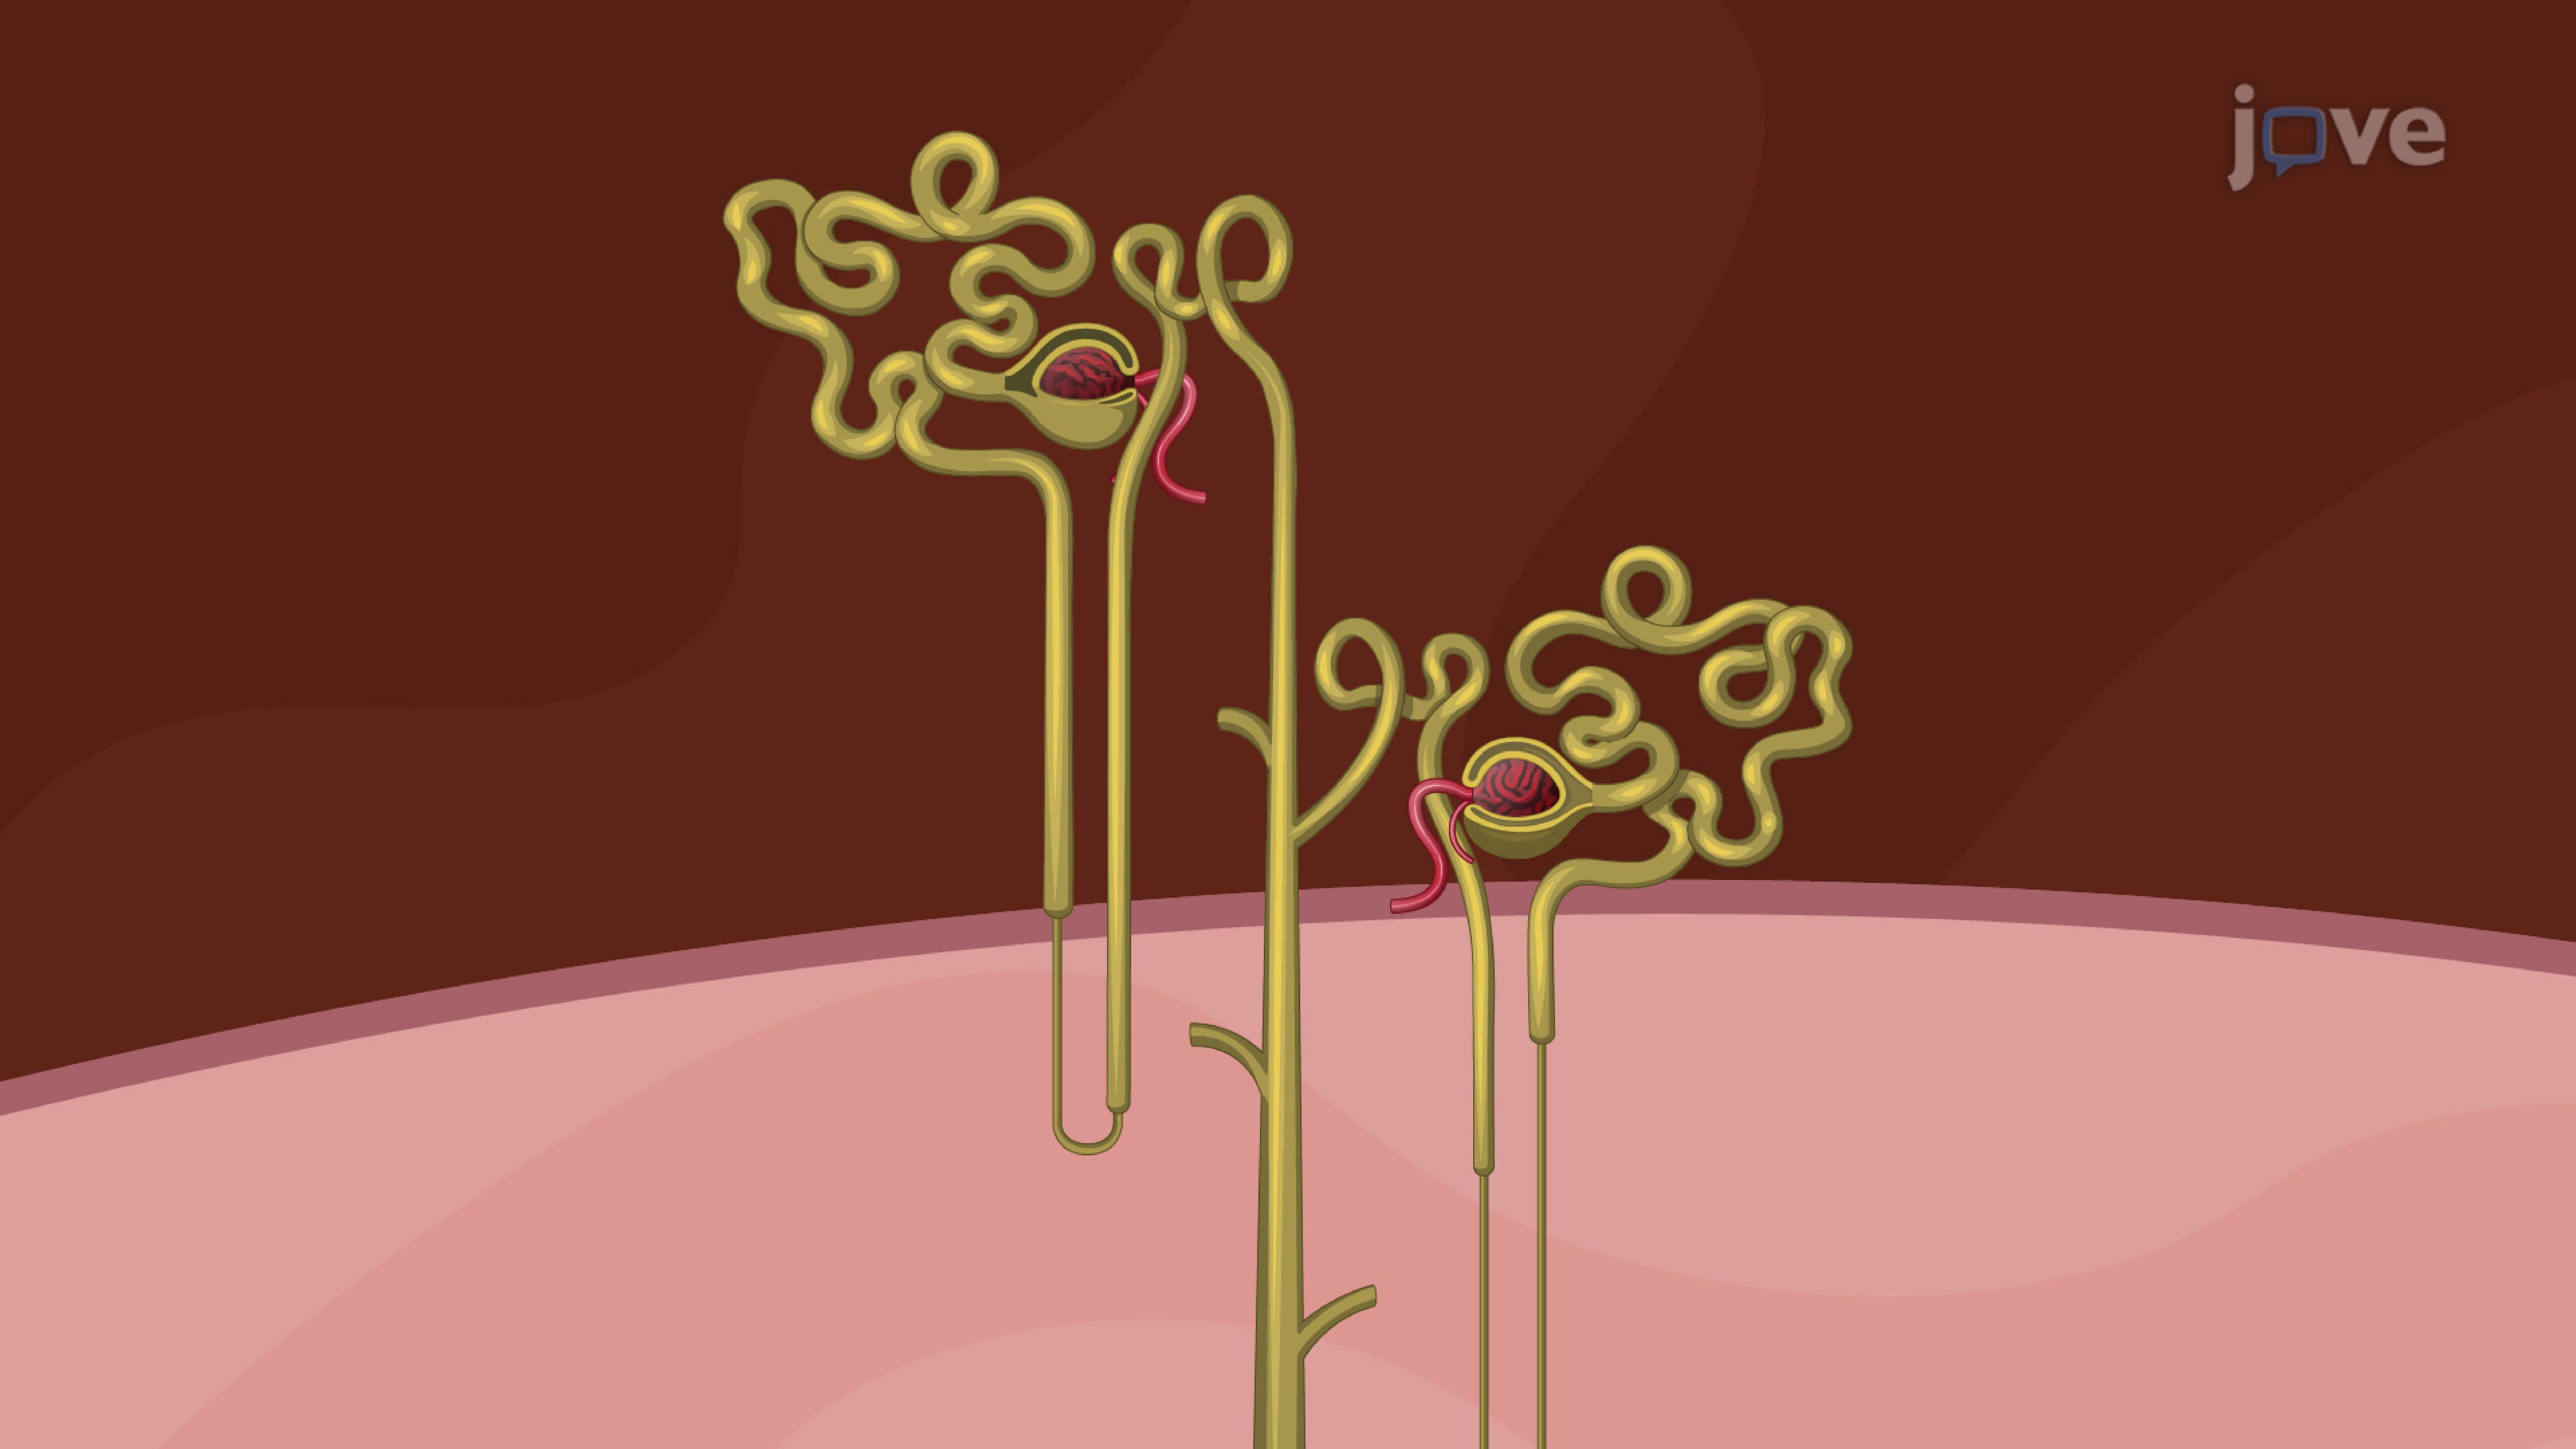
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:30
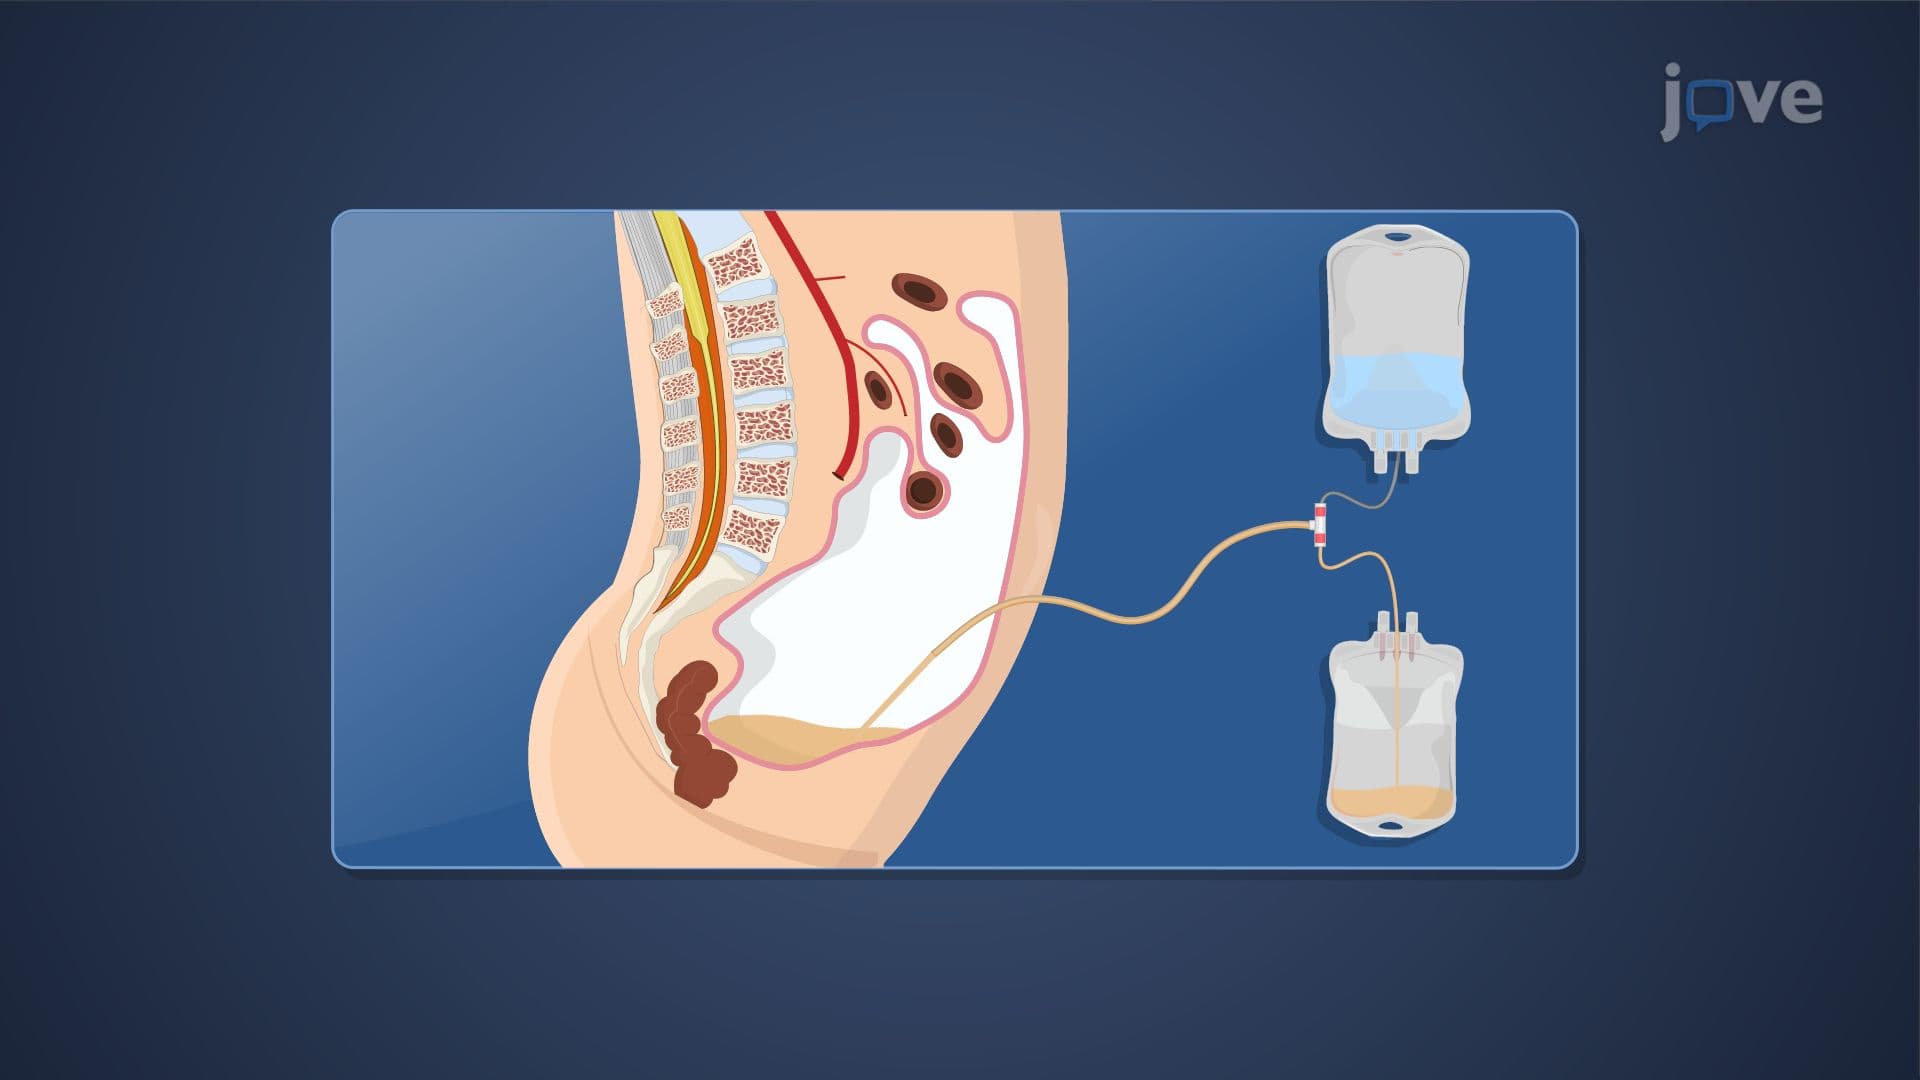
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis