Related Experiment Video
Updated: Oct 27, 2025
Application of End-to-end Anastomosis in Robotic Central Pancreatectomy
Published on: June 2, 2018
The clinicopathologic and operative characteristics of patients with small nonfunctioning pancreatic neuroendocrine
SuHyeon Ha1, Ki Byung Song1, Sarang Hong1
1Division of Hepatobiliary and Pancreatic Surgery, Department of Surgery, University of Ulsan College of Medicine and Asan Medical Center, Seoul, South Korea.

Background:
Incidentally detected, small nonfunctioning pancreatic neuroendocrine tumors (NF-PNETs) are increasingly diagnosed on imaging modalities. This retrospective investigation evaluated the clinicopathologic characteristics and perioperative and oncologic outcomes in patients with small NF-PNETs undergoing curative resection.
Methods:
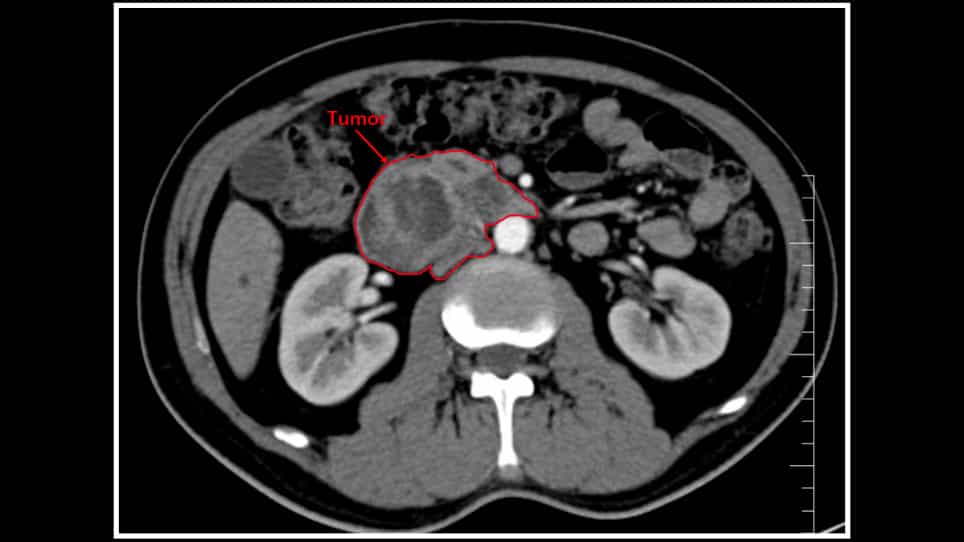
The medical records of 444 patients who underwent pancreatic resection for NF-PNETs at a single, large-volume institution between January 2000 and December 2018 were retrospectively reviewed. Patients were divided into those with small (≤2 cm) and large (>2 cm) tumors based on the largest tumor diameter on preoperative computed tomography (CT). Outcomes were also evaluated in subgroups of patients with small NF-PNET who did and did not undergo lymphadenectomy.
Results:
Of the 444 patients with NF-PNETs, 195 (43.9%) had small (≤2 cm) and 249 (56.1%) had large (>2 cm) NF-PNETs. The rate of parenchyma-preserving surgery (14.4% vs. 7.2%, p = 0.014) and the ratio of spleen preservation for left-sided pancreatectomy (65.6% vs. 38.3%, p < 0.001) were higher in the small NF-PNET group. Size on CT >2 cm (p < 0.001, hazard ratio [HR]: 5.836, 95% confidence interval [CI]: 2.474-13.769), presence of perineural invasion (p < 0.001, HR: 3.025, 95% CI: 1.640-5.577), World Health Organization (WHO) Grade 2 (p = 0.007, HR: 2.861, 95% CI: 1.325-6.176), and WHO Grade 3 (p < 0.001, HR: 11.537, 95% CI: 5.282-25.199) were independent predictors of disease-free survival (DFS). DFS did not differ significantly in patients with small NF-PNETs who did and did not undergo lymphadenectomy (p = 0.886).
Conclusions:
Assessment of long-term oncologic outcomes suggests that surgical resection may cure small NF-PNETs. Minimally invasive surgery and organ-preserving surgery are acceptable treatment options for select patients with small NF-PNETs. The effect on survival outcomes of lymph node dissection for small NF-PNETs remains unclear.
Insights
Small nonfunctioning pancreatic neuroendocrine tumors (NF-PNETs) can be cured by surgical resection. Organ-preserving techniques are suitable for select patients, but the role of lymph node dissection for small NF-PNETs requires further study.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Endocrinology
Background:
- Small nonfunctioning pancreatic neuroendocrine tumors (NF-PNETs) are increasingly detected incidentally.
- This study evaluates outcomes for patients with small NF-PNETs undergoing resection.
Purpose of the Study:
- To assess clinicopathologic features and outcomes of small NF-PNETs.
- To compare outcomes of lymphadenectomy versus no lymphadenectomy in small NF-PNETs.
Main Methods:
- Retrospective review of 444 patients who underwent pancreatic resection for NF-PNETs.
- Tumors classified as small (≤2 cm) or large (>2 cm) based on preoperative CT.
- Subgroup analysis of small NF-PNETs with and without lymphadenectomy.
Main Results:
- Small NF-PNETs had higher rates of parenchyma-preserving and spleen-preserving surgery.
- Tumor size >2 cm, perineural invasion, and WHO Grades 2/3 predicted poorer disease-free survival (DFS).
- No significant difference in DFS for small NF-PNETs with or without lymphadenectomy.
Conclusions:
- Surgical resection can potentially cure small NF-PNETs.
- Minimally invasive and organ-preserving surgeries are viable options for select small NF-PNET patients.
- The impact of lymph node dissection on survival for small NF-PNETs remains uncertain.