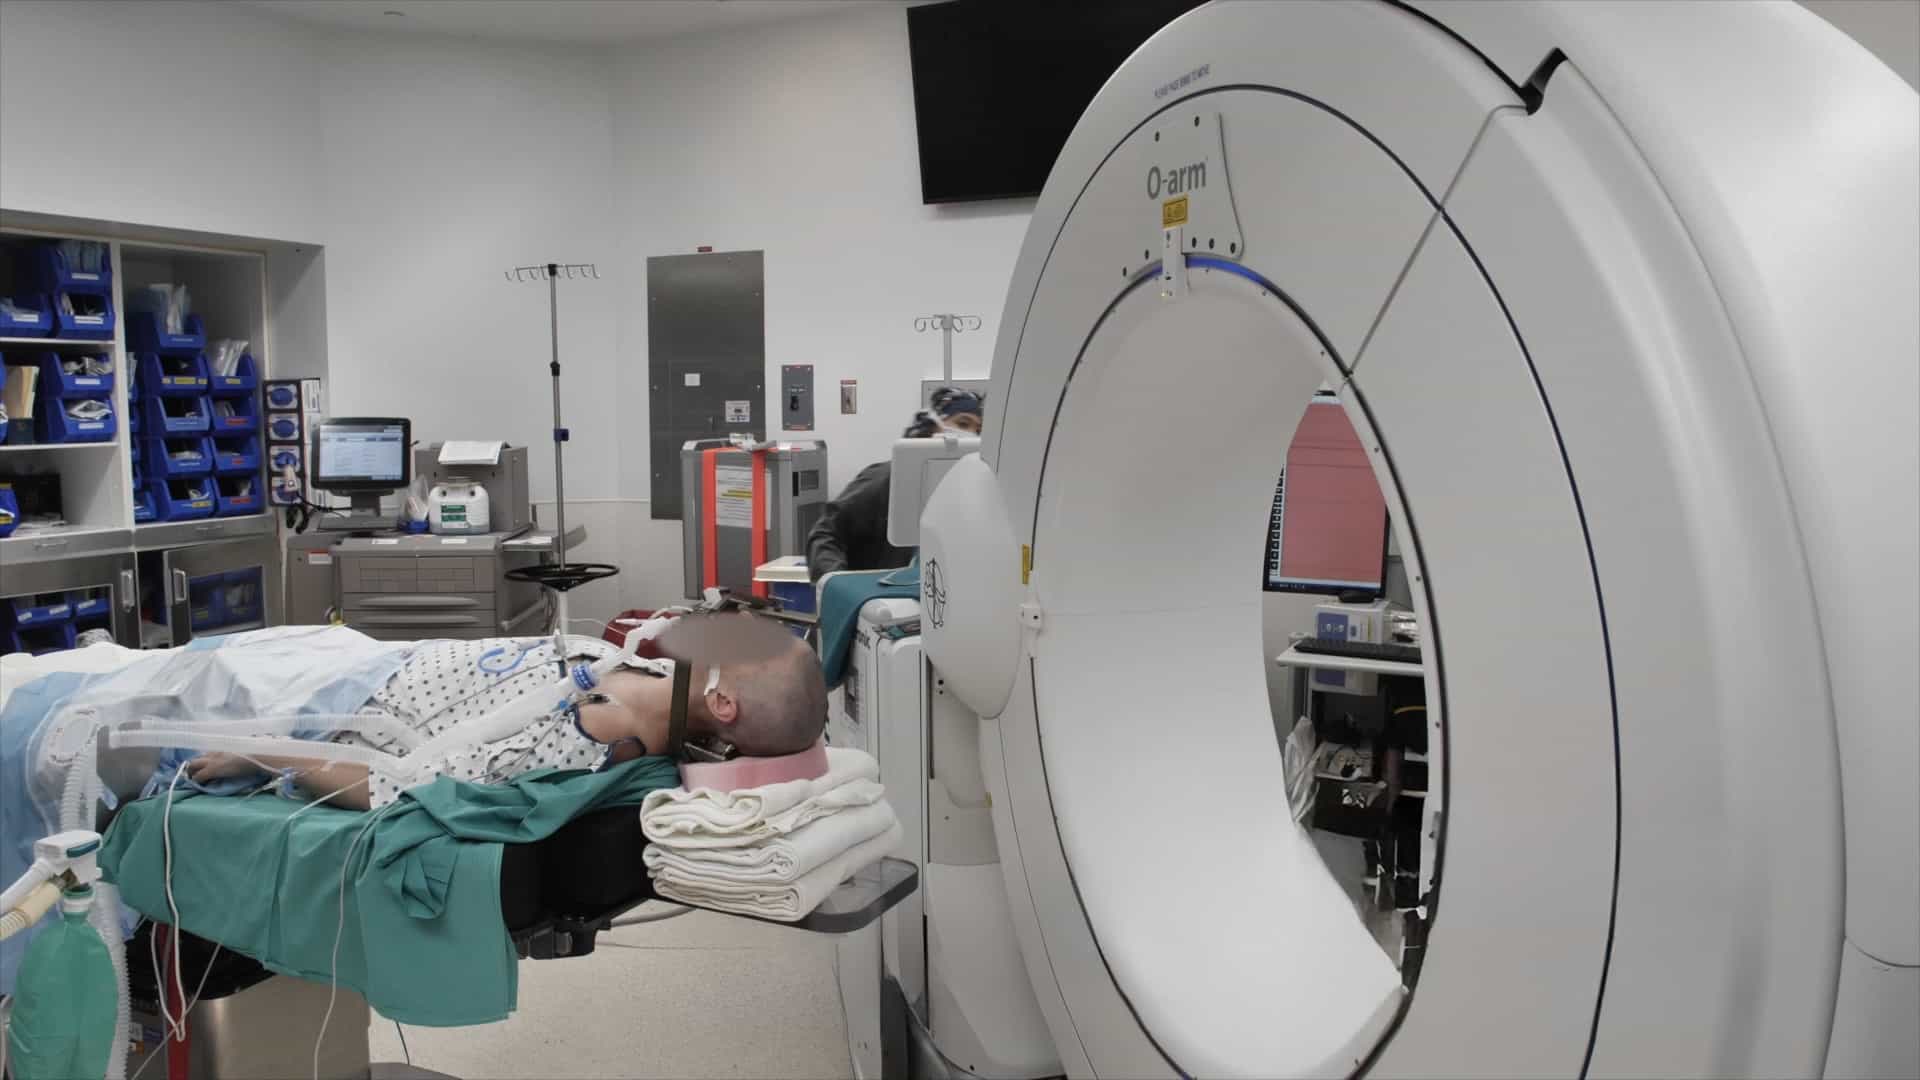
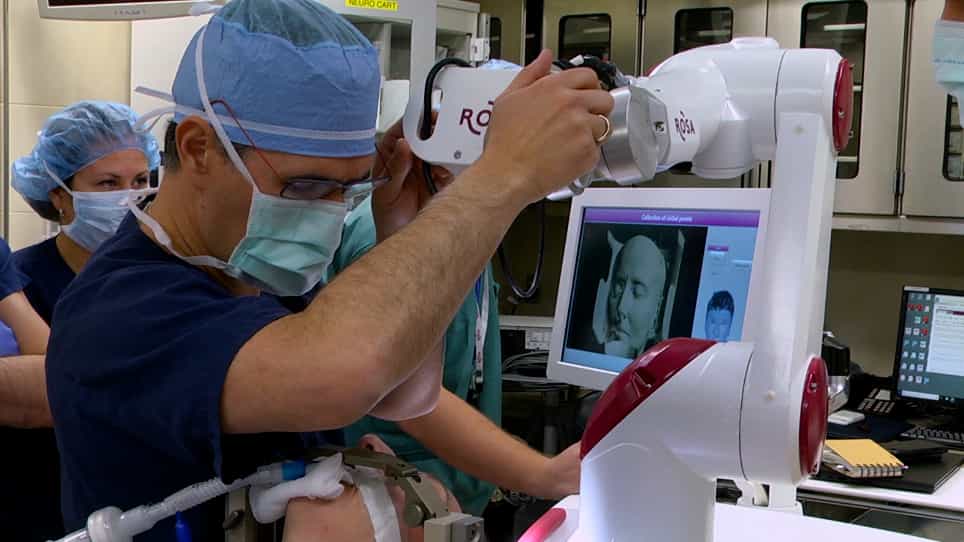
Related Experiment Video
Updated: Oct 27, 2025
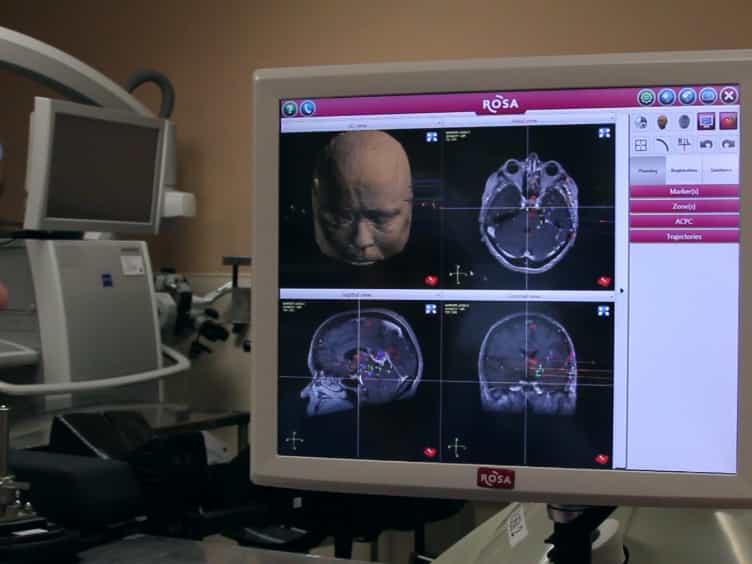
Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
Pediatric stereo-electroencephalography: effects of robot assistance and other variables on seizure outcome and
Ioannis N Mavridis1, William B Lo1, Welege Samantha Buddhika Wimalachandra1
1Departments of1Neurosurgery.

Insights
Stereo-electroencephalography (SEEG) in children is safe, with uncommon and treatable complications. Robot assistance improves electrode implantation accuracy and leads to better epilepsy surgery outcomes.
Area of Science:
- Neurosurgery
- Pediatric Epilepsy Surgery
- Stereo-electroencephalography (SEEG)
Background:
- Pediatric and adult populations have distinct anatomical and physiological characteristics impacting SEEG safety.
- Limited research differentiates SEEG safety profiles between pediatric and adult patients.
Purpose of the Study:
- To evaluate the safety of SEEG in pediatric patients.
- To identify potential patient and surgical risk factors for complications.
- To assess the impact of robot assistance on SEEG practice, surgical parameters, and clinical outcomes.
Main Methods:
- Retrospective analysis of 64 SEEG procedures in 63 children (December 2014 - March 2020).
- Evaluation of demographic, surgical variables, and complications.
- Comparison of clinical outcomes between robot-assisted and non-robot-assisted SEEG.
Main Results:
- Overall complication rate was 6.3%; complications were transient or reversible.
- Robot assistance was associated with a higher number of implanted electrodes (12.6 vs 7.6) and improved accuracy (1.51 mm vs 2.98 mm error).
- Robot-assisted SEEG demonstrated superior seizure control post-epilepsy surgery (82% Engel class IA vs 42% in non-robot group).
Conclusions:
- Pediatric SEEG is safe, with a low complication rate.
- Robot assistance enhances SEEG procedures by enabling more accurate and extensive electrode placement.
- Robot-assisted SEEG significantly improves outcomes for subsequent epilepsy surgery in children.
Objective:
The safety of stereo-electroencephalography (SEEG) has been investigated; however, most studies have not differentiated pediatric and adult populations, which have different anatomy and physiology. The purpose of this study was to assess SEEG safety in the pediatric setting, focusing on surgical complications and the identification of patient and surgical risk factors, if any. The authors also aimed to determine whether robot assistance in SEEG was associated with a change in practice, surgical parameters, and clinical outcomes.
Methods:
The authors retrospectively studied all SEEG cases performed in their department from December 2014 to March 2020. They analyzed both demographic and surgical variables and noted the types of surgery-related complications and their management. They also studied the clinical outcomes of a subset of the patients in relation to robot-assisted and non-robot-assisted SEEG.
Results:
Sixty-three children had undergone 64 SEEG procedures. Girls were on average 3 years younger than the boys (mean age 11.1 vs 14.1 years, p < 0.01). The overall complication rate was 6.3%, and the complication rate for patients with left-sided electrodes was higher than that for patients with right-sided electrodes (11.1% vs 3.3%), although the difference between the two groups was not statistically significant. The duration of recording was positively correlated to the number of implanted electrodes (r = 0.296, p < 0.05). Robot assistance was associated with a higher number of implanted electrodes (mean 12.6 vs 7.6 electrodes, p < 0.0001). Robot-assisted implantations were more accurate, with a mean error of 1.51 mm at the target compared to 2.98 mm in nonrobot implantations (p < 0.001). Clinical outcomes were assessed in the first 32 patients treated (16 in the nonrobot group and 16 in the robot group), 23 of whom proceeded to further resective surgery. The children who had undergone robot-assisted SEEG had better eventual seizure control following subsequent epilepsy surgery. Of the children who had undergone resective epilepsy surgery, 42% (5/12) in the nonrobot group and 82% (9/11) in the robot group obtained an Engel class IA outcome at 1 year (χ2 = 3.885, p = 0.049). Based on Kaplan-Meier survival analysis, the robot group had a higher seizure-free rate than the nonrobot group at 30 months postoperation (7/11 vs 2/12, p = 0.063). Two complications, whose causes were attributed to the implantation and head-bandaging steps, required surgical intervention. All complications were either transient or reversible.
Conclusions:
This is the largest single-center, exclusively pediatric SEEG series that includes robot assistance so far. SEEG complications are uncommon and usually transient or treatable. Robot assistance enabled implantation of more electrodes and improved epilepsy surgery outcomes, as compared to those in the non-robot-assisted cases.