Related Experiment Video
Updated: Oct 25, 2025


Author Spotlight: Recent Advancements in Reoperative Foregut Surgery
Published on: September 22, 2023
Mucous Fistula Refeeding Promotes Earlier Enteral Autonomy in Infants With Small Bowel Resection
Sean D Woods1, Barbara O McElhanon2, Megan M Durham3
1Division of Neonatal-Perinatal Medicine, Department of Pediatrics, Emory University - Children's Healthcare of Atlanta at Egleston.

Insights
Mucous fistula refeeding (MFR) in infants undergoing intestinal resection for necrotizing enterocolitis (NEC) or small bowel atresia (SBA) improves nutritional outcomes. MFR reduces parenteral nutrition dependence and speeds enteral feeding, with no increased complications.
Area of Science:
- Pediatric Surgery
- Neonatal Nutrition
- Gastroenterology
Background:
- Infants with necrotizing enterocolitis (NEC) or small bowel atresia (SBA) often require intestinal resection and enterostomy.
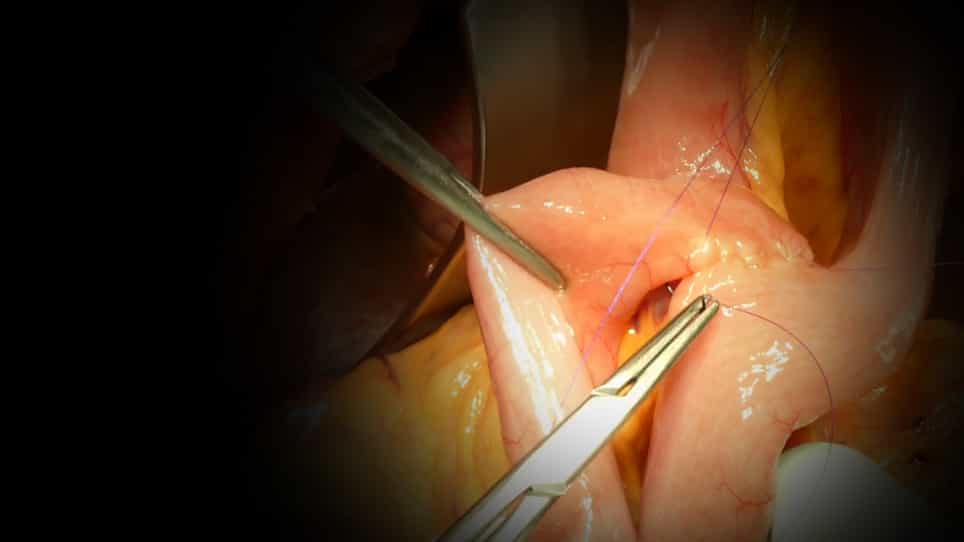
- Mucous fistula refeeding (MFR) is a technique to reintroduce enterostomy output into the distal bowel to improve nutrition and adaptation.
- Previous studies suggested MFR benefits, but lacked adjustment for confounding factors.
Purpose of the Study:
- To evaluate the impact of MFR on nutritional outcomes and bowel adaptation in infants with NEC or SBA.
- To compare outcomes between infants who received MFR and those who did not, using multivariable adjusted models.
Main Methods:
- Retrospective cohort analysis of infants with NEC or SBA undergoing intestinal resection and enterostomy.
- Comparison of demographic and outcome data between MFR and non-MFR groups.
- Multivariable analysis to adjust for potential confounding variables.
Main Results:
- MFR was utilized in 64% of the 101 infants studied.
- Infants with NEC receiving MFR achieved full enteral feeds 14 days sooner and required 22 fewer days of parenteral nutrition.
- MFR was associated with lower peak direct bilirubin, reduced ursodiol use, and improved growth parameters in NEC patients, with similar trends in SBA patients. No complications were observed.
Conclusions:
- Mucous fistula refeeding (MFR) is a safe and effective method to improve nutritional outcomes in infants with intestinal resection.
- MFR leads to decreased reliance on total parenteral nutrition (TPN) and earlier achievement of enteral autonomy.
- The findings support the use of MFR in select infants following intestinal resection for NEC or SBA.
Objective:
Infants requiring intestinal resection because of necrotizing enterocolitis (NEC) or small bowel atresia (SBA) may benefit from mucous fistula refeeding (MFR) of enterostomy output to improve nutrition and bowel adaptation before reanastomosis. Previous series demonstrated improved outcomes with MFR but did not account for varied patient characteristics as potential sources of bias. We performed a cohort analysis using multivariable adjusted models to compare outcomes of patients with and without MFR.
Methods:
Retrospective chart review was performed for patients with NEC or SBA and small bowel resection with enterostomy and MF. Demographic and outcome data was compared between MFR and non-MFR groups using adjusted multivariable analysis for potential confounding variables.
Results:
MFR was performed in 65 of 101 patients (64%), including 45 of 75 patients with NEC and 20 of 26 patients with SBA. Reasons for not receiving MFR included bowel stricture, technical limitation, or not otherwise specified. NEC patients receiving MFR had 14 fewer days to achieve full enteral feeds after intestinal reconnection, 22 fewer days of parenteral nutrition, lower peak direct bilirubin by 2.4 mg/dL, and 77% less odds of ursodiol use (all P < 0.01). SBA patients had similar trends not reaching statistical significance. Growth parameters were improved in MFR groups. There were no complications or increased infections from MFR.
Conclusions:
This study suggests that MFR safely improves nutritional outcomes in infants with intestinal resection, related to decreased total parenteral nutrition (TPN) dependence and earlier enteral autonomy.

Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...