Related Experiment Video
Updated: Oct 25, 2025


Ex Vivo Porcine Experimental Model for Studying and Teaching Lung Mechanics
Published on: April 19, 2024
Model-based estimation of negative inspiratory driving pressure in patients receiving invasive NAVA mechanical
Jennifer L Knopp1, J Geoffrey Chase1, Kyeong Tae Kim1
1Department of Mechanical Engineering, University of Canterbury, Private Bag 4800, Christchurch 8140, New Zealand.

Background:
Optimisation of mechanical ventilation (MV) and weaning requires insight into underlying patient breathing effort. Current identifiable models effectively describe lung mechanics, such as elastance (E) and resistance (R) at the bedside in sedated patients, but are less effective when spontaneous breathing is present. This research derives and regularises a single compartment model to identify patient-specific inspiratory effort.
Methods:
Constrained second-order b-spline basis functions (knot width 0.05 s) are used to describe negative inspiratory drive (Pp, cmH2O) as a function of time. Breath-breath Pp are identified with single E and R values over inspiration and expiration from n = 20 breaths for N = 22 patients on NAVA ventilation. Pp is compared to measured electrical activity of the diaphragm (Eadi) and published results.
Results:
Average per-patient root-mean-squared model fit error was (median [interquartile range, IQR]) 0.9 [0.6-1.3] cmH2O, and average per-patient median Pp was -3.9 [-4.5- -3.0] cmH2O, with range -7.9 - -1.9 cmH2O. Per-patient E and R were 16.4 [13.6-21.8] cmH2O/L and 9.2 [6.4-13.1] cmH2O.s/L, respectively. Most patients showed an inspiratory volume threshold beyond which Pp started to return to baseline, and Pp at peak Eadi (end-inspiration) was often strongly correlated with peak Eadi (R2=0.25-0.86). Similarly, average transpulmonary pressure was consistent breath-breath in most patients, despite differences in peak Eadi and thus peak airway pressure.
Conclusions:
The model-based inspiratory effort aligns with electrical muscle activity and published studies showing neuro-muscular decoupling as a function of pressure and/or volume. Consistency in coupling/dynamics were patient-specific. Quantification of patient and ventilator work of breathing contributions may aid optimisation of MV modes and weaning.
More Related Videos
 09:31
Normothermic Negative Pressure Ventilation Ex Situ Lung Perfusion: Evaluation of Lung Function and Metabolism
Published on: February 14, 2022
 11:26
Assessing Cerebral Autoregulation via Oscillatory Lower Body Negative Pressure and Projection Pursuit Regression
Published on: December 10, 2014
Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:24
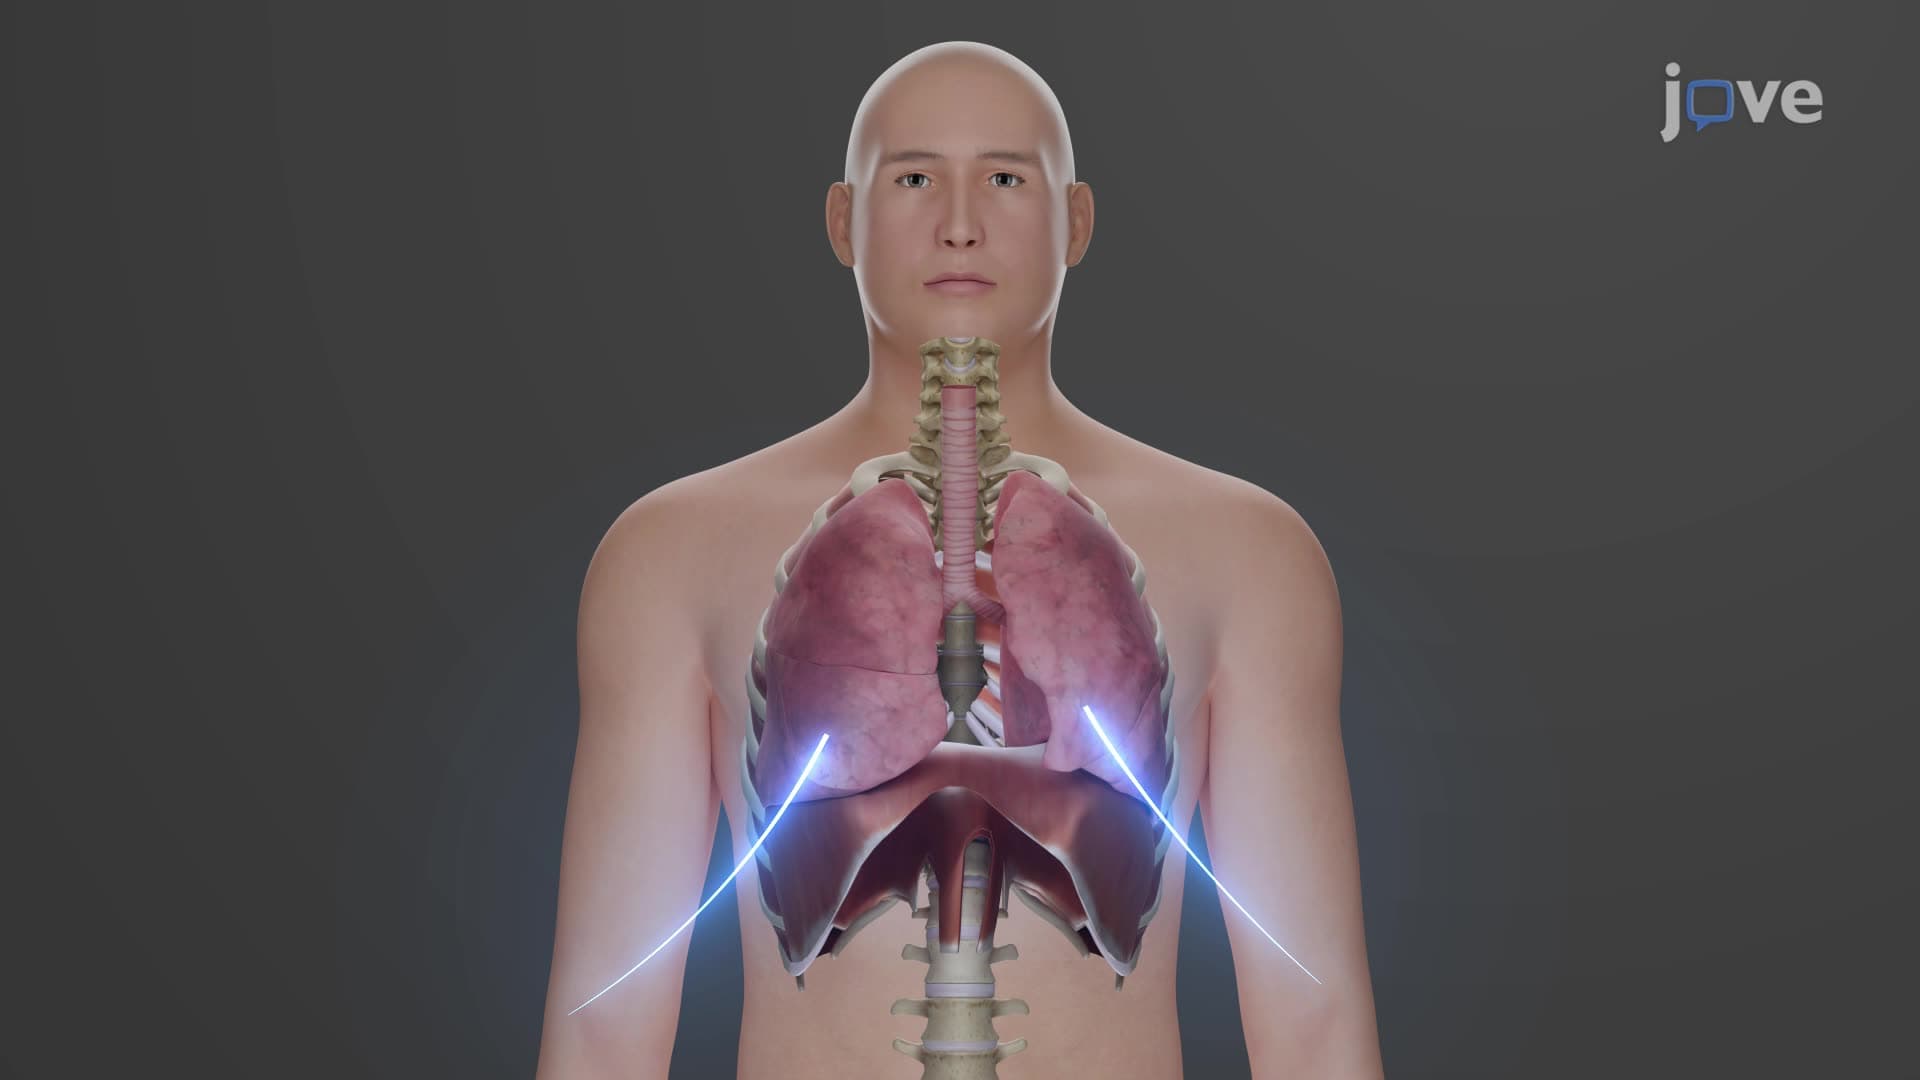
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:24
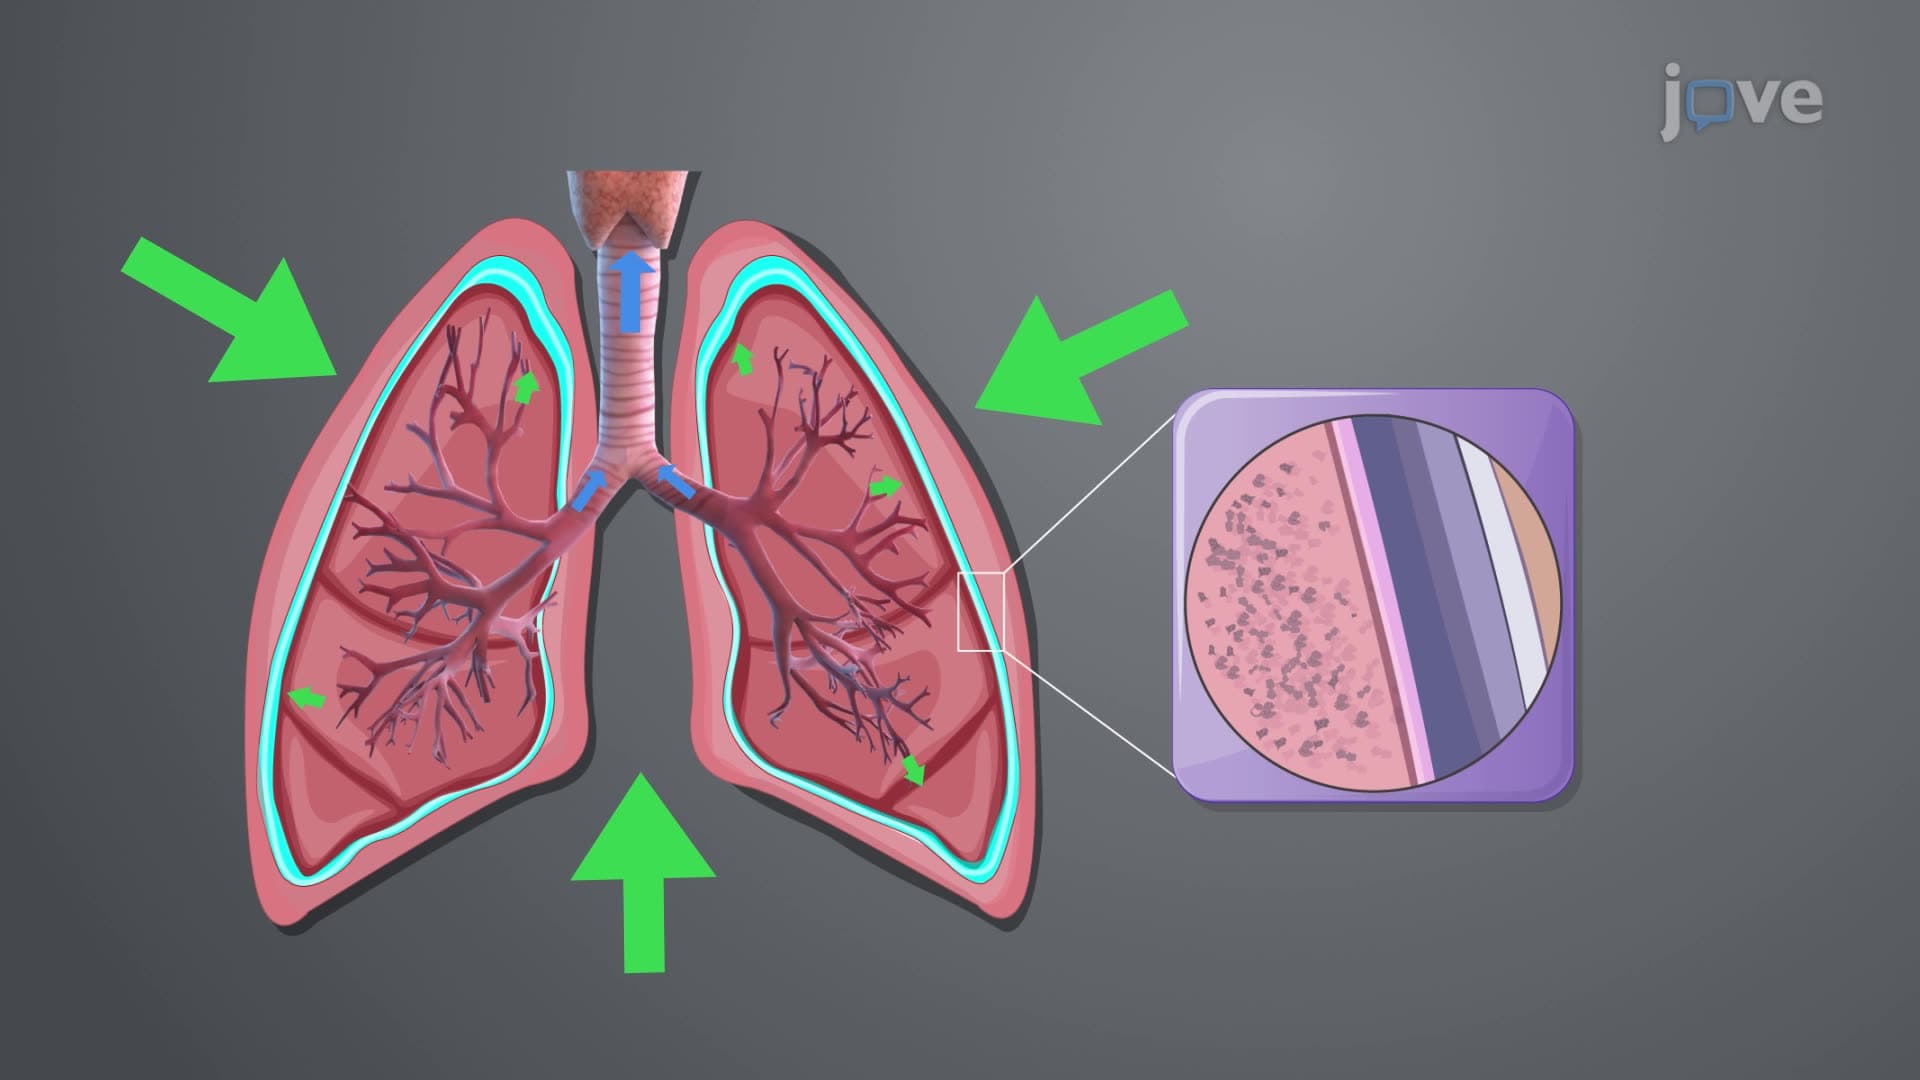
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...