Asymptomatic cerebellar venous angioma

G J Hankey1, S S Gubbay, T M Chakera

  • 1Department of Neurology, Royal Perth Hospital, WA.

Australian and New Zealand Journal of Medicine
|August 1, 1987
PubMed

Related Concept Videos

Aneurysm II: Clinical Manifestations and Diagnostic Studies01:21

Aneurysm II: Clinical Manifestations and Diagnostic Studies

Thoracic, aortic arch and abdominal aneurysms are significant vascular conditions that can present with various clinical manifestations and lead to serious complications. Understanding these manifestations and the appropriate diagnostic studies is essential for effective management and treatment.Thoracic Aortic AneurysmsThoracic aortic aneurysms often remain asymptomatic until they reach a size that impinges on adjacent structures. They typically cause deep, diffuse chest pain that radiates to...
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies01:20

Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies

The key difference between Superficial Vein Thrombosis (SVT) and Deep Vein Thrombosis (DVT) lies in their location and severity.Clinical ManifestationsSVT typically presents with localized pain, tenderness, and redness along the course of a superficial vein, often accompanied by a palpable, cord-like structure under the skin. This condition is usually less dangerous than DVT but can be uncomfortable and may lead to complications such as cellulitis or, rarely, a clot extension into the deep...
Arboviral Encephalitis01:25

Arboviral Encephalitis

Arboviral encephalitis refers to brain inflammation caused by arthropod-borne viruses, particularly those transmitted through mosquito vectors. Among these, West Nile virus (WNV), a member of the Flaviviridae family, is a significant public health concern. WNV is an enveloped, positive-sense, single-stranded RNA virus. Human infection typically begins when an infected mosquito introduces the virus into the dermis during feeding. The primary transmission cycle involves birds as amplifying hosts...
Hemorrhagic Stroke ll: Pathophysiology01:29

Hemorrhagic Stroke ll: Pathophysiology
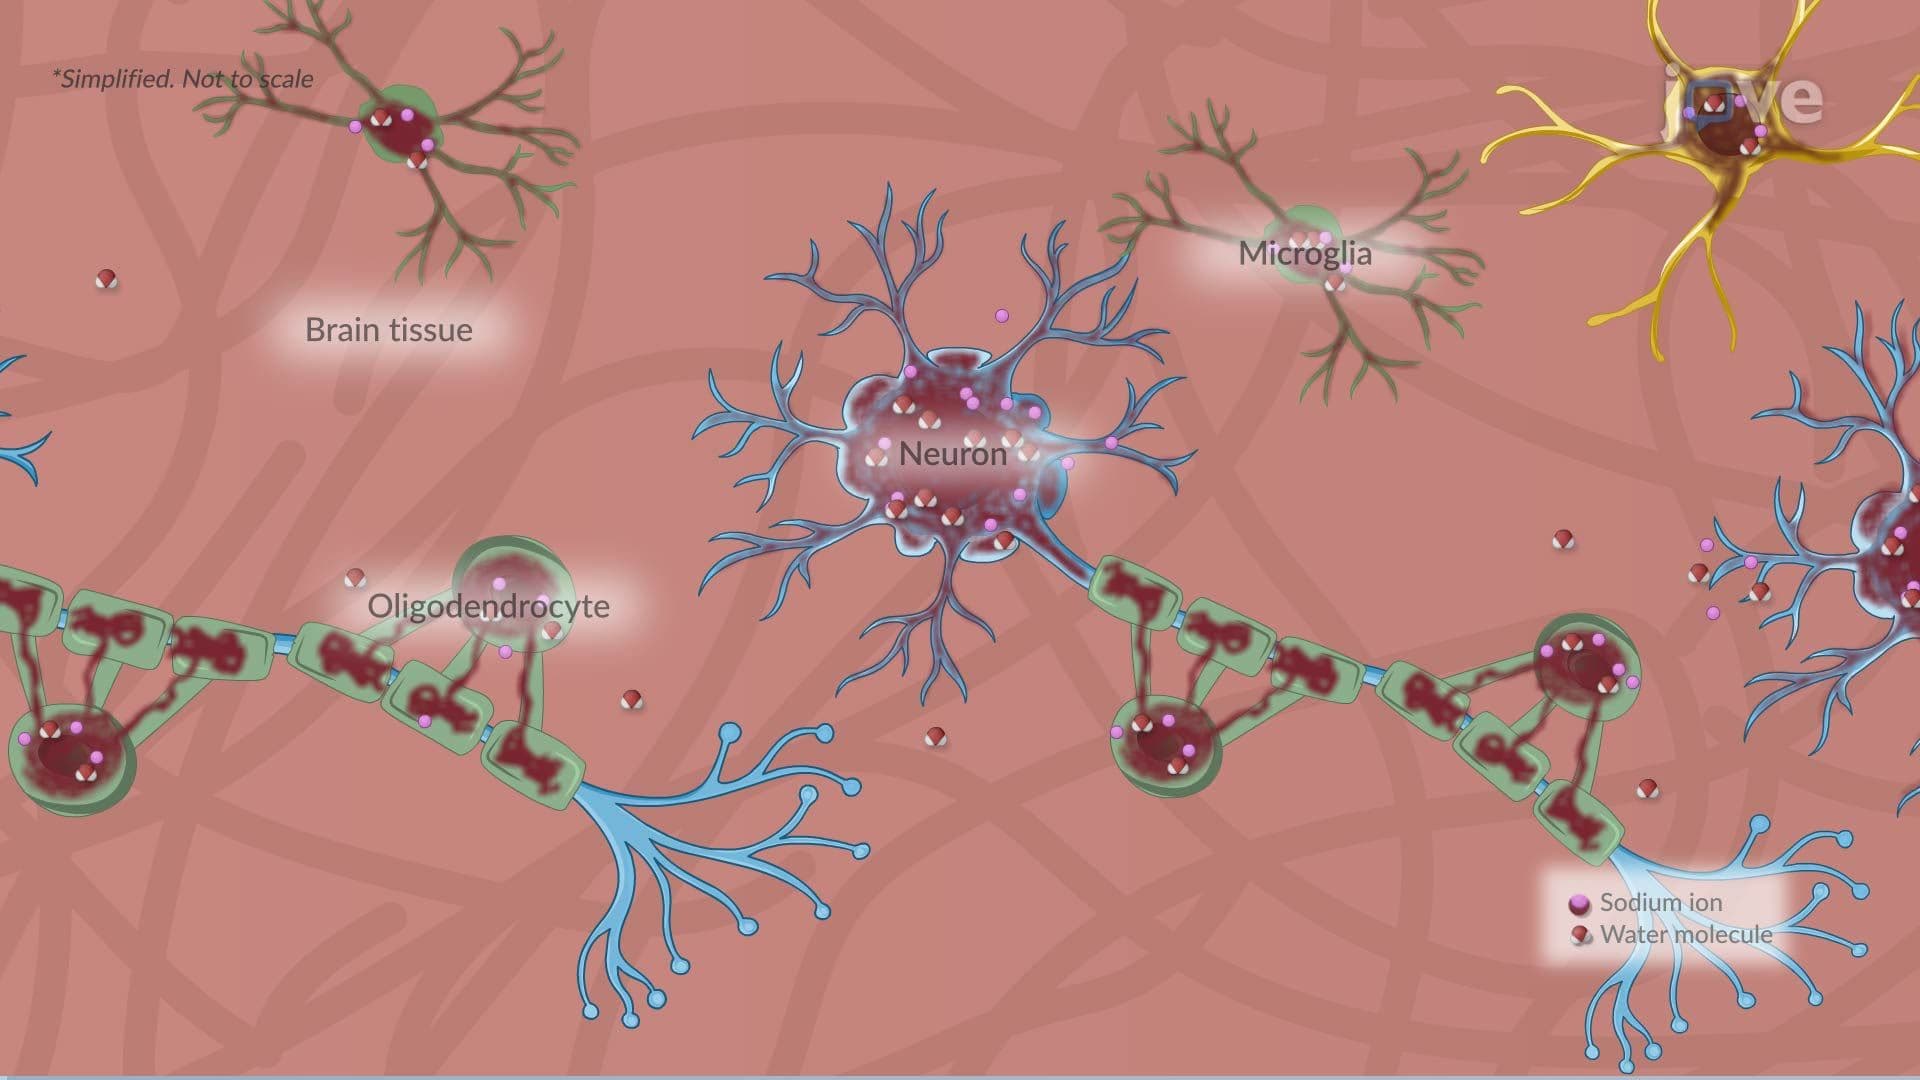
A hemorrhagic stroke develops when a cerebral blood vessel ruptures, allowing blood to escape into the surrounding brain tissue, as in intracerebral hemorrhage (ICH), or into the subarachnoid space, as in subarachnoid hemorrhage (SAH). Because the skull is a rigid compartment, the sudden presence of extravascular blood rapidly increases intracranial pressure and compresses adjacent neural structures, leading to immediate tissue injury and impaired cerebral perfusion.Mass Effect and Primary...
Cerebral Edema l: Introduction01:19

Cerebral Edema l: Introduction

Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...