Related Experiment Video
Updated: Oct 25, 2025

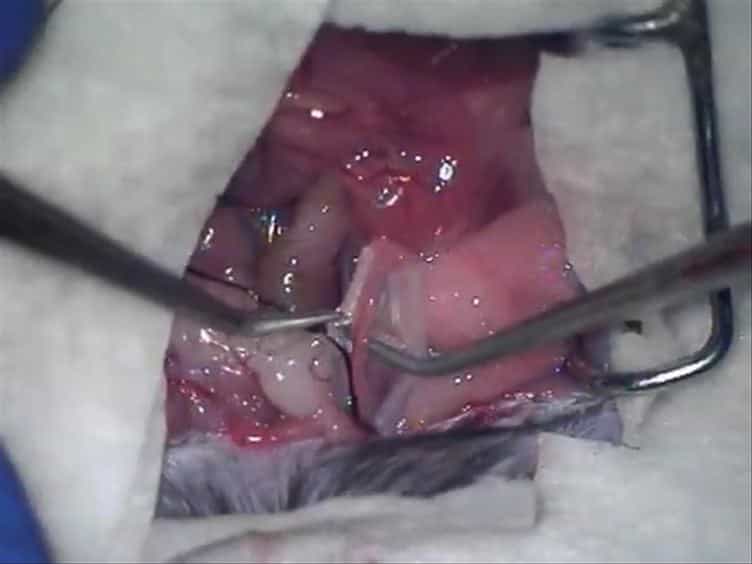
Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Ureteroneocystostomy without ureteral remodeling for grade III-V vesicoureteral reflux treatment
Tiffany Toni1, Alyssa Lombardo1, Ciro Andolfi2
1University of Chicago, Pritzker School of Medicine, Chicago, IL, USA.

Background:
Ureteral remodeling (tapering or tailoring) is often performed alongside ureteroneocystostomy (ureteric reimplantation) procedures despite limited evidence on its role in promoting reflux resolution.
Objectives:
To investigate the efficacy of ureteroneocystostomy in the absence of adjuvant ureteral remodeling for promoting reflux resolution in grade III-V vesicoureteral reflux.
Study Design:
A retrospective analysis identified pediatric patients who underwent open or robotic assisted ureteroneocystostomy (OUN and RAUN, respectively) without ureteral remodeling (tailoring or tapering) at a single tertiary care center. The primary endpoint of reflux resolution was defined as no reflux on latest follow up postoperative voiding cystourethrogram (VCUG). Ureteral dilation was analyzed using the ureteral diameter ratio (UDR), which normalized for image characteristics. Inclusion criteria was as follows: grade III-V reflux, accessible postoperative VCUG scan, RAUN after June 2013 following technique optimization, and no other structural urologic abnormality or associated neurogenic bladder.
Results:
A total of 68 ureters were analyzed (Grade III = 28, Grade IV = 27, Grade V = 13, OUN = 23, RAUN = 45). Complete reflux resolution was achieved postoperatively in 96% (27/28) of grade III, 100% (27/27) of grade IV and 100% (13/13) grade V cases, for a combined resolution rate of 99%. In the one failed case, the preoperative UDR was in the second quartile and postoperatively, reflux diminished from grade III to grade I. Notably, no cases with UDRs in the largest quartile required tapering/tailoring for complete reflux resolution.
Discussion:
Ureteral tapering and tailoring were unnecessary to achieve reflux resolution in grade III-V VUR by both OUN and RAUN. Additionally, the unsuccessful case was classified as grade III with a UDR value in the second quartile, suggesting that high grade reflux (IV-V) can be repaired without tapering with equal success rates to that of grade III VUR repair, which is classically not tapered. Tapering was unnecessary for complete reflux resolution in the cases with the largest ureteral diameter ratios (UDR). These findings are limited by the single center retrospective nature of the study.
Conclusions:
This study demonstrates that vesicoureteral reimplantation for resolution of grade III-V reflux is successful in the absence of ureteral remodeling techniques.

Related Concept Videos
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:26
Kidney Transplant II: Surgical Procedure
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:22
Ureters