Related Experiment Video
Updated: Oct 24, 2025
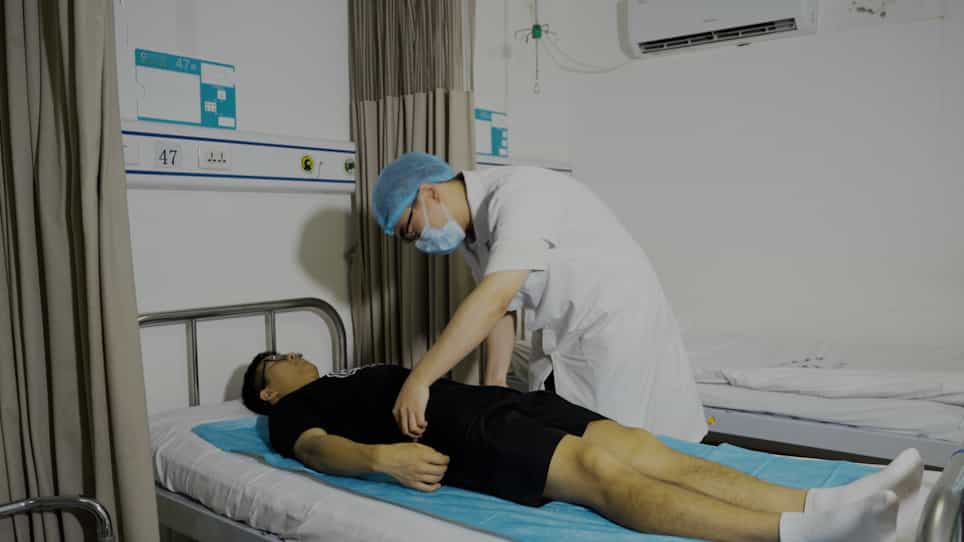

Acupoint Needle-Embedding Combined with Ironing Therapy for Postoperative Pain After Anal Surgery
Published on: June 23, 2023
Development of a Practice Guideline for Discharge Opioid Prescribing After Major Colorectal Surgery
David C Meyer1, Susanna S Hill1, M Richard Pavao2
1Division of Colorectal Surgery, Department of Surgery, University of Massachusetts Medical School, Worcester, Massachusetts.

Background:
Better alignment of opioid prescription quantities with patient need could help reduce excessive prescribing.
Objective:
The study sought to develop an institutional prescribing guideline based on defined opioid consumption patterns after inpatient colorectal operations.
Design:
This was a retrospective cohort study.
Settings:
The study was conducted at a single tertiary care center.
Patients:
Patients who underwent elective major colorectal procedures between July 2018 and January 2019 were included.
Main Outcome Measures:
The study measured prescription and consumption quantities measured as equianalgesic oxycodone 5-mg pills.
Results:
Patients were categorized into 3 groups based on consumption in the 24-hour period before discharge: tier 1 consumed 0 equianalgesic oxycodone 5-mg pills (n = 53), tier 2 consumed 0.1 to 3.0 equianalgesic oxycodone 5-mg pills (n = 25), and tier 3 consumed >3.0 equianalgesic oxycodone 5-mg pills (n = 22). Average prescription quantity was 17.5 ± 10.5 equianalgesic oxycodone 5-mg pills (range, 0-78). Patients consumed a mean of 6.7 ± 10.9 equianalgesic oxycodone 5-mg pills after discharge and had 10.8 ± 10.2 equianalgesic oxycodone 5-mg pill excess, whereas 51% of patients consumed no pills. Opioid consumption was significantly different between each tier (p < 0.001). A prescribing guideline was developed to satisfy the majority of patients: 0 equianalgesic oxycodone 5-mg pills if tier 1, 12 pills if tier 2, and 30 pills if tier 3. Tiered guideline adoption could reduce prescribed pills by 45% and excess pills per prescription by 73%. Patient history of IBD was independently associated with increased odds of exceeding the guideline (adjusted OR = 7.2 (95% CI, 1.6-32.6)).
Limitations:
The study was limited by its single-center, retrospective design and that outpatient opioid consumption was self-reported.
Conclusions:
Following hospital discharge after major colorectal surgery, more than half of patients consumed no opioid pills, and 62% of prescribed opioids were in excess. Outpatient opioid consumption was highly associated with inpatient opioid use in the 24 hours before discharge. Prospective validation of this prescribing guideline is needed, but adoption could reduce excessive prescribing. See Video Abstract at http://links.lww.com/DCR/B575.
Desarrollo De Una Gua Prctica Para La Prescripcin De Opioides Al Egreso Despus De Una Ciruga Colorrectal Mayor:
ANTECEDENTES:Una mejor alineación de las cantidades de prescripción de opioides con las necesidades del paciente podría ayudar a reducir la prescripción excesiva.OBJETIVO:El estudio buscó desarrollar una guía institucional de prescripción basada en patrones definidos de consumo de opioides luego de cirugías colorrectales hospitalarias.DISEÑO:Estudio de cohorte retrospectivo.ENTORNO CLÍNICO:El estudio se llevó a cabo en un solo centro de atención terciaria.PACIENTES:Pacientes que se sometieron a procedimientos colorrectales mayores electivos entre julio de 2018 y enero de 2019.PRINCIPALES MEDIDAS DE RESULTADO:El estudio midió las cantidades de prescripción y consumo medidas como píldoras de 5 mg de oxicodona equianalgésica (EOP).RESULTADOS:Los pacientes se clasificaron en tres grupos según el consumo en el período de 24 horas antes del egreso: el nivel 1 consumió 0 EOP (n = 53), el nivel 2 consumió 0,1-3 EOP (n = 25) y el nivel 3 consumió más de 3 EOP (n = 22). La cantidad promedio de prescripción fue 17,5 (± 10,5) EOP (rango: 0-78). Los pacientes consumieron una media de 6,7 (± 10,9) EOP posterior al egreso y tuvieron un exceso de 10,8 (± 10,2) EOP, mientras que el 51% de los pacientes no consumieron píldoras. El consumo de opioides fue significativamente diferente entre cada nivel (p <0,001). Se desarrolló una guía de prescripción para satisfacer a la mayoría de los pacientes: 0 EOP del nivel 1, 12 EOP del nivel 2 y 30 EOP del nivel 3. La adquisición de una guía escalonada podría reducir las píldoras recetadas en un 45% y el exceso de píldoras por receta en un 73%. El historial del paciente de enfermedad inflamatoria intestinal se asoció de forma independiente con un aumento de las probabilidades de superar la guía (ORa 7,2; IC del 95%: 1,6-32,6).LIMITACIONES:El estudio estuvo limitado por su diseño retrospectivo de un solo centro y por el consumo de opioides del paciente ambulatorio el cual fue autoinformado.CONCLUSIONES:Tras el egreso hospitalario de una cirugía colorrectal mayor, más de la mitad de los pacientes no consumieron pastillas opioides y el 62% de los opioides prescritos estaban en exceso. El consumo de opioides como paciente ambulatorio estuvo altamente asociado con el uso de opioides como paciente hospitalizado en las 24 horas previas al egreso. Se necesita una validación prospectiva de esta guía de prescripción, pero la adopción podría reducir la prescripción excesiva. Consulte Video Resumen en http://links.lww.com/DCR/B575.


Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:25
Endoscopic Procedures II: Colonoscopy
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:17
Drugs Affecting GI Tract Motility: Opioids as Antidiarrheal Agents
Opioids, widely used antidiarrheal agents, mitigate diarrhea by slowing down...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease