Impact of Venoarterial Extracorporeal Membrane Oxygenation Flow on Outcomes in Cardiogenic Shock
Related Experiment Video
Updated: Oct 24, 2025

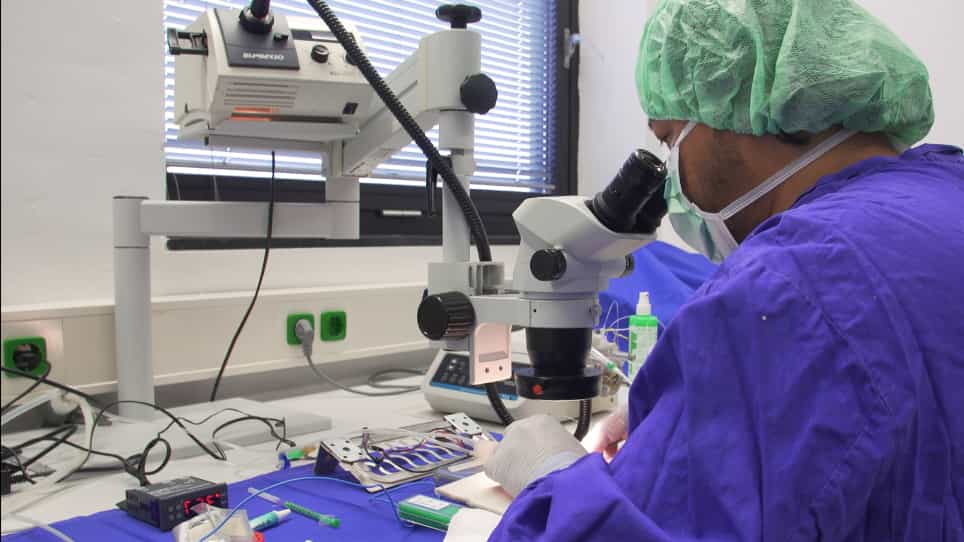
Point-of-Care Ultrasound for Peripheral Veno-Arterial Extracorporeal Membrane Oxygenation Without Left Ventricular Venting
Published on: January 17, 2025
Sameer K Singh1, Yuming Ning2, Paul Kurlansky1
1From the Department of Surgery, Division of Cardiothoracic Surgery, Columbia University Medical Center, New York.

Abstract:
Venoarterial extracorporeal membrane oxygenation (VA ECMO) is used to provide cardiopulmonary support in cardiogenic shock; however, high extracorporeal flow may increase left ventricular (LV) afterload leading to LV distention and intracardiac stasis. It is unclear how ECMO flow affects patient outcomes and complications related to ECMO. Retrospective review of patients at a single institution placed on VA ECMO from 2007 to 2018 was performed. Patients were divided into full flow (flow index > 2.2 L/min/m2) and partial flow (flow index < 2.2 L/min/m2) groups. In-hospital mortality and markers of end-organ perfusion were compared between groups balanced for risk factors using propensity score inverse probability of treatment weighting. ECMO-related complications such as LV distention, limb ischemia, and bleeding were recorded. There were 488 patients included, 405 (83%) in the partial flow group, and 83 (17%) in the full flow group. No major differences in age, gender, or comorbidities were found. There was no difference in in-hospital mortality between groups (51% vs. 55%, p = 0.59). At 72 hours post-ECMO initiation, there was no difference in the change in renal, hepatic function, or lactate from baseline nor in the rates of continuous venoveno hemofiltration initiation (p = 0.41). There was a trend towards the decreased incidence of LV distention requiring LV vent placement in the partial flow group (12% vs. 7%, p = 0.16). Compared with full flow VA ECMO, partial flow VA ECMO in carefully selected patients results in similar in-hospital mortality and provides similar end-organ perfusion for the treatment of refractory cardiogenic shock.

Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...