Related Experiment Video
Updated: Oct 23, 2025

Development and Assessment of Intracellular Infection Models for Staphylococcus aureus
Published on: January 17, 2025
Variation Among Infectious Diseases Pharmacists for the Treatment of Staphylococcus aureus Bacteremia
Bryan P White1,2, Katie E Barber3, Daniel B Chastain4
1Department of Pharmacy, 6195OU Medical Center, Oklahoma City, OK, USA.

Abstract:
Introduction: Staphylococcus aureus bacteremia (SAB) remains complex, in that optimal treatment for patients, including complicated or persistent infection, remains unclear. Two recent surveys have demonstrated practice variations in SAB among infectious diseases (ID) physicians. Objectives: The purpose of this survey was to examine practice variations in SAB among ID pharmacists. Methods: A thirty-five-question survey was electronically distributed to the American College of Clinical Pharmacy (ACCP) Infectious Diseases Practice and Research Network (IDPRN) in Fall 2019 to determine differences in SAB management. Data were analyzed utilizing Pearson's Chi-Square or Fisher's Exact Test. Results: A total of 106 ID pharmacists responded. Only 28% of pharmacists practiced at hospitals with mandatory ID consultation for SAB. A majority (75%) had rapid diagnostic technology (RDT) for identifying SABSI, but 32% of those facilities with RDT did not notify pharmacy with results. Anti-staphylococcal penicillins were preferred for MSSA blood stream infections (BSI) in patients with central nervous system infection and endocarditis, whereas cefazolin was favored for other MSSA BSI. For persistent MRSA BSI, 34% selected daptomycin alone while 38% elected to combine daptomycin and ceftaroline. Pharmacists at hospitals less than 500 beds were more likely to use daptomycin, while those at larger hospitals were more likely to use daptomycin and ceftaroline for persistent MRSA BSI (P < .05). Conclusions: A survey of ID pharmacists showed variation in the management of SABs, as well as the definition and treatment of persistent SAB. Mandatory ID consultation and RDT use to improve SAB management have not been optimized.
More Related Videos
 07:44
Time-Lapse Epifluorescence Microscopy Imaging of Pseudomonas aeruginosa and Staphylococcus aureus Heterogeneous Phenotypes
Published on: February 14, 2025
 11:17
Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Related Concept Videos
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:20
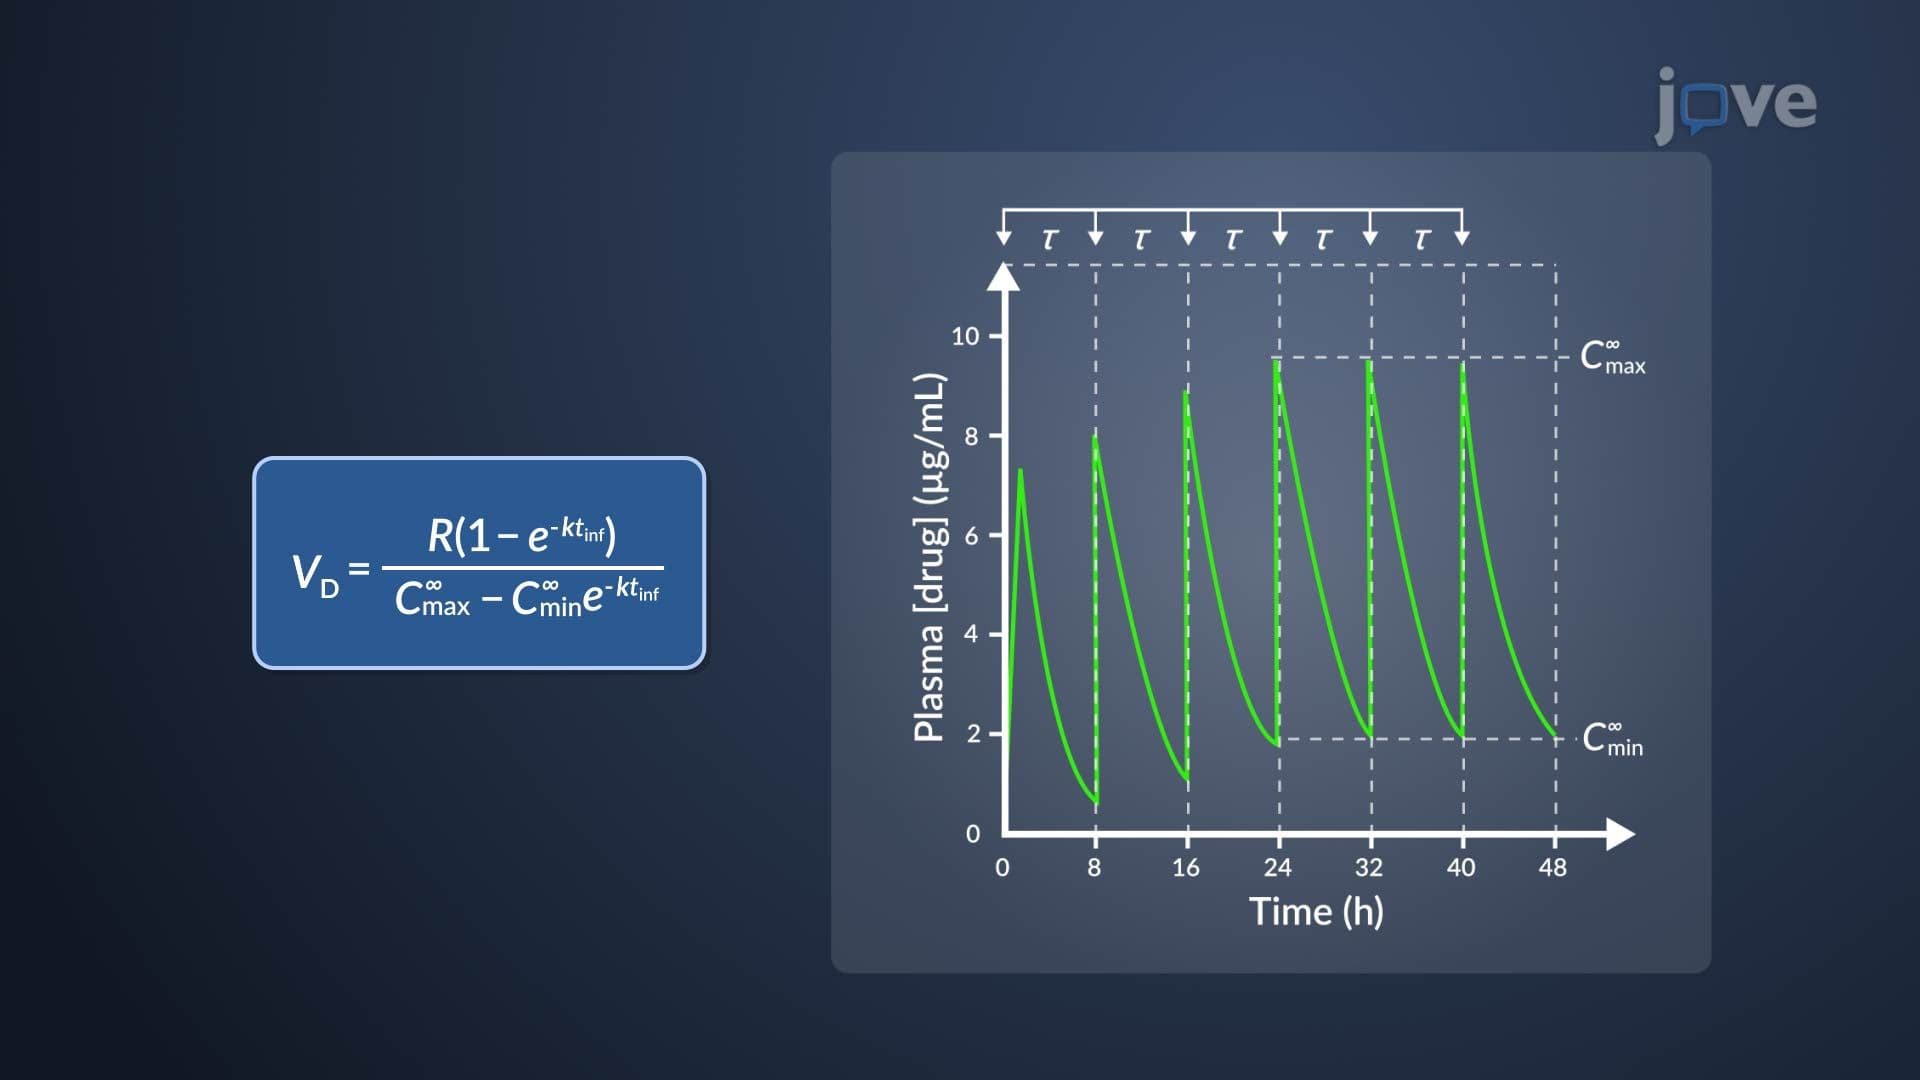
Estimation of k and VD of Aminoglycosides
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:26
Urine Studies II: Urine Culture and Sensitivity Test