Related Experiment Video
Updated: Oct 23, 2025
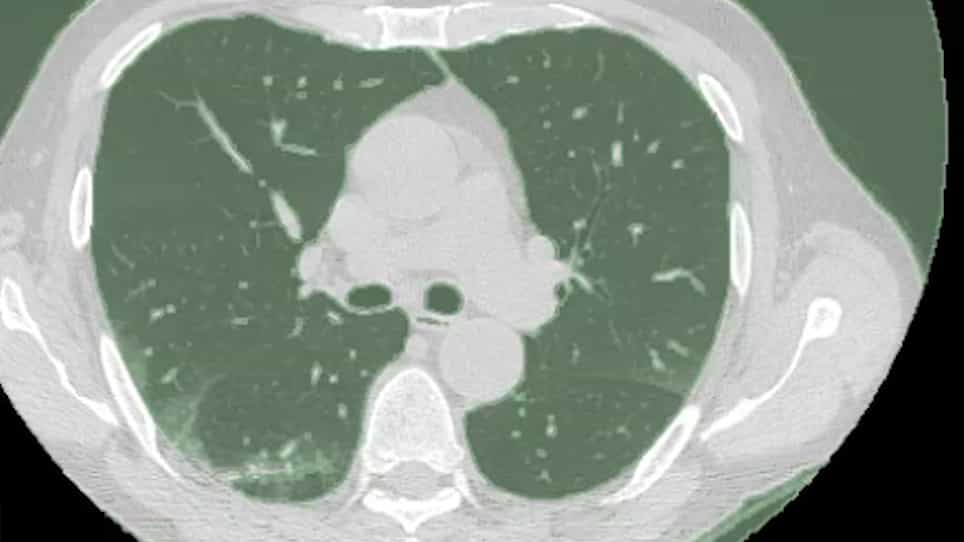

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Absent right superior vena cava with persistent left superior vena cava in a patient with COVID-19
Hiroshi Araki1, Motohiro Sekino2, Naoya Iwasaki3
1Department of Anesthesiology and Intensive Care Medicine, Nagasaki University Graduate School of Biomedical Sciences, 1-7-1 Sakamoto, Nagasaki, 852-8501, Japan. hiroshi-araki@nagasaki-u.ac.jp.

Abstract:
Vascular injury associated with cannulation during extracorporeal membrane oxygenation (ECMO) induction is a rare but life-threatening complication. The presence of abnormal vascular anatomy increases the risk of vascular injury and should be recognized before cannulation. We report the case of a patient with coronavirus disease (COVID-19) who was expected to undergo ECMO. By performing computed tomography (CT), we identified the absence of right superior vena cava (RSVC) with a persistent left superior vena cava (PLSVC) that could have caused serious complications associated with ECMO cannulation. PLSVC is observed in less than 0.5% of the general population; however, the combination of PLSVC and an absent RSVC in visceroatrial situs solitus is extremely rare. Attempting cannulation for Veno-venous (VV)-ECMO from the right (or left) internal jugular vein to the right atrium may cause serious complications. Cannulation may fail or lead to complications even in patients with inferior vena cava malformations. Although these vascular abnormalities are rare, it is possible to avoid iatrogenic vascular injury by identifying their presence in advance. Since anatomical variations in the vessels from the deep chest and abdominal cavity cannot be visualized using chest radiography and ultrasonography, we recommend CT, if possible, for patients with severe respiratory failure, including those with COVID-19, who may be considered for VV-ECMO induction.

Related Concept Videos
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:19
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:11
Overview of Systemic Arteries
Systemic circulation is the part of the cardiovascular system that carries oxygenated blood away from the heart to the body's tissues and returns deoxygenated blood back to the...
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care