Related Experiment Video
Updated: Oct 23, 2025

Establishing a Competing Risk Regression Nomogram Model for Survival Data
Published on: October 23, 2020
Predicting 10-year stroke mortality: development and validation of a nomogram
Weronika A Szlachetka1, Tiberiu A Pana1, Mamas A Mamas2
1Ageing Clinical and Experimental Research Team, Institute of Applied Health Sciences, School of Medicine, Medical Sciences and Nutrition, University of Aberdeen, Aberdeen, UK.

Abstract:
Predicting long-term stroke mortality is a clinically important and unmet need. We aimed to develop and internally validate a 10-year ischaemic stroke mortality prediction score. In this UK cohort study, 10,366 patients with first-ever ischaemic stroke between January 2003 and December 2016 were followed up for a median (interquartile range) of 5.47 (2.96-9.15) years. A Cox proportional-hazards model was used to predict 10-year post-admission mortality. The predictors associated with 10-year mortality included age, sex, Oxfordshire Community Stroke Project classification, estimated glomerular filtration rate (eGFR), pre-stroke modified Rankin Score, admission haemoglobin, sodium, white blood cell count and comorbidities (atrial fibrillation, coronary heart disease, heart failure, cancer, hypertension, chronic obstructive pulmonary disease, liver disease and peripheral vascular disease). The model was internally validated using bootstrap resampling to assess optimism in discrimination and calibration. A nomogram was created to facilitate application of the score at the point of care. Mean age (SD) was 78.5 ± 10.9 years, 52% female. Most strokes were partial anterior circulation syndromes (38%). 10-year mortality predictors were: total anterior circulation stroke (hazard ratio, 95% confidence intervals) (2.87, 2.62-3.14), eGFR < 15 (1.97, 1.55-2.52), 1-year increment in age (1.04, 1.04-1.05), liver disease (1.50, 1.20-1.87), peripheral vascular disease (1.39, 1.23-1.57), cancers (1.37, 1.27-1.47), heart failure (1.24, 1.15-1.34), 1-point increment in pre-stroke mRS (1.20, 1.17-1.22), atrial fibrillation (1.17, 1.10-1.24), coronary heart disease (1.09, 1.02-1.16), chronic obstructive pulmonary disease (1.13, 1.03-1.25) and hypertension (0.77, 0.72-0.82). Upon internal validation, the optimism-adjusted c-statistic was 0.76 and calibration slope was 0.98. Our 10-year mortality model uses routinely collected point-of-care information. It is the first 10-year mortality score in stroke. While the model was internally validated, further external validation is also warranted.


Related Concept Videos
 01:23
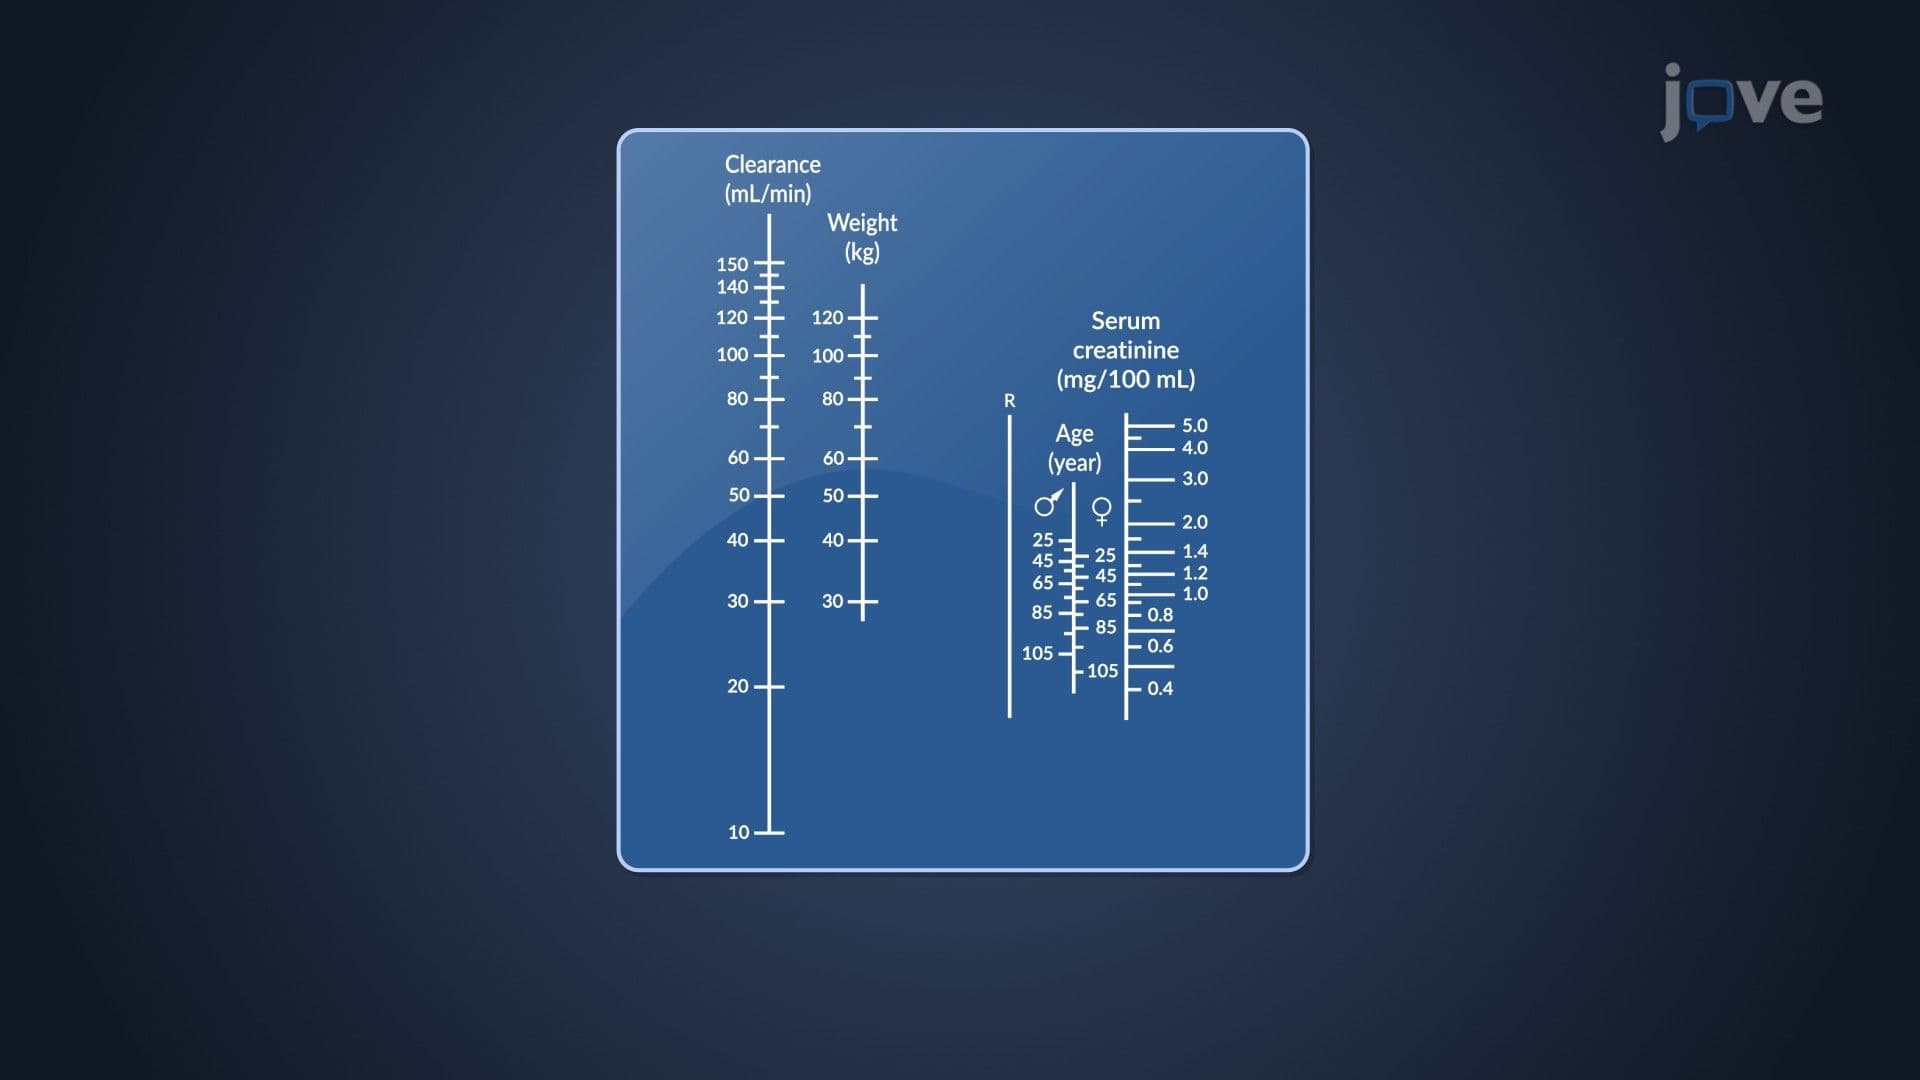
Dosage Regimen Designs: Nomograms and Tabulations
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration