Related Experiment Video
Updated: Oct 23, 2025
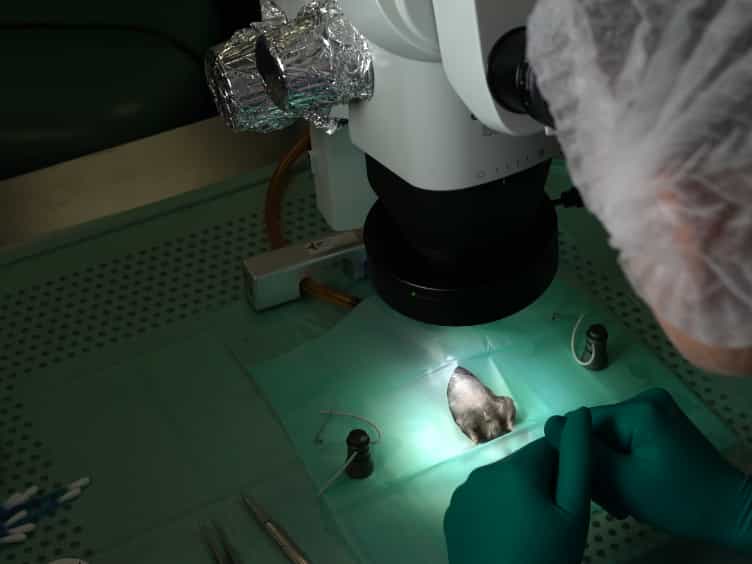

Stenosis of the Inferior Vena Cava: A Murine Model of Deep Vein Thrombosis
Published on: December 22, 2017
Contemporary rates of inferior vena cava filter thrombosis and risk factors
Ryan W King1, Mathew D Wooster1, Ravi K Veeraswamy1
1Division of Vascular Surgery, Medical University of South Carolina, Charleston, SC.

Objective:
Inferior vena cava (IVC) thrombosis is an uncommon complication associated with IVC filters (IVCFs), with studies reporting rates ranging from 1% to 31%. Few observational studies have described the risk factors associated with IVCF thrombosis, despite the significant clinical sequelae such as post-thrombotic syndrome, venous claudication, and venous ulceration. To better describe IVCF thrombosis and the risk factors, data were queried from Vascular Quality Initiative (VQI) participating centers.
Methods:
IVCF data were obtained from the international VQI database from 2013 to 2019. The patients included in the present analysis had 2 years of follow-up data available. The baseline demographics, medical comorbidities, medication, and procedural, anatomic, and postoperative variables were assessed using Kaplan-Meier survival curves with log-rank tests, Student's t tests, or Mann-Whitney U tests for IVCF thrombosis at 2 years. Cox regression analyses were used to identify independent predictors of IVCF thrombosis. A subgroup analysis of those who had presented with venous thromboembolism (VTE) was also performed.
Results:
A total of 62 U.S. and Canadian VQI-participating centers included 12,874 cases of IVCF placement. Of the 5780 cases with 2 years of follow-up available, 78 (1.3%) had developed IVCF thrombosis. Those who had experienced IVCF thrombosis had had significantly lower rates of diabetes, coronary artery disease, preoperative antiplatelet medications, preoperative statin use, and lower rates of discharge and follow-up antiplatelet medications. On univariable analysis, the cases of IVCF thrombosis also had higher rates of pulmonary embolism and VTE on admission, internal jugular venous access (vs femoral vein access), temporary IVCF use, follow-up anticoagulation, follow-up IVCF complication, follow-up access site thrombosis, and rates of new or propagated deep vein thrombosis at follow-up, and longer postoperative hospital stays. Multivariable analysis demonstrated that the independent predictors of IVCF thrombosis included new or propagated deep vein thrombosis at follow-up (hazard ratio [HR], 16.3; 95% confident interval [CI], 9.8-27.3; P < .001), no antiplatelet therapy at follow-up (HR, 4.8; 95% CI, 1.9-12.5; P = .001), internal jugular venous access (HR, 2.2; 95% CI, 1.4-3.5; P = .001), the presence of VTE on admission (HR, 2.7; 95% CI, 1.4-5.1; P = .002), and temporary IVCF placement (HR, 2.5; 95% CI, 1.1-5.6; P = .031). In an analysis of the subgroup of patients with VTE on admission, similar predictive factors were identified in a multivariable model. Massive pulmonary embolism was also predictive of IVCF thrombosis in this subgroup.
Conclusions:
The rate of IVCF thrombosis remained low in a contemporary international database. The results from the present study of >5000 patients with IVCFs suggest that antiplatelet therapy should be administered after IVCF placement to decreased the risk of IVCF thrombosis.

Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...