Related Experiment Video
Updated: Oct 23, 2025
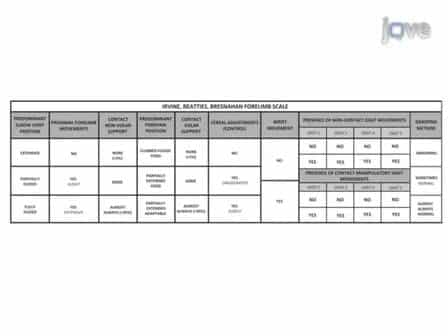

A Novel Method for Assessing Proximal and Distal Forelimb Function in the Rat: the Irvine, Beatties and Bresnahan IBB Forelimb Scale
Published on: December 16, 2010
Palsy of elbow extension
1Faculté de Médecine, Université Montpellier 1, 5, Boulevard Henri IV, 34090 Montpellier, France; Service de chirurgie de la main et du membre supérieur, chirurgie des paralysies, Institut de Neuro-Orthopédie Montpellier, Hôpital Lapeyronie, CHU de Montpellier, Avenue du doyen Gaston Giraud, 34295 Montpellier Cedex 5, France.

Abstract:
Elbow extension palsy is generally well tolerated, because when standing up, it is alleviated by gravity. In the case of trunk paralysis or brachial plexus palsy, standing is possible, thus the restoration of active elbow extension improves the hand's positioning above the shoulder, and allows the elbow to be locked in extension, which is necessary during certain activities such as cycling. In these palsy cases, the triceps brachii will be reinnervated by nerve transfers if surgery is performed early enough before irreversible atrophy of the effector muscle sets in. In these situations, secondary tendon transfers are rarely indicated. Few available muscles can be harvested without deleterious consequences on the donor site. Finally, in patients with a very deficient upper limb but with a healthy contralateral limb, when nerve transfers are no longer possible, elbow extension will not be restored. In the tetraplegics using a wheelchair, elbow extension becomes essential for positioning the hand in space and for potentiating the transferable muscles to activate the hand. As nerve transfers have rare indications and are currently being validated in this population, palliative tendon transfers are the reference technique. They must be integrated into an overall upper limb reconstructive surgery program that takes into consideration the potentially usable muscles and the presence of elbow flexion contracture and supination deformity of the forearm. Elbow extension restoration techniques are based on the transfer of two muscles, the posterior deltoid and the biceps brachii. The first is very effective and has very specific requirements, notably good anterior stabilization of the shoulder by the pectoralis major, while the second has broader indications, notably in the case of elbow contracture and inability to stabilize the shoulder anteriorly.

Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:15
Bones of the Upper Limb: Ulna
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:19
Bones of the Upper Limb: Humerus
 01:17
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi...