Related Experiment Video
Updated: Oct 22, 2025

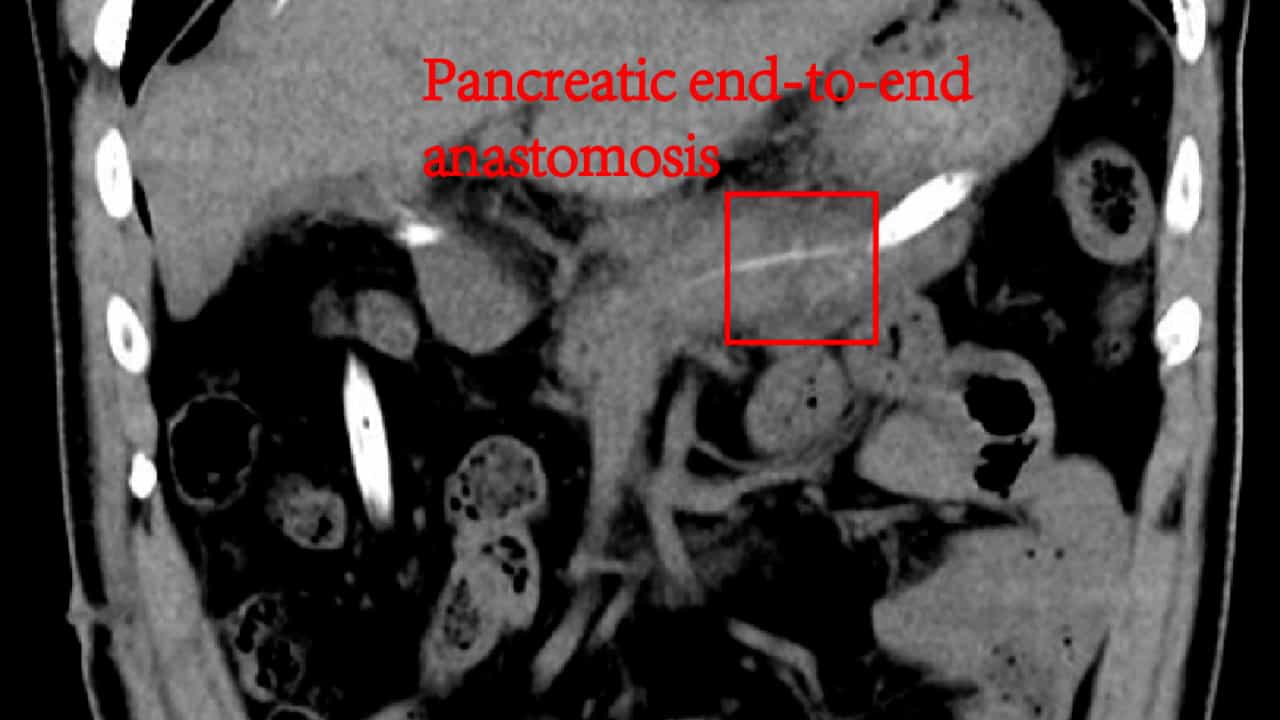
Application of End-to-end Anastomosis in Robotic Central Pancreatectomy
Published on: June 2, 2018
Resection of Non-Functional Pancreatic Neuroendocrine Neoplasms-A Single-Center Retrospective Outcome Analysis
Kirsten Lindner1, Daniel Binte1, Jens Hoeppner1
1Department of Surgery, University Medical Center of Schleswig-Holstein-Campus Lübeck, Ratzeburger Allee 160, 23538 Lübeck, Germany.

Abstract:
Surgery remains the only curative treatment of pancreatic neuroendocrine neoplasms (pNEN). Here, we report the outcome after surgery for non-functional pNEN at a European Neuroendocrine Tumor Society (ENETS) center in Germany between 2000 and 2019; cases were analyzed for surgical (Clavien-Dindo classification; CDc) and oncological outcomes. Forty-nine patients (tumor grading G1 n = 25, G2 n = 22, G3 n = 2), with a median age of 56 years, were included. Severe complications (CDc ≥ grade 3b) occurred in 11 patients (22.4%) and type B/C pancreatic fistulas (POPFs) occurred in 5 patients (10.2%); in-hospital mortality was 2% (n = 1). Six of seven patients with tumor recurrence (14.3%) had G2 tumors in the pancreatic body/tail. The median survival was 5.7 years (68 months; [1-228 months]). Neither the occurrence (p = 0.683) nor the severity of complications had an influence on the relapse behavior (p = 0.086). This also applied for a POPF (≥B, p = 0.609). G2 pNEN patients (n = 22) with and without tumor recurrence had similar median tumor sizes (4 cm and 3.9 cm, respectively). Five of the six relapsed G2 patients (83.3%) had tumor-positive lymph nodes (N+); all G2 pNEN patients with recurrence had initially been treated with distal pancreatic resection. Pancreatic resections for pNEN are safe but associated with relevant postoperative morbidity. Future studies are needed to evaluate suitable resection strategies for G2 pNEN.