Related Experiment Video
Updated: Oct 22, 2025
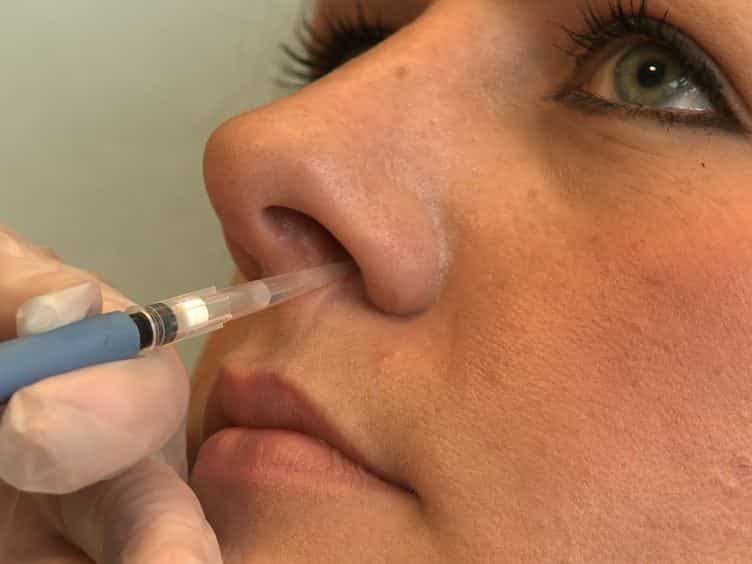

Experimental Human Pneumococcal Carriage
Published on: February 15, 2013
Risk of COVID-19 in shielded and nursing care home patients: a cohort study in general practice
David Wingfield1,2, Mansour Taghavi Azar Sharabiani1, Azeem Majeed1
1Department of Primary Care and Public Health, Imperial College London, London, UK.

Background:
COVID-19 cases were first detected in the UK in January 2020 and vulnerable patients were asked to shield from March to reduce their risk of COVID-19 infection.
Aim:
To determine the risk and determinants of COVID-19 diagnosis in shielded versus non-shielded groups, adjusted for key comorbidities not explained by shielding.
Design & Setting:
Retrospective cohort study of adults with COVID-19 infection between 1 February 2020 and 15 May 2020 in west London.
Method:
Individuals diagnosed with COVID-19 were identified in SystmOne records using clinical codes. Infection risks were adjusted for sociodemographic factors, nursing home status, and comorbidities.
Results:
Of 57 713 adults, 573 (1%) individuals were identified as shielded and 1074 adults had documented COVID-19 infections (1.9%). COVID-19 infection rate in the shielded group individuals compared with non-shielded adult individuals was 6.5% (n = 37/573) versus 1.8% (n = 1037/57 140), P<0.001. A multivariable fully adjusted Cox proportional hazards (CPH) regression identified that COVID-19 infection was increased with shielding status (adjusted hazard ratio [aHR] 1.52; 95% confidence interval [CI] = 1.00 to 2.30; P = 0.048). Other determinants of COVID-19 infection included nursing home residency (aHR 7.05; 95% CI = 4.22 to 11.77; P<0.001); Black African (aHR 2.52; 95% CI = 1.99 to 3.18; P<0.001), Other (aHR 1.74; 95% CI = 1.42 to 2.13; P<0.001), Non-stated (aHR 1.70; 95% CI = 1.02 to 2.84; P = 0.04), or South Asian ethnic group (aHR 1.46; 95% CI = 1.10 to 1.93; P = 0.01); history of respiratory disease (aHR 1.51; 95% CI = 1.06 to 2.16; P = 0.02); deprivation (third versus least deprived Index of Multiple Deprivation [IMD] quintile) (aHR 1.25 ; 95% CI = 1.01 to 1.56; P = 0.05); obesity (body mass index [BMI] >30 kg/m2) (aHR 1.39; 95% CI = 1.18 to 1.63; P<0.001); and age (aHR 1.02; 95% CI = 1.01 to 1.02; P<0.001. Male sex was associated with lower risk of COVID-19 infection (aHR 0.71; 95% CI = 0.62 to 0.82; P<0.001).
Conclusion:
Shielded individuals had a higher COVID-19 infection rate compared with non-shielded individuals, after adjusting for sociodemographic factors, nursing home status, and comorbidities.
More Related Videos


Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:29
Bias in Epidemiological Studies
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...