Related Experiment Video
Updated: Oct 21, 2025


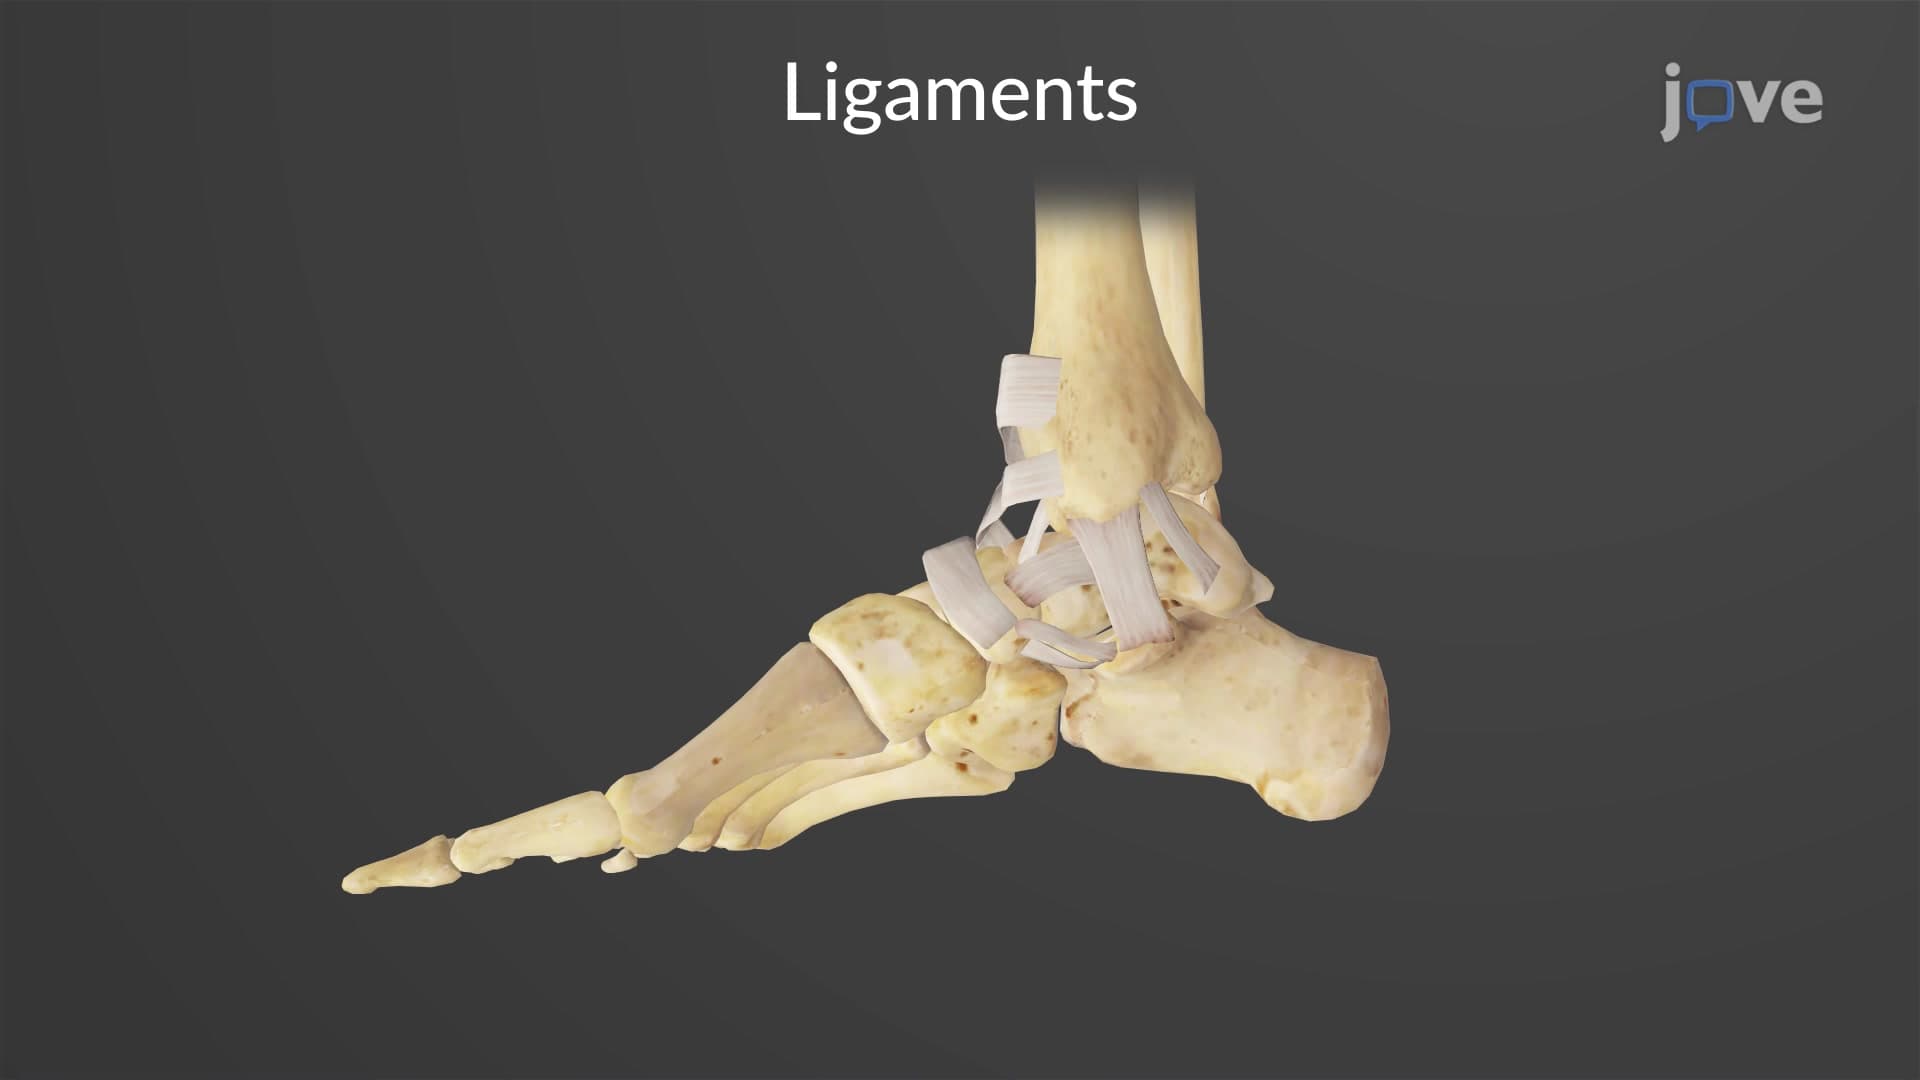
A Mouse Model of Ankle-Subtalar Complex Joint Instability
Published on: October 28, 2022
Multiplanar instability of the first tarsometatarsal joint in hallux valgus and hallux rigidus patients: a
Hee Young Lee1, Matthieu Lalevee1,2, Nacime Salomao Barbachan Mansur1,3
1Department of Orthopaedics and Rehabilitation, University of Iowa, 200 Hawkins Drive John Pappajon Pavilion, Room 01066, Iowa City, IA, 52242, USA.

Background:
Hypermobility of the first ray has been considered associated with various forefoot diseases including hallux valgus (HV) and hallux rigidus (HR). Weightbearing CT scan can be a reliable method for analysis of the first tarsometatarsal (TMT) joint in axial, sagittal, and coronal planes. Our objective was to comparatively investigate signs of instability of the first TMT joint on weightbearing CT between three groups (control, HV, and HR).
Methods:
In this single-centre, retrospective, case-control study, 27 HV patients (30 feet; mean age 54.2 years), 26 HR patients (30 feet; mean age 56.6 years), and 30 controls (30 feet; mean age; 43 years) were enrolled. Measurements of signs of instability were performed in multiplanes including first TMT angle, dorsal translation of the first metatarsal (M1) at the first TMT joint, plantar distance between the medial cuneiform (C1) and M1 in sagittal plane, hallux valgus angle (HVA), intermetatarsal angle (IMA) in axial plane, rotational profiles of C1 and M1 in coronal plane. Analysis of variance (ANOVA) test and chi-square test were performed to compare each parameter between the three groups. Interobserver reliabilities were assessed using interclass correlation coefficients (ICCs).
Results:
The HV group had significantly increased first TMT angle (0.23° in controls, 1.15° in HV, 0.19° in HR, p < 0.001), HVA (7.52°, 33.50°, 11.21°, p < 0.001), IMA (9.46°, 16.98°, 11.87°, p < 0.001), C1-M1 angle (22.44°, 29.46°, 23.74°, p < 0.001), and rotational profile of the distal M1 (7.06°, 17.88°, 9.85°, p < 0.001) compared with the control and HR groups. Dorsal translation of M1 (23% in controls, 63% in HV, 70% in HR, p < 0.001) was frequently found in the HV and HR groups with significantly increased plantar distance (0.37 mm, 1.14 mm, 1.46 mm, p < 0.001) compared with controls.
Conclusions:
Multiplanar instability of the first TMT joint was confirmed using weightbearing CT in HV and HR groups compared with controls. HV group demonstrated instability mainly in sagittal and axial planes; HR group had sagittal instability predominantly. Our measurement of rotational instability at the first TMT joint was not able to detect differences between groups. A surgical correction of the instability at the first TMT joint can be an option to address HV and HR.
Clinical Relevance:
First ray hypermobility at the first TMT joint is an important consideration when addressing HV and HR, a surgical correction of the instability at the first TMT joint should be taken in consideration as an option.
More Related Videos
 15:04
An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
 06:35
Using Gold-standard Gait Analysis Methods to Assess Experience Effects on Lower-limb Mechanics During Moderate High-heeled Jogging and Running
Published on: September 14, 2017