Related Experiment Video
Updated: Oct 21, 2025


5/6 Nephrectomy Using Sharp Bipolectomy Via Midline Laparotomy in Rats
Published on: April 4, 2025
Prevalence of Metabolic Acidosis Among Patients with Chronic Kidney Disease and Hyperkalemia
Erin E Cook1, Jill Davis2, Rubeen Israni2
1Analysis Group, Boston, MA, USA. Erin.Cook@analysisgroup.com.

Insights
Metabolic acidosis is common in chronic kidney disease (CKD) patients with hyperkalemia, affecting up to 39% of individuals. Prevalence estimates vary significantly based on diagnostic criteria used for both conditions.
Area of Science:
- Nephrology
- Internal Medicine
- Clinical Research
Background:
- Hyperkalemia and metabolic acidosis frequently coexist in patients with chronic kidney disease (CKD).
- The precise prevalence of metabolic acidosis in CKD patients experiencing hyperkalemia remains understudied.
- Understanding this overlap is crucial for effective patient management.
Purpose of the Study:
- To estimate the prevalence of metabolic acidosis among adult patients with CKD and hyperkalemia.
- To analyze how different diagnostic criteria for hyperkalemia and metabolic acidosis influence prevalence estimates.
Main Methods:
- Retrospective analysis of medical records from the Research Action for Health Network.
- Inclusion criteria: adult patients with CKD stages 3-5, with at least one outpatient potassium > 5.0 mEq/L and available bicarbonate levels.
- Exclusion criteria: patients with end-stage kidney disease (ESKD) in the prior year. Prevalence calculated for 2014-2017 using varying definitions for hyperkalemia (K > 5.0 or > 5.5 mEq/L) and metabolic acidosis (HCO3 < 18 or < 22 mEq/L).
Main Results:
- In 2017, patients with metabolic acidosis were younger, had more advanced CKD, and were more likely to use oral sodium bicarbonate compared to those without.
- Prevalence of metabolic acidosis (HCO3 < 22 mEq/L) ranged from 25-29% (K > 5.0 mEq/L) to 33-39% (K > 5.5 mEq/L).
- Prevalence estimates were sensitive to the specific diagnostic thresholds applied.
Conclusions:
- The prevalence of metabolic acidosis in CKD patients with hyperkalemia is substantial.
- Diagnostic criteria significantly impact the calculated prevalence of metabolic acidosis in this population.
- Further research may be needed to standardize diagnostic approaches.
Introduction:
Although hyperkalemia and metabolic acidosis often co-occur in patients with chronic kidney disease (CKD), the prevalence of metabolic acidosis among patients with CKD and hyperkalemia is understudied. Therefore, we used medical record data from the Research Action for Health Network to estimate this prevalence.
Methods:
Adult patients with CKD stage 3-5, ≥ 1 outpatient potassium value > 5.0 mEq/l, and ≥ 1 outpatient bicarbonate value available were identified. Patients with end stage kidney disease (ESKD) in the prior year were excluded. The prevalence of metabolic acidosis in each calendar year from 2014 to 2017 among patients with CKD and hyperkalemia was estimated using two definitions of hyperkalemia (potassium > 5.0 mEq/l and > 5.5 mEq/l) and metabolic acidosis (bicarbonate < 18 mEq/l and < 22 mEq/l).
Results:
In the 2017 patient cohort and among patients with CKD and hyperkalemia, patients with metabolic acidosis were younger (69 versus 74 years), more likely to have advanced CKD (35% versus 13%), and use oral sodium bicarbonate (21% versus 4%) than patients without metabolic acidosis. The prevalence of metabolic acidosis (< 22 mEq/l) ranged from 25 to 29% when hyperkalemia was defined by potassium > 5.0 mEq/l and ranged from 33 to 39% when hyperkalemia was defined by potassium > 5.5 mEq/l.
Conclusion:
Results demonstrated that prevalence estimates of metabolic acidosis varied based on the definition of hyperkalemia and metabolic acidosis utilized.


Related Concept Videos
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:29
Renal Regulation of Acid-Base Balance
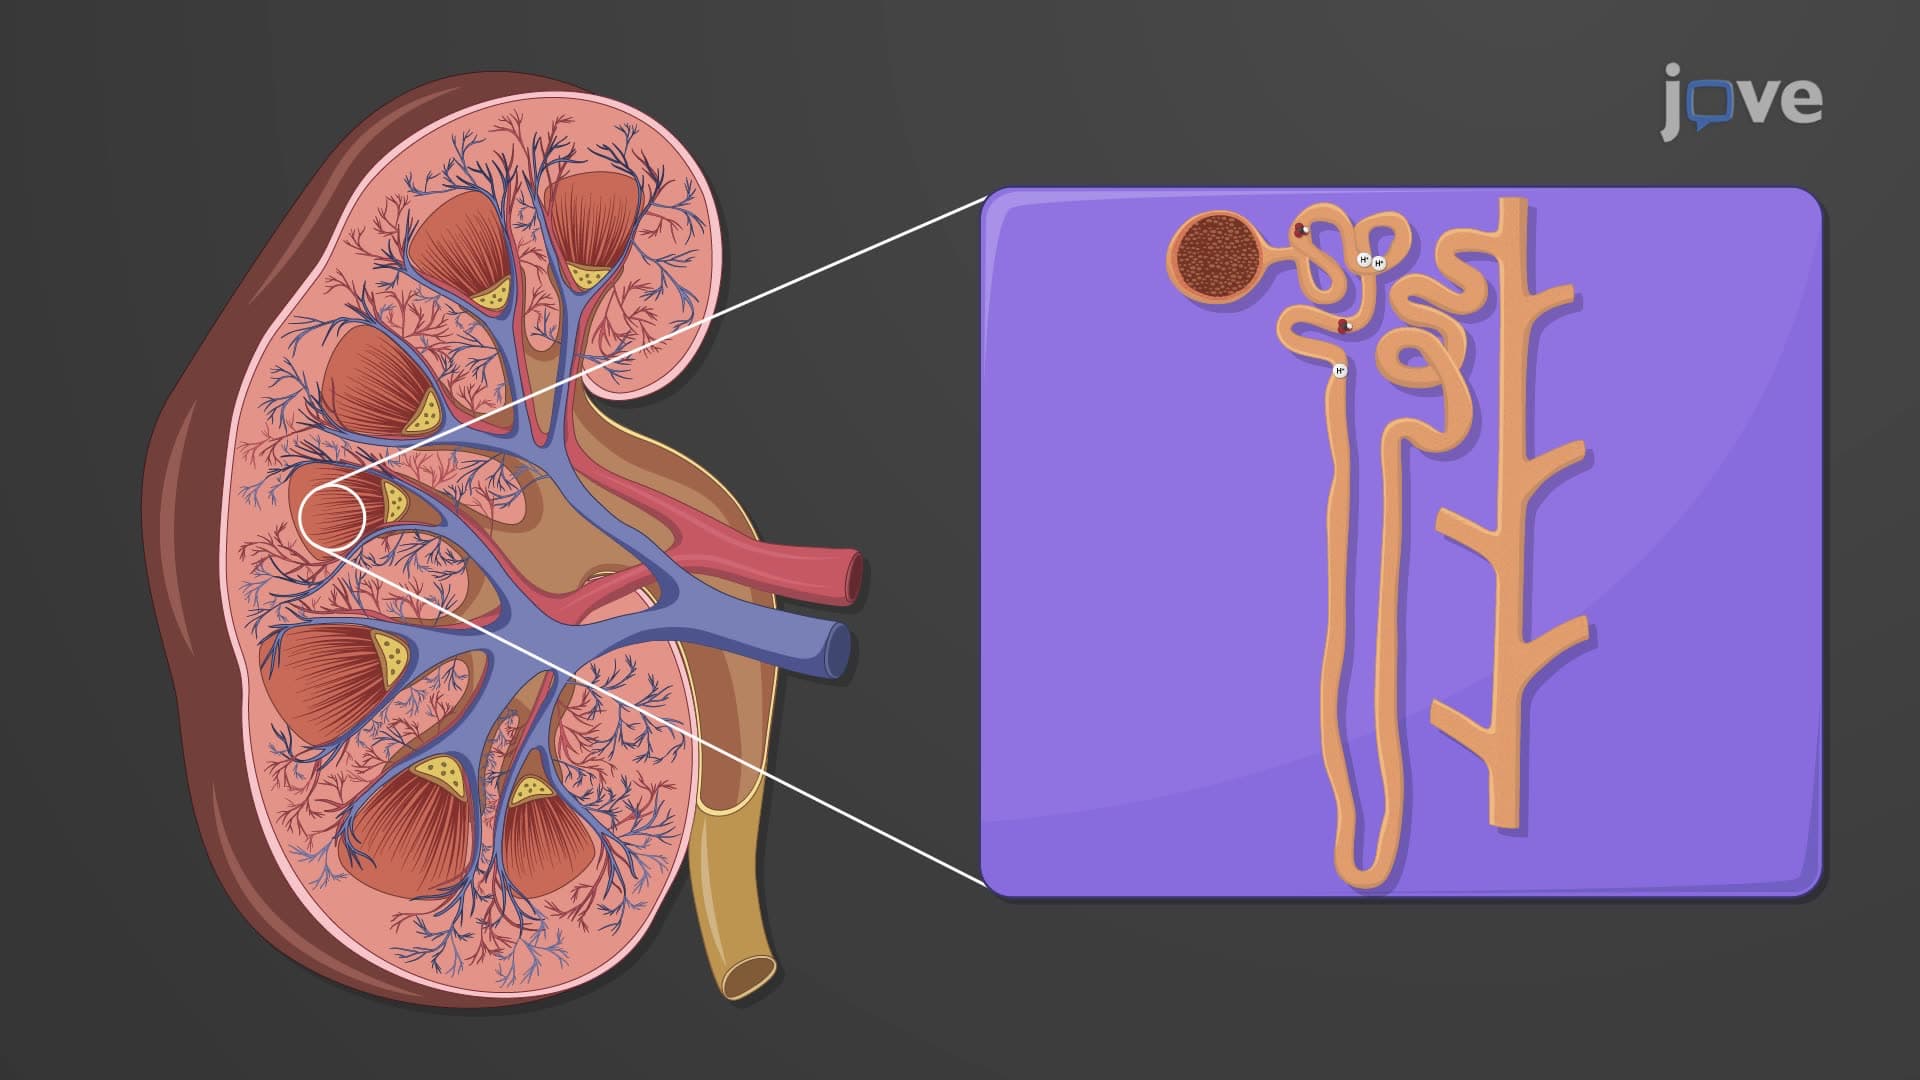
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Chronic Kidney Disease I: Introduction