Related Experiment Video
Updated: Oct 21, 2025
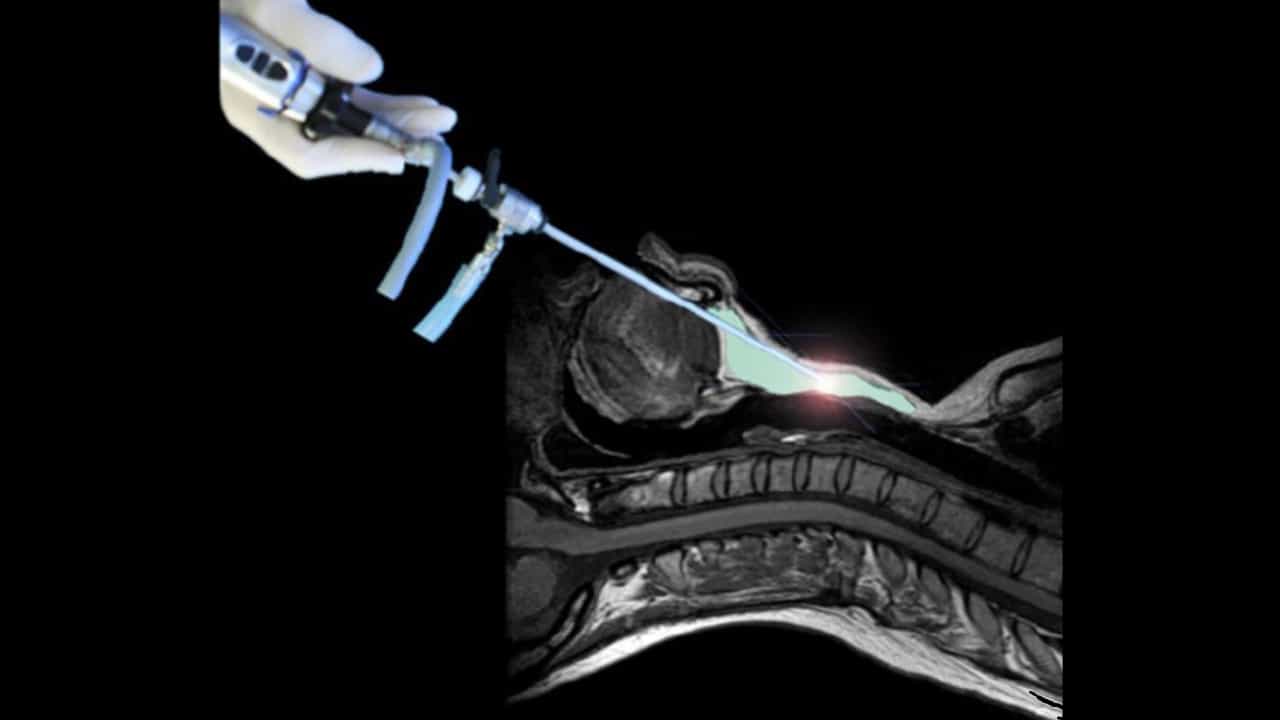
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Indications of Superselective Neck Dissection in Patients With Lateral Node Metastasis of Papillary Thyroid Carcinoma
Yuntao Song1, Guohui Xu1, Tianxiao Wang1
1Department of Head and Neck Surgery, Peking University Cancer Hospital and Institute, Key Laboratory of Carcinogenesis and Translational Research (Ministry of Education/Beijing), Beijing, China.

Objective:
The extent of neck dissection in papillary thyroid carcinoma (PTC) patients with lateral neck metastasis is controversial. This work aims to screen the patients suitable for superselective neck dissections including only levels III-IV.
Study Design:
Prospective observational cohort study.
Setting:
The study was conducted in a high-volume tertiary care setting.
Methods:
A total of 134 consecutive previously untreated PTC patients with lateral neck metastases and subjected to 154 therapeutic lateral neck dissections (including levels II, III, IV, and VB) between June 2018 and March 2021 were enrolled. Fine-needle aspiration was performed preoperatively at each suspicious neck level. Clinical predictors were analyzed for occult lymph node metastases at levels II and VB.
Results:
As a result, 44.8% and 5.8% of neck specimens exhibited metastatic lymph nodes at levels II and VB. In addition, univariate and multivariate analyses showed that the primary tumor in the ipsilateral thyroid upper lobe (P = .016, odds ratio = 3.528) and clinically multiple metastatic lymph nodes in level III-IV (P = .005, odds ratio = 6.414) were independent predictive factors for occult level II metastases. All 3 (1.9%) occult metastases at level VB were found in necks with preoperative multiple lymph node metastases.
Conclusions:
A superselective lateral neck dissection including levels III to IV may be considered in patients with PTC when the preoperative evaluation identifies a single lymph node metastasis located at levels III to IV and the primary tumor is not in the upper lobe of the ipsilateral thyroid.