Do ScvO2 variations induced by passive leg raising predict fluid responsiveness? A prospective study
Related Experiment Video
Updated: Oct 21, 2025
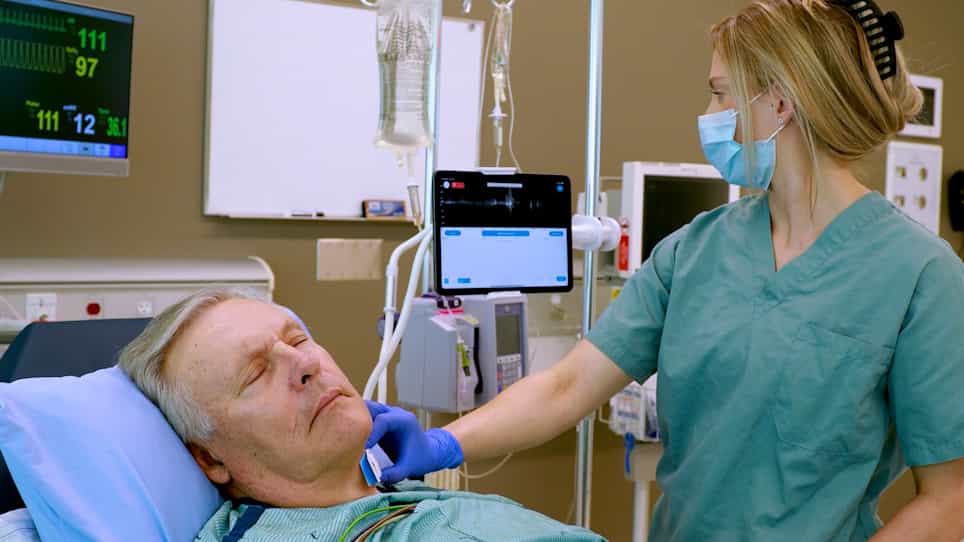
Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Raphaël Giraud1,2,3, Bojana Vujovic1, Benjamin Assouline1,2,3
1Intensive Care Unit, Geneva University Hospitals, Geneva, Switzerland.

Objective:
The present study investigates whether ScvO2 variations induced by passive leg raising (PLR) are able to predict fluid responsiveness (FR) in mechanically ventilated patients.
Design:
A monocentric prospective clinical study.
Setting:
An intensive care division in a tertiary hospital.
Patients:
The inclusion criteria were elective postoperative cardiac surgery patients who were over 18 years old, deeply sedated, mechanically ventilated and needed volume expansion (VE). Fluid responders (R) were defined as patients who increased their left ventricular outflow tract velocity time integral (VTI) ≥15% after VE.
Intervention:
In patients included in this study, continuous ScvO2 monitoring (CeVOX device, Pulsion Medical Systems) and VTI (transthoracic echocardiography) were measured simultaneously before and during a PLR test and before and after VE (with 500 ml of saline).
Measurements And Main Results:
Thirty-three consecutive patients were included in this study. In 15 patients with a positive PLR test (increase in VTI ≥15%), ScvO2 increased during PLR by 9 ± 4%. In the 18 patients with a negative PLR test, ScvO2 did not significantly change during PLR. VE increased ScvO2 by 9 ± 6% and 2 ± 4% in responders and nonresponders, respectively. If ScvO2 increased by >4% during the PLR test, then a positive VTI response (≥15%) was diagnosed with a sensitivity of 93% (68-99%) and a specificity of 94% (63-99%) (Area under the receiver operating characteristic curve 0.92 ± 0.58, p < 0.05). Moreover, ScvO2 variations were able to distinguish responders to VE from nonresponders to VE with a sensitivity of 87% (68-99%) and a specificity of 89% (63-99%) (Area under the receiver operating characteristic curve 0.89 ± 0.07, p < 0.05).
Conclusions:
ScvO2 variation induced by PLR is a reliable, minimally invasive parameter for predicting FR at the postoperative cardiac surgery bedside of mechanically ventilated, critically ill patients.
More Related Videos
 09:18
Author Spotlight: Assessing the Reliability of Doppler Ultrasound in Measuring Leg Blood Flow
Published on: December 15, 2023
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:15
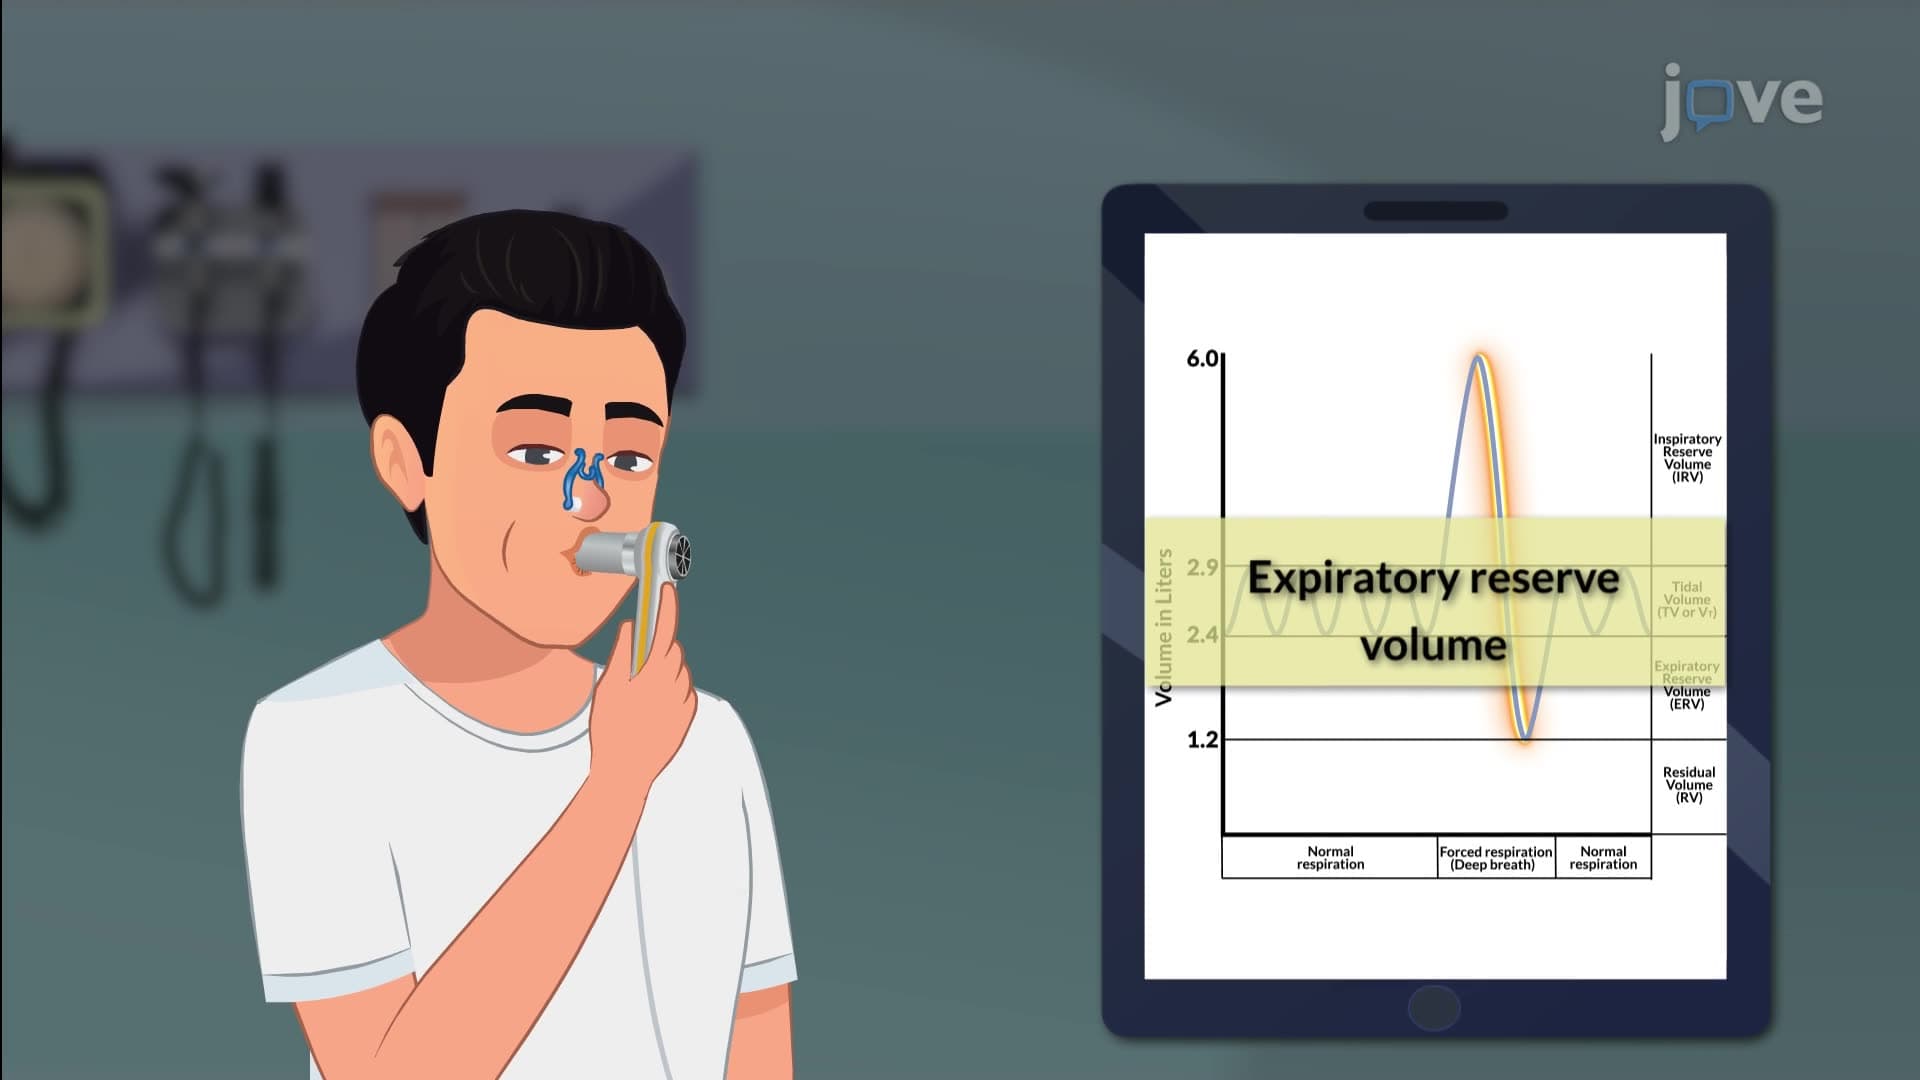
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: