Related Experiment Video
Updated: Jul 11, 2026


Evaluation of Coronary Flow Reserve After Myocardial Ischemia Reperfusion in Rats
Published on: June 28, 2019
Coronary dilator effects of intracoronary nifedipine and isosorbide dinitrate
B Griffin1, A D Timmis, E Sowton
1Department of Cardiology, Guy's Hospital, London, U.K.

Abstract:
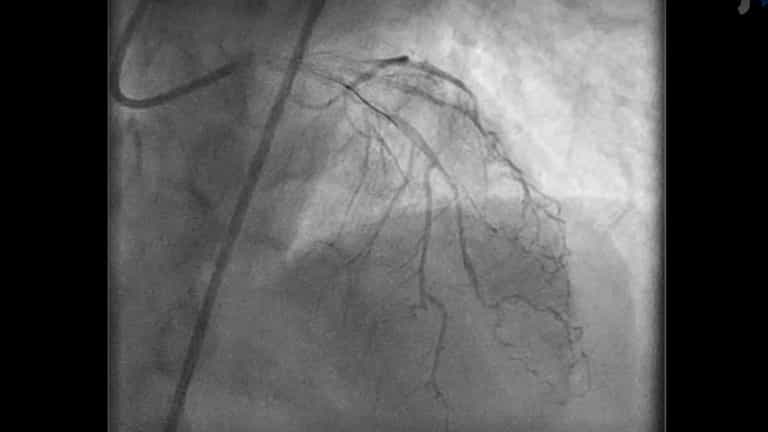
Although both nitrates and calcium antagonists may be administered by the intracoronary route, the relative efficacy of these agents and of their combination is unknown. In this study, we investigated the coronary vasodilatory potential of intracoronary nifedipine, isosorbide dinitrate and their combination in patients undergoing routine coronary arteriography. Both normal and diseased segments of coronary arteries were studied. Coronary artery diameters were measured from 35 mm cine film before and after the administration of each drug. Two groups of 10 patients were studied: group I received nifedipine, 0.2 mg, followed by isosorbide dinitrate, 1 mg, group II received isosorbide dinitrate, 1 mg, followed by nifedipine, 0.2 mg. Both agents resulted in significant dilatation of normal and diseased segments of the coronary arteries when injected as the first drug, but neither nifedipine nor isosorbide dinitrate produced significant additional vasodilation when injected as the second drug. The degree of dilatation of both diseased and normal segments produced by either nifedipine or isosorbide dinitrate was similar, suggesting that the dose used, of either drug, produced near maximal coronary vasodilatation. Importantly, drug induced dilatation of stenotic segments was similar to that of normal segments.

Related Concept Videos
 01:23
Antihypertensive Drugs: Vasodilators
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:26
Coronary Artery Disease II: Pathophysiology
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:28
Acute Coronary Syndrome IV: Interprofessional Care