Related Experiment Video
Updated: Aug 12, 2026


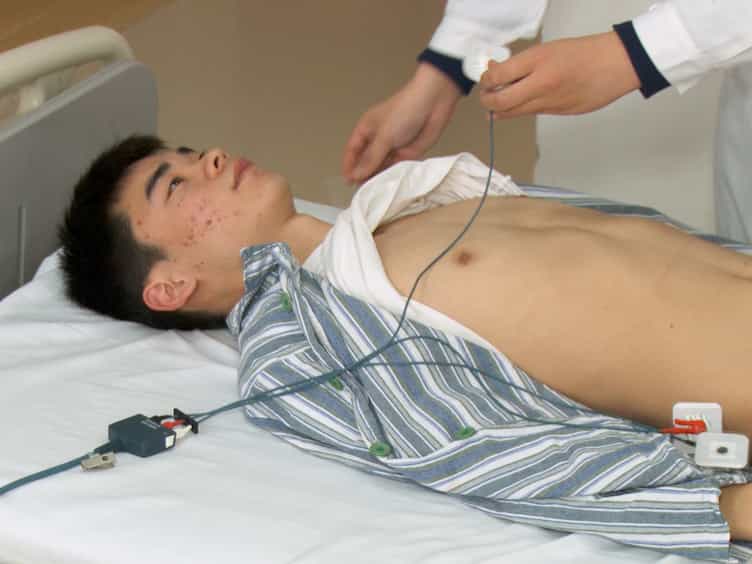
Measuring Cardiac Autonomic Nervous System (ANS) Activity in Children
Published on: April 29, 2013
Ten-year follow-up study of children with primary hypertension from Sofia, Bulgaria
R D Rahneva1, D P Belova, R A Nedkova
1Research Institute of Pediatrics, Medical Academy, Sofia, Bulgaria.

Insights
Childhood primary hypertension (PH) often persists into adulthood, leading to significant cardiovascular and metabolic issues. Long-term follow-up reveals persistent hypertension and target organ damage in a substantial portion of affected children.
Area of Science:
- Pediatric Cardiology
- Hypertension Research
- Longitudinal Health Studies
Background:
- Primary hypertension (PH) in children is a growing concern with potential long-term health implications.
- Understanding the natural course and risk factors associated with childhood PH is crucial for effective management.
- Previous studies have indicated potential target organ damage and metabolic abnormalities in hypertensive children.
Purpose of the Study:
- To investigate the long-term outcomes of childhood primary hypertension over a 10-year period.
- To assess the persistence of hypertension, development of target organ changes, and influence of risk factors.
- To compare outcomes with a control group of children with normal blood pressure.
Main Methods:
- A 10-year longitudinal study (1972-1983) involving 251 children aged 6-15 with primary hypertension.
- Regular monitoring of blood pressure (BP), target organ status (heart via ECG, x-ray, echocardiography), and metabolic risk factors.
- Inclusion of a control group of 145 children with normal BP during the same period.
Main Results:
- After 10 years, 44.2% of children remained hypertensive, 29.9% had borderline hypertension, and 25.9% had normal BP.
- Significant cardiac functional and structural changes were observed in a considerable number of participants.
- Prevalence of angioretinopathy (24.0%), hyperlipoproteinemia (45.3%), and low HDL-cholesterol (34.5%) was noted in those with childhood PH.
Conclusions:
- Childhood primary hypertension frequently persists into later years, highlighting the need for early intervention.
- Long-term follow-up reveals a significant burden of cardiovascular and metabolic complications in individuals with childhood PH.
- These findings underscore the importance of continued monitoring and management of pediatric hypertension to prevent long-term sequelae.
Abstract:
A longitudinal study of 251 children with primary hypertension (PH), aged 6-15 from Sofia, Bulgaria, was carried out over a 10-year period (1972-1983). The dynamics of blood pressure (BP), target organ changes, and risk-factors influence were followed up. In the tenth year, 44.2% of the persons remained hypertensive, 29.9% were found to be with borderline hypertension, and 25.9% with normal BP. Functional and structural changes in the heart were discovered in a considerable number of the persons by ECG, x-ray, and echocardiography examinations. Furthermore, angioretinopathy I and II gr. in 24.0%, hyperlipoproteinemia (IIA, IIB, and IV type) in 45.3% and low levels HDL-chol. (less than or equal to 0.905 mmol/l) in 34.5% were present at the end of the study in those young persons who had PH in childhood. A control group of 145 children with normal BP in 1972-1973 has been followed up over the same period.
Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction while...
 01:28
Hypertension I: Introduction
 01:29
Hypertension II: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications